Environment Network 2024: Environmental risk assessment what do we need to know?

As Girlymicro has a) got tonsillitis and b) attempting to run the day, todays blog is a guest blog brought to you by frequent Girlymicrobiologist contributors and Environment Network stakeholder members: Sam Watkin and Dr Claire Walker.

It’s the most wonderful time of the year! Today is the Environment Network meeting where we gather together to talk all things environmental risk assessment.  This is a network for people in clinical, scientific and engineering roles within the NHS and other associated organisations who are interested in the role of environmental infection prevention and control in preventing infection. Despite being an immunologist (Claire Walker) for most of my career, this is one of my favourite meetings of the year. Everyone is deeply passionate about what they do and how we can work together to exchange ideas and improve practice.

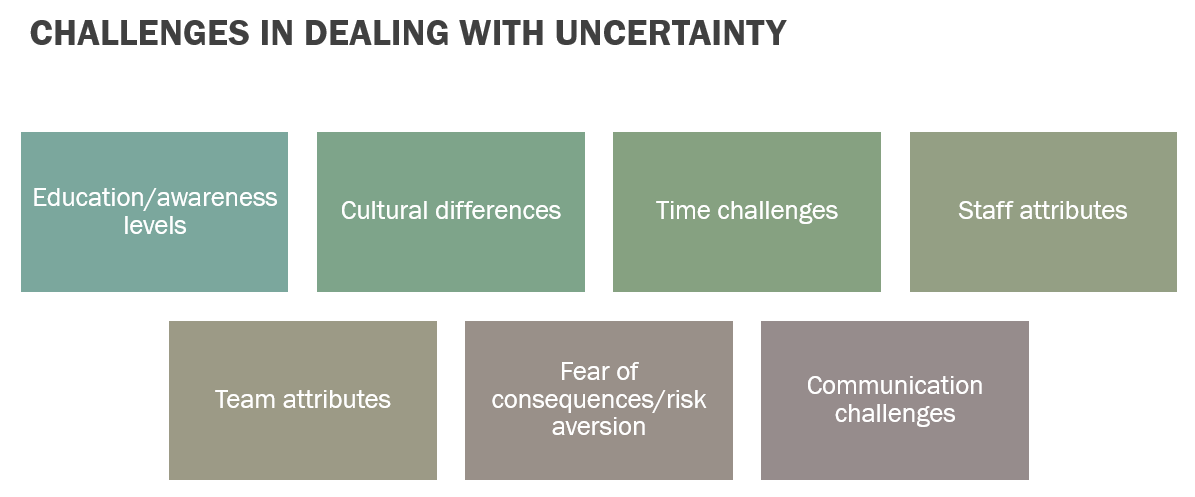
Too kick us off, we have the wonderful Professor Elaine Cloutman-Green and Lena Ciric welcoming us to a day of interactive sessions on key issues in the field. Prof C-G sets the scene for our day introducing the concept of our different perceptions of risk assessment and the challenge of unexpected consequences. Of course we understand the triumvirate of identify, understand and mitigate problems but how an engineer approaches risk is quite different to how a clinician might. As Prof C-G says clinical risk assessment is not a zero harm game, it is about controlling real rather than theoretical harm. A balance needs to be stuck between what is most appropriate for the patient – we could keep patients in bubbles and not even have healthcare professionals approach them, but I doubt that patient would fare very well! There is a need to balance the approach of the clinical and the engineer to find an optimal position to minimise harm. To make these decisions we need to consider the interaction between organism, patient and the built environment in order to work out what the control measure should look like. Problems aren’t simple, we need to accept and embrace that risk assessment is a complex process. And perhaps most importantly we need to take the time to see the perspectives of others, or we might never see the elephant in the room.

Risk assessment has the potential to make use all uncomfortable, as scientists we do not enjoy the unknown. In good risk assessment A plus B does not always equal C, it might do 50% of the time so we have to rely on our best judgement. Moreover, risk is not static. All patient and clinical environments are quite different as we need to pick the point that works for that situation – National guidance can never cover all of these unique situations. A multi-disciplinary team approach is essential to ensure we are asking the right questions.

Next up we have Dr Susanne Surman-Lee giving a talk on combining clinical and engineering risk and why working in silos hinders risk assessments. Silo working at all levels, even within a team, can cause a raft of problems, with poor communication, different priorities, resource conflicts and inefficiencies. This can mean those in each silo work to their desired outcomes, not taking into account what other requirements may be. The danger of this is that it ultimately increases the risk to patients.

A poll found that the event was well attended by people from a range of disciplines, covering many relevant professions to environmental infection control. We often all want different things from a building, be that aesthetic, cost or usability. What is critical, and reflected in new guidance, is that the purpose of a building must be to put the patient first.

To escape working in silos, the audience recognised that communication is absolutely key. Working as a single team, sharing respect, data sharing and fostering a collaborative culture is all needed to break down individual working silos. This enables the project team to work as a single unit, supporting faster, safer decisions across strategic levels.

A set of examples on real-world decision-making processes highlighted not only the importance of accurate record keeping when it comes to decision-making, but also what can happen when an IPC challenge is only viewed through teams working in silos.

When considering waterborne infection risks, a multitude of challenges, both from an engineering and non-engineering standpoint must be considered. This can range from inadequate usage leading to stagnation, poor hygiene during installation and poor labelling, outlet misuse, poor cleaning techniques and inappropriate assessment if transmission risks as examples.

Ultimately, we must consider the problem as a whole. Different hazards and sources of pathogens overlap, meaning we must work across disciplines to mitigate risk. We also must gather information from multiple sources to identify risks to make sure a risk isn’t overlooked.

Updated guidance has recently been produced following an outbreak of non-tuberculous Mycobacteria for the safe design and management of new buildings calls for collaborative working throughout the project, with continual risk assessments and project ownership by the trust. Having a multidisciplinary approach can help effectively design and manage risk, improving IPC risk assessment and decision-making procedures.

In this final session before some essential caffeine, we have Andrew Poplett taking us on a whistle stop tour of derogation management. Derogations, like puppies, are for life – if you agree to one you must be sure as they are extremely difficult to reverse. We know that unless specifically stated much of the guidance in not mandatory. However departure or derogation from HTM should provide a degrees of safety NOT LESS THAN that achieved by following the guidance laid out in the HTM.

A derogation is an exemption from or relation of a standard or rule but it must be carefully managed, documented and justified. It must be risk assessed and cannot be to reduce costs. Of course, the bugs haven’t read the HTMs and they really don’t care about the budget! Minimum standards and patient safety guidelines cannot be derogated, but for those for those ‘nice to haves’ there is some wriggle room. So why do we want to derogate? Situations like conflicting guidance and refurbishment of existing buildings. Once again we are lead to the conclusion that these decisions must be the result of a multi-disciplinary team approach and risk assessments – these decisions can’t be made solely by a financial manager, an engineer, a microbiologist or infection prevention and control, but requires a meeting of minds to reach the right conclusion. The cornerstone of derogations is communication, ideally reaching a sensible and agreed consensus that balances risk, compliance and other important factors (like cost!). Ego needs to be left at the door or we might need to start hiring some referees!

If you break the rules, you really need to document why, what, who and when. It’s not to say that we shouldn’t, as we know every circumstance is difference. But transparency is essential to the process, and they do need to be reviewed regularly. As a final thought, Andrew invites us to consider that it is important to remember that it is always cheaper to invest the time upfront because short cuts tend to end in expensive disaster.
After a quick coffee break, we have Louise Clarke from GPT Consult discussing capturing water and ventilation risks as part of governance strategies. First off, we must understand what risks we actually need to assess and manage. We often have aging infrastructures, changes in usage, hidden infrastructure, access challenges and maintenance works. Not only that, how people use and view spaces factors into the risks we must assess.

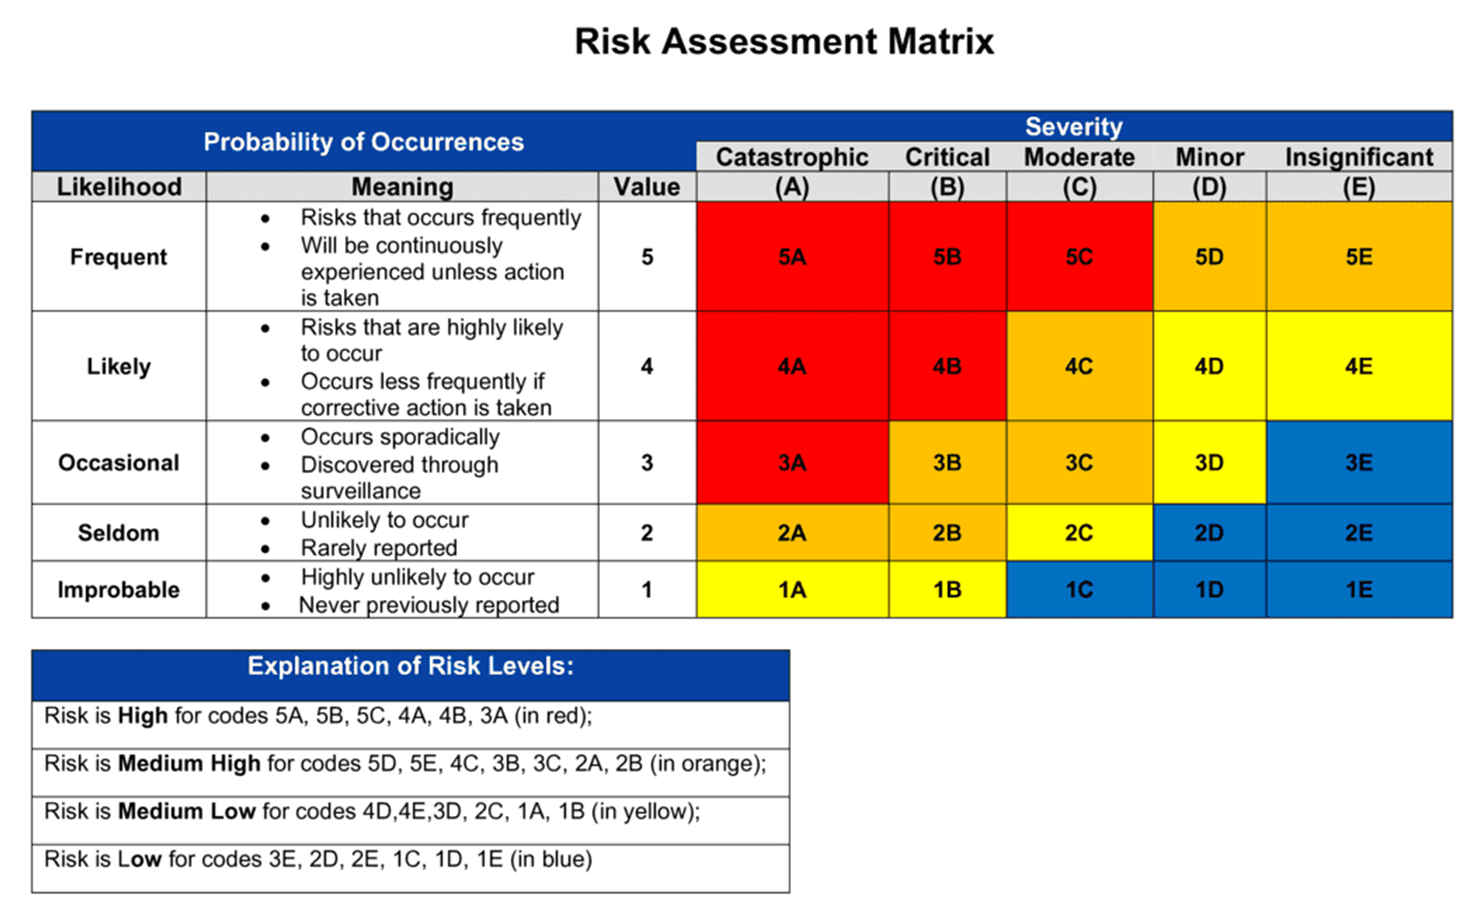
When assessing risk, it must be suitable and sufficient. But what does that actually mean? It depends on what you are trying to deliver, what you are looking for and what is being managed. Five-by-five risk matrices do not necessarily capture the complexities of these risks. Not only this, a huge amount od information is required for effective assessment. Factors like patient factors, unique building features, data from building management systems must all be considered. Not only that, but there are a large amount of unknown factors which need to be considered. The current state of a building and the equipment in place is important to consider, with the impact these may have in the future on risk taken into account. Overall risk profiles are needed but challenging to achieve as many people view the risk of a setting from different perspectives.

All risk assessments must be performed within the appropriate legislation. This covers government legislation, approved codes of practice and best practice guidance (such as the HTMs). To ensure that all standards and met and the process of derogation is appropriately followed, governance structures have to be followed. But these structures themselves can be difficult to navigate. The reporting of information gathered from the building (such as information from the building management system) can be challenging through these structures. How do we ensure the data is appropriately recorded, interpreted and presented? Do governance structures effectively allow for this process and make sure that the data collected useful and enables risk assessment? So, how should the data we collect from the building be presented? As with many things, it depends. What the intended use of the information is, how is needs to be interpreted and disseminated all matter.

Typical governance structures include water and ventilation safety groups. These groups serve to bring together estates, infection control, representatives from the relevant clinical units, contractors in order to assess risk and make informed decisions. Are such meetings suitable to address risk? The volume of data that must be presented, understood and used to inform decisions is massive, and these meetings are time-constrained. A lot of the processes will be informed by the risk appetite of the organisation. Information may not be available and work may not be possible. As such, appropriate record keeping and reporting is crucial. Taking this all in, governance strategies which to be implemented must be practical, realistic, effective, suitable and sufficient.

Sadly Dr Derren Ready from UKHSA is enjoying a marvellous holiday so we have a recording from him today. We are venturing into the field of community risk assessments and the considerations that are notably different from in the hospital. There are significant challenges, as highlighted by the consideration of the prison system where an outbreak might further restrain the liberty of the prisoners impacting significantly on their mental and physical wellness, thus careful balances need to be struck. In essence, the challenges of the community require a different set of questions to be answered in risk assessment.

In community risk assessment the first stages fall to information gathering and fact checking. Information gathering might focus on the clinical, epidemiological, microbiological or environmental factors. Context of the information should be considered. In public health we often act on suspicion as time is of the essence. In the initial stages there is often simply anecdotal information and there is a need to all the facts to be checked through this dynamic process.

UKHSA bases its risk assessment of five key areas. The first of which is severity which is the seriousness of the incident in terms of the potential to cause harm to individuals or to the population. This is graded from 0-4 where 0 has a very low severity like head lice in a school whilst class 4 are extremely severe illnesses which are almost invariably fatal, like rabies or Ebola virus outbreaks. The second area is uncertainty, how sure are we that the diagnosis is correct based on epidemiological, clinical, statistical and laboratory evidence. The third area is the likelihood of the organism spreading covered by an assessment of the infective dose, virulence of the organism, mode and routes of transmission, observed spread and susceptibility of the population. Again the areas are graded from 0 to 4 allow qualification of the potential risk. The fourth area is intervention, what could be done to alter the course of the outbreak? This ranges from minimal, non invasive procedures like handwashing to an urgent mass immunisation campaign or withdrawal of all contaminated food products. Clearly some outbreaks don’t lend themselves well to specific interventions an example would include responding to a cluster of vCJD disease where remedial intervention is particularly challenging. The last key area is context. The easiest way to consider this is to think about the broader environment in which the event is occurring. Factors like public concern, attitudes, expectations, strength of professional knowledge and politics have the potential to influence decisions about the appropriate response to an outbreak.

The best way to approach this complex process is through the use of a dynamic risk assessment where the risk assessment is continually reviewed throughout the outbreak. This allows UKHSA to make the best possible decisions based on the best information available. These dynamic risk assessments can be classified an routine, standard or enhanced based on the response required to an event. The take home message is very much that risk is not static and we need robust frameworks to ensure we make the right decision at the right time.

In our final talk of this morning, we have our own soon to be Dr Sam Watkins from UCL/UKHSA. Sam’s research interest in detection of surface based pathogens in the hospital. Surfaces can be come contaminated and play an important role in the spread of infection around the hospital. Once considered tenuous, the role of surfaces in the persistence of healthcare associated infection is now well established for several pathogenic organisms. The current standard is for surfaces to be visibly clean but there is no guidance on assessment of microbiological hygiene of surfaces. It’s extremely important to remember that just because something looks clean, doesn’t mean it isn’t crawling with bugs! Again, we must consider that a one size fits all approach cannot be enforced across the NHS as we have so many different situations and patient requirements.

Sam’s research focuses on development of new tools for assessing surface-based transmission risk. Surface sampling can be many different things from contact agar plates, to specific swabbing or sponges, to PCR identification of specific viruses in a outbreak scenario all of which have different purposes. All of this information can help support clinical risk assessment and the actions of infection prevention and control. Currently surface sampling is most commonly used as a retrospective measure after a clinical incident during outbreaks. Sadly there is little guidance or framework in place to guide process in this area. Furthermore, the identification of a pathogen on the surface doesn’t provide sufficient information on if this is the cause of the outbreak. Sam’s work has been to gather prospective evidence gathering through surrogate markers which mimic a microorganism in the environment without posing any infectious risk. In Sam’s work, he has been using cauliflower mosaic virus across an outpatient and inpatient haematology oncology unit. Three markers derived from the genome of the cauliflower mosaic virus were used and inoculated on various risk level surfaces. After 8 hours the swab samples were collected from pre defined sites. The movement of the surrogate markers across the unit were investigated over the course of five days. Within 8 hours there was widespread movement of the markers across the outpatient unit. A slightly less dramatic spread was noted in the inpatient site. From this we see that there is huge variability in the dissemination of markers, markers deposited on high risk sites where identified in a greater number of places. Paediatrics certainly adds an additional dimension to this work, with children spreading viruses through an exciting game of hide and seek in the department! An important take home message here is that a one size fits all approach is unlikely to be successful, given the highly varied nature of clinical settings. A unique approach to surface-based transmission risk assessment and mitigation may therefore be needed.

With the morning session drawing to a close. We look forward to a delicious lunch, more coffee and interactive case based discussions this afternoon!

If you want to find out more about environmental infection prevention and control and future events you can check out the Environment Network here. Girlymicro has also previously posted about risk assessment and the role of the environment in healthcare settings, links to more posts can be found here. The main theme of the day was that we all need to get out of our silo’s and talk more, so let’s start that change by being bold, starting conversations and getting out of our boxes!

All opinions in this blog are my own

Tales of a Recovering Workaholic: Talking about the darker side of success

I’ve been thinking a lot about pathways in healthcare lately, from having conversations about T-levels and apprenticeships this week, to equivalence and Higher Specialist Scientific Training (HSST) posts. It’s made me reflect a lot on my own training pathways and the fact that the majority of the advice I received was that the only option, in terms of approach, was to work harder and do more. Now, don’t get me wrong, there is some merit to that, and there is also some truth, but I had it drilled into me that you can’t be successful if you do a 9 – 5. You must always do more. You must always over deliver. You must always be adding to and diversifying your CV.

This advice and approach has been key to me developing into the person I am now. I am objectively successful and so grateful for the support I’ve received along the way. I have the long dreamed of Consultant post, and my dream job. I was made a professor within 10 years of finishing my PhD. I’ve held multi-million pound grants and have over 50 publications. The other side of the coin is that, despite being exhausted, I can never sleep for the number of things I haven’t finished, and I constantly feel like I’m not doing or achieving enough. I’ve also written before about the impact of my anxiety levels when I’m tired or try to step away. So, as new starter season comes upon us, I wanted to take a moment to really talk about the messages we are giving our trainees, and ourselves, to think about how true they are for current training opportunities and what we can do better for those that follow us.

Let’s start with a bit of history and the messaging that we used to focus on as part of training

Goal orientated view of the world

During my first week as a trainee Clinical Scientist, I was sat down and told that it was an 11 year training scheme to Consultant, but it was up to me to put in the work and make it happen. Well, I worked pretty damn hard, including not having a weekend off at one point for 3 years, and it still took me 16 years. Does that make me a failure? I don’t think so. Does that mean that I should have worked hard to make it happen in 11? I’m not sure of how I could. In fact, I don’t know of anyone who made it happen in 11 years. Of the 4 of us who started, only 3 are now Consultants, and we were a pretty committed bunch. So were we all set up to fail?

The whole scheme was designed with that 11 year target in mind. I understand it from a strategic point of view. There are a lot of boxes to be ticked. Our situation was made even harder as there were only 3 years’ worth of funding for a scheme that required 4 years of professional practice to gain registration. That meant you also had to prove yourself worthy and useful enough that someone would decide to fund you for that extra year. Otherwise, everything had been a waste, and you would walk away unregistered and unlikely therefore to get a job.

My main problem with this approach is that it doesn’t really allow scope for exploration, and it really doesn’t allow time for creativity. It trains you into the ‘onto the next thing’ approach. I certainly had no time for celebration or reflection between stages. I was always trying to make sure that I was useful enough to remain employed, and in later stages, as it took me 13 years to be made permanent, I had to also ensure I was bringing in sufficient money to cover my salary so I would be kept in a job. It also means that when you finally do get all those boxes ticked and get your dream job, you are so trained into the tick box way of life that you are left searching for what the next box should be, rather than embedding and celebrating what you have achieved.

There is nothing that cannot be fixed if you work hard enough

When I started work, I used to read a book at my desk during my lunchtime, like I had when I worked at Birmingham City Council. It would always be some variety of fiction novel. I came into work one day during my first few months, and a pile of textbooks had been left on my desk with a post-it note suggesting that maybe I should read these instead. The implication, to me, was that it was not acceptable to have downtime, that any moment I had should be used to continuously work and improve myself. In short,’I must try harder’ ‘I must work more’ in order to justify the privileged position I was in. If I wasn’t going to lunchtime talks, the time should be used for other improving activities.

I also remember clearly listening to amazing female Healthcare Scientists talking at events about how, to achieve as a woman, you always had to work harder and do more than anyone around you. It was made very clear that it was required to constantly go above and beyond if you wanted to reach their position, if you wanted to succeed, if you wanted to make a difference.

The messaging has always been pretty clear. No matter how hard you are working, it probably isn’t enough, and you must work harder. Otherwise, you will fail and let everyone who had faith in you down, as well as yourself. If experiments fail, you don’t go home, rest and reflect, and come back tomorrow. You stay and set it up again. There were just too many midnight finishes to count during my journey to Consultant. If you want it, you will just work harder until it happens. I submitted my PhD a year early in order to achieve FRCPath whilst on my fellowship. At the same time, I took a PGCert in education because I recognised that it was important for my career path and my interests. Looking back, doing those three things simultaneously was foolish beyond measure. At the time, I thought I was just demonstrating that I had what it took.

Effort must be continuous

At the very start of training, I remember sitting over a bunsen burner crying. I was so ill, but no one around me ever took any time off sick, and it was just not considered to be OK. Eventually, I was sent home as I just couldn’t breathe, but it was very much ‘see you tomorrow’. Having an ‘off day’ was not something that happened. The hard earned truth I’ve learned to accept is that my best looks different from day to day. Some days, I could take on the world. Other days, I struggle to crawl across the line at the end of the day. Especially with a health condition made worse by stress, the idea that I can just ignore it, carry on, and always achieve amazing things every day is sheer madness. This was how I tried to work, however, and it took seniority and growing older to come to terms with the fact that this was just not achievable.

The thing about seniority is interesting. There is something about seniority and being able to give yourself permission to do things differently, which is worth mentioning. That’s not the real difference, though. I think the real difference is in the expectation setting. I try to be the person who gives others permission to acknowledge that some days are harder than others. Who checks why people are still there when they should have gone home. Doing this for others has the side benefit of reminding me that sometimes it’s OK to also do this for myself. It is not possible, nor is it necessary, to work at 100% all of the time. There will be days when you absolutely need to bring it, but there will be recovery days when what you should do is catch your breath, and if possible, do some reflection in order to make things better long term. A career is a marathon and not a sprint, after all.

There is no room for failure

This one isn’t just a work thing. It’s definitely a family thing too. My father is infamous for saying that no child of his has ever failed anything, and we weren’t about to start now when I was worried about FRCPath.

The Clinical Scientist training programme has always been competitive. Getting into the programme was competitive,  but even when you were in it, my experience was that the programme itself was pretty competitive. The people on it were used to being at the top of their class, and I experienced a fair amount of posturing throughout my first 4 years. Far from being tackled and a focus placed in peer support and collaboration, I feel like the rhetoric around the programme added to this. The focus on there not being enough places for us all to get posts when we finished, and the constant commentary on only the best of the best being able to get Consultant posts, placed us in direct competition with each other from day one. Therefore, you couldn’t talk about challenges for fear of disclosing weakness that would impact your future. That atmosphere is one of the reasons I’m so passionate about talking about the reality of the job on this blog, both the highs and the lows, as I didn’t have any way to normalise my experiences when I was training and in the midst of them. I hope posting will help others in finding a benchmark for ‘normal’ that I didn’t have.

Even on a day to day basis failure was not an acceptable part of training. To this day, I remember that one of my fellow trainees reported a NEQAS result (part of a quality control scheme), and she got it wrong. The result got reported, and the department lost a point on the national scheme. In reality, it should have been checked by someone else before it went out, but it happened. The virology consultant at the time never spoke to them again. We would sit in joint tutorials, and he would ask a question, he would then wait for my response even if I was just repeating what my colleague just said. He would respond to my answer but not theirs. There was never a review of what had happened and how the mistake had occurred. There was no acceptance of the fact that being part of a quality scheme is there to support learning and to identify where improvements can be made. There was just a long-term change in the way that trainee was seen and how they were then supported. It was a clear demonstration of what would happen if a mistake was made and that it would impact how your working life would be from that point on.

Quitting is not an option

The same trainee went through a hard time during her final year. She basically spent a lot of her time crying, and the response was that she was allowed to come in 30 minutes late. She started to see a therapist, and even though we never met, I owe that therapist a lot. Her therapist pointed out that in the three years she had been in post she had never been out for a cup of tea with a colleague, so she was given homework to ask someone out for tea, and she asked me. This was a real turning point for me. We went for tea, and we had a real conversation about the things that were both hard and good. It was the first time that I felt less alone. It was also the start of a conscious decision I made to take people off site for tea, to support better conversations, that I’ve continued to this day.

Later that year, she walked away. She made a decision to go a different way. It took enormous strength to do it, and even now, I have enormous admiration for her. Until that point, I hadn’t known anyone make a decision that prioritised their wellbeing rather than the CV tick boxing. The general attitude was that Healthcare Science is a small world, and you were incredibly fortunate to be a part of it. It was so hard to get into, and you had put in so much that you would be crazy to walk away. There was judgement linked to failed experiments, let alone walking away from the programme. Seeing someone break that mould was incredibly powerful.

The truth is none of these messages are entirely true, so how do we do a better job of messaging for current training programmes?

Training is just that, a learning programme, a time to explore, fail, and reflect on those failures in order to learn to do things better. If the messaging I experienced as a trainee now feel less than ideal, what messages should we be encouraging? I’ve been having a think and these are some that I would like us to have better conversations about:

We are more than the sum of our qualifications

Not everyone is going to become a Consultant.  Not everyone is going to get FRCPath and a PhD. You know what, that’s perfectly OK. It doesn’t stop you aspiring for those things if that’s what you want. However, our trainees are not in a Hunger Games style competition to be the last one standing. More than that, how good you are at your job is not dictated by how many qualifications you pick up along the way. Some of the most amazing Biomedical Scientists I know and have the privilege to work with don’t have a masters degree. It’s OK to be a brilliant band 7, and be satisfied and fulfilled by the role you have. Your qualifications don’t define your worth, and it’s OK to make choices that aren’t about playing CV bingo. It is also OK to decide that those things matter to you, you still aren’t defined by them. They have the value you choose to give them.

It’s OK to pause and reflect

No career is a straight path, no matter how it looks from the outside. There will be bumps along the way and the odd hill/mountain to climb. You will reach the destination better for it. You will be able to handle the journey a whole lot better if you allow yourself time to pause and reflect along the way. A big part of development is about making time to reflect on where you are and where you are going to, but also asking the big questions about whether those decisions and reflections you’ve made previously are valid for where you are now. You will be working for decades, and the decisions you make in your 20s are unlikely to reflect the decisions you might make in your 40s, so making time for active reflection isn’t a luxury, it’s an essential part of a professional career.

Knowing when to change direction requires courage

In many ways, I’ve been pretty fortunate, the things that I’ve wanted have aligned with my values and have stayed pretty consistent. This could easily have changed, however. I suspect that if I’d been able to have a family, my focus may have altered somewhat. Knowing when to change your focus or direction is important. This a balancing act between knowing when you just need to double down because things are getting difficult, or when you have truly shifted as a person and that you have to change direction to reflect this. Mentorship and coaching can really help with both this and the reflection that may get you to that moment. Acknowledging that continuing down a path ‘just because’ may not be the right thing and that it requires courage to sometimes jump off a cliff and make a big switch is a step that may require additional support.

Your value is not defined by your productivity

This is the one that I struggle with most and therefore know I probably fail to provide the best leadership around. I often feel that ‘I’m do what I say’ not ‘do what I do’ in this area. I often feel defined by my to-do list, and when that gets out of control, as it often does, I place a LOT of judgement on myself. The thing is, if I get hit by a car tomorrow, no one is talking about my to-do list failures at my funeral. I hope that they will talk about how I made them feel, and maybe even this blog. It is hard, but we can choose what defines us. You have that power. One of the reasons this blog is ‘Tales of a recovering workaholic’ is because I recognise I need to change, and I’m hoping to do a better job of playing this on forward and encouraging our trainees to be defined as well rounded individuals with interests outside of work. We need to encourage a holistic view of value in ourselves and others.

There is no prize for working the hardest

The biggest lie I felt that was embedded in my original training programme was that if you just worked hard enough and ticked the required boxes, the prize was there at the end of the race. The hard truth is working hardest does not get you the job. Ticking all the boxes makes the outcome more likely, but it doesn’t guarantee you anything. There is no prize for the most midnight finishes. Trust me, I’ve done enough of them to know. To a certain extent, the prize for working hard is more work. If you set the bar at working most weekends, then your work just expands, so you have to work most weekends in order to keep on top of everything. If you require external validation, like me, this can be a really dangerous game to get into. If we see this in our trainees or ourselves, I think it’s important to recognise and actively find other ways to find that validation before it becomes built in or results in negative consequences.

The next generation of trainees deserve to benefit from the experiences of those that came before, both in terms of knowledge and in learning how we could do it differently. The working environment has changed, as have our trainees and training pathways. By thinking more about our messaging we can make the work place right now more suited to where we want it to be, rather than relying on chance to make it better. Everyone has a role to play, but we, as leaders and educators, should be prepared to lead by example and own the change we wish to see.

All opinions in this blog are my own

Greetings from the Laziest Girl on the Internet: Living with a mind that won’t stop in a body that doesn’t want to begin

I woke up at 5 this morning, the alarm wasn’t set to go off until 6:15. I am desperately tired and in need of more sleep. Instead of allowing me this simple luxury my brain decided to a) run through an experimental protocol, b) draft a paper I need to write, and c) plan a conference presentation. Sadly, my body wasn’t in alignment with this and so none of it has been written down or recorded anywhere. I am therefore exhausted still and have no concrete outputs to balance it out. I’d like to state this was a one off, but it is in fact my life and daily existence.

People often ask me how I manage to ‘do’ so much. The sad fact is that I really don’t think I manage to ‘do’ very much at all. I’m always a chapter behind on my ‘to do’ list. That combined with the fact that I only manage to get as much done as I do because Mr Girlymicro keeps our lives together by making everything happen at home, means that I thought I’d write something that talks openly about what the reality of having a mind that just doesn’t stop looks like.

I only have 2 speeds

I think those people who think I achieve a lot only see me in ‘doing’ phase. Running around spinning multiple plates at the same time and being totally ‘eyes on the prize’ focused. The other side to this is that when this Duracell bunny phase is over, I become the sloth girl who inhabits the sofa and doesn’t contribute to house work or the want to leave the house. The challenge is that work generally gets the Duracell bunny which means there is very little left over for real life. Hence Mr Girlymicro deserving the husband of the year award 15 years running, and the fact that I need to find a way to split my energy better.

My mind can’t switch off

One of the reasons for the enormous to do list, is that although my body switches off, my mind really doesn’t. I would really love it if it did. Today is Easter Monday, it’s before 9am, and I would really love to be able to sit and chill out. Instead I’m writing this blog as my mind is so full of stuff that this is my equivalent of relaxing as it enables me to focus, and thus relax a little. I don’t know if this is how everyone lives? I really don’t. I have so many thoughts, I remember so many things I should have done, things I should be doing. My mind can make my life a less than relaxing existence. Lovely Mr Girlymicro has brought me some Lego for later though so that I can use it to help, as the process of doing something whilst watching a movie or listening to an audio book, is basically my relaxed happy place. It’s important to have a strategy when my head is spinning out of control.

I find it very uncomfortable to only do 1 thing at a time

This leads me onto another thing. I need to be doing at least 2 things at once to feel comfortable. I’m writing this blog whilst watching CSI on Netflix, later I’ll be putting together Lego whilst enjoying a movie, I even need an audio book to sleep. One of the reasons I’m so happy to have my little bathroom office is that I find it really challenging to work in silence and so it means I can have music or a book running as background audio. I really find it helps me focus. The advantage to this way of living life is that does it enable me to plan talks in my head whilst doing other things, or to plan a text book or blog outline whilst writing a policy. This adds to my ‘to do’ list but also helps keep my head above water when I’ve made too many commitments.

I’m physically lazy and don’t pull my weight

For all that my mind is active I am physically lazy. I always joke that I was born to lounge on a chaise lounge with a book in my hand surrounded by my library with someone to bring me Darjeeling on request. I know that I must be challenging to live with. I get so focused on things, that without adult supervision, I have a tendency to forget to eat or drink, one reason that I am much healthier when I work from home. When I work on-site I tend to come home in a ball of flames, exhausted by my working life and physically broken, and therefore contribute negligibly to doing any form of physical chores. I’m working on it, but saying that, whilst Mr Girlymicro is working upstairs here I am writing this blog instead of tidying the kitchen. I did say he deserves awards, and I am a work in progress.

My mind doesn’t let me rest

One of the other factors that contributes to my physical laziness is that I am so tired all the time. I rarely get a decent nights sleep. If I wake up between one and three to go to the bathroom, my brain kicks in as I’ve had just enough sleep. It’s then fully engaged, whilst my body remains sleepy, with things I should be doing or random thoughts. The same is true even if I get back to sleep, I rarely if ever manage to sleep to the alarm. I do all the tips that everyone talks about, I keep a notebook by the side of my bed, I make notes into this blog so get things out of my mind, but I find switching off really hard. Some of this is because I should probably just take some painkillers/antihistamines, to manage other things, but some of it is definitely the fact that my brain just doesn’t want to play normal.

I am a starter not a finisher

Another side effect of having a mind that is constantly full of ideas, is that it can be challenging to bring any of them to completion. I am very much a starter not a finisher. Finishing anything requires a lot of active effort, otherwise I have a tendency to get distracted by the next good idea that comes along. I think it’s one of the reasons that over the years I’ve become slightly obsessed about keeping my promises and deadlines if I’m given them, even if it means I work weekends and evenings, as I’m hyper aware of my natural tendency to drift. If I make a commitment I can be pretty over the top and harsh with myself about delivering on time. As a people pleaser, this has gotten me into trouble in the past due to over committing to too many things. There have been a lot of very late nights and lost weekends. These days I’m trying to not over commit, whilst using this particular fear of failure to ensure that I still finish things on occasion.

I find focusing on being in the moment incredibly challenging

I am aware that some people are able to really ‘be’ in the moment. When they achieve something, when they have successes, they are able to really be fully present in the moment and enjoy the depth of emotions that that presence achieves. Don’t get me wrong, I enjoy the moment, but my brain is always onto the next thing. I’m always planning and looking forward. In many ways this is a really useful trait, but it means that I’m pretty rubbish at stopping and smelling the roses. I think this is another contributor to why I find it so hard to relax, as even when I’m having a lovely time I’m planning for the next thing. When I’m on holiday, I find it hard not to be planning for how I need to address work when I get back. When I’m at work, it’s always about how to keep us moving forward, and what needs to happen next. I need to make more run for tea 🙂

I spend my day being reactive when I would love to be visionary

My tendency to plan is one of the reasons that I find the current state of the NHS and my role within it so stressful. I want to be planning how to make us better, but because we are still recovering from the pandemic, even if the outside world has moved on, I spend a lot of my time still in reaction mode. It’s one of the reasons that research is so very important to me. In that aspect of my role, as well as in education, I feel like I can be focused on how to make things better and move things forward, whereas that can be more challenging clinically. It is why I love and value the different aspects of my role, education, research and clinical, as they balance each other off for the different needs that I have personality wise. It’s why my role is perfect for me and I’m so grateful that I have been able to develop it the way I have.

I feel I should be doing so so much more

All of this leaves me with a continuous general underlying feeling that I should be doing so much more, that there is so much more to do, and that I need to be better. There’s a lot about this which is good, especially when I was training and it could be channeled into ticking off the necessary boxes. Frankly, it was also easier to work full force and recover when I was in my 20’s and 30’s. I don’t think I had the self awareness, or self reflection skills I have now to understand my drivers in the same way back then. I also don’t think I had the self forgiveness to handle my lack of perfection and therefore be open to change. Now, although looking in the mirror and seeing my flaws can be challenging, it also inspires me to be better and I try to treat myself with the kindness I would offer to others. All traits have a light side and a dark side. My brain means that I am more physically broken and can make the lives of those around me harder by not contributing as much as I should. It also enables me to create change and make the lives of others better. It has been the enabler and the driver to allow me to reach where I am today, and to do things like start this blog. Although peculiar, it is of more benefit than it is harm, and after 44 years in each others company, we have finally reached an en tant cordial, where we still strive for improvement but also live in acceptance of the reality of what the day to day looks like. So my advice, learn to love yourself for who you, whilst striving to be better.

All opinions in this blog are my own

Me and My Bathroom: Being an adult scientist has way more to do with bathrooms than I’d expected

Last week, I was lucky enough to be the Lord Mayor’s Colloquies (an academic conference or seminar) on water and sanitation, where the wonderful Dr Susanne Surman-Lee was speaking. It was an event sponsored by the Lord Mayor and supported by the Worshipful Company of Plumbers.

What has this got to do with bathrooms I hear you ask? Is it because it was on water and sanitation? Is it because these things impact healthcare design? Or are linked with infectious diseases? Is it because of the LAKANA Mali study? You’d like to think, but actually the trigger for this post was none of these things. It was triggered because I have a habit of hiding in bathrooms.

Hiding in bathrooms

I have posted before about networking, and that I’m not a natural in this regard. I have over time developed tools and approaches to aid me, but I still don’t love it. Now for a confession, and to be honest I genuinely don’t know if this is just a me thing as I haven’t really talked about it. Sometimes when I just can’t face networking, I hide in the bathroom of wherever the event is taking place so I don’t have to be in the room until just before the event start so I don’t even have to try. I’ve hidden in some pretty Class A bathrooms in my time, at the Houses of Parliament, at fancy hotels and most recently at Mansion House.

Some days, I just can’t face the sea of people and trying to come up with something interesting that I can bring to the conversation. It is especially bad when entering rooms when I just don’t know anyone or at least anyone well. Occasionally, my game face just fails me and so I find myself locked in a toilet cubicle negotiating with myself about what point I will leave in order to still look like I’m arriving in a timely fashion and with a window to grab some tea.

The negotiation is also about convincing myself to not a) hide at the back of the room, b) just call it quits and go home, and c) look confident and like I haven’t been hiding in a bathroom when I enter the room.

The negotiating doesn’t end here. Many years ago I made a deal with myself. I am allowed to hide in the bathroom, but only pre-event. Once I make it to the room I am not allowed to leave without speaking to at least one person I don’t know. It doesn’t have to be extensive, but it has to be a deliberate act of networking. One of the reasons I find this bit easier is because post event, at least, the one thing I have in common with the other attendees is that we’ve just engaged in the same activity. So that’s the rule, one person, one conversation before I’m allowed to leave. I don’t know if I’m the only one that has these types of rules, but now you all know if you see me hiding out in a bathroom, there is a reason why.

Developing a more than normal interest in bathrooms and water

You won’t just find me in bathrooms at events, however. Working in IPC has waaaaay more to do with bathrooms than I could ever have imagined before I came into post. From overflowing toilets to drain flies, we deal with it all. We often joke that we don’t know which members of the team are Mario and which are Luigi, as even when it isn’t an IPC issue, we still get all the plumbing calls.

As time has progressed, I’ve developed strong opinions on a wealth of topics that I never thought would hold meaning for me, from sink design to tap choice. I’ve also learnt a lot more about IPS panels (the panels at the back of your sink) and TMVs (thermostatic mixer valves) and how both can impact on other areas, such as my need to revalidate my specialist mechanically ventilated rooms.

One of the key things I’ve learnt, as well as being open to continuously learning, is that relationships in this area are key. This is an area where you need to be able to ‘phone a friend’. Friends aren’t just other people in IPC. You need to build relationships with engineers and designers, as well as those people in the lab who can talk you through your water-based results. You simply can’t do this one alone. There are too many factors. Collaboration is key, and the sooner we recognise we can’t do it alone, the more impactful we will be.

Promoted to a bathroom

I don’t know if there’s any meaning behind it, or whether it is just an amusing coincidence, but when I finally got to a point in my career where I was allowed my own office it turned out it was a converted toilet cubicle. My office still says on-call bathroom on the door, alongside one of my favourite things the team have ever given me, my Dame Elaine sign (they always joke it will happen one day). It is a rather compact space, but I love it, and at least they remembered to take the actual toilet out.

The irony of a blog post that starts with how much I hide in bathroom cubicles then discussing how my office is now one is not lost on me. Quite a lot of people don’t like it as a space, as it has no natural light or any ventilation. I don’t know if it’s because I’ve been hiding in bathrooms for way longer than I had a bathroom office, but I find it a really comforting space. I like the lack of distractions. I like being able to spin my chair and reach for anything I need. I like being able to listen to peppy music whilst I work, as I hate working in silence, and not having to worry about bothering others. To me, it’s sanctuary.

Being considered a bathroom expert

One of the things I didn’t realise when I started out as a Healthcare Scientist is how organically interests grow and end up turning into something more. I started involving myself in all things built environment and IPC, because I wanted to understand it better. I wanted to learn more. As time went on that wanting to learn led me to develop more and more questions, as I found gaps in the literature and questions I couldn’t find the answers to. Maybe because I am a scientist, those questions led me to create studies and collaborate with others to gain knowledge that not only solved some things but also created more questions. I’ve also had the painful experience of making bad decisions based on a lack of evidence to enable me to make better ones. Therefore, I think this area (water and water safety) is one that is often overlooked and yet is critical to all healthcare and healthcare environments.

One of the reasons it’s so easy to make less than ideal judgements and decisions in this area is that IPC teams get so little training on this. Most will know something about Legionella pneumophila and Pseudomonas aeruginosa, but very few will know much about other key organisms, such as atypical mycobacteria or Elizabethkingae. What can feel like fairly low consequence decisions based on aesthetic appeal, such as which tap you prefer, can have significant consequences down the line which might not be seen for years. This can make it hard to tie up cause and effect in order to lead to improved learning without external support.

I never aspired to, or meant to be considered an expert in this area, but somehow I have accrued some level of knowledge by being in a Trust that is always building, and having stayed in one place for 20 years to see the cause and effect in real time. For the same reasons, I’ve also published a few papers linked to ways to improve water hygiene, although only a handful.

The main thing I’ve done is establish the Environment Network as a way to share learning and talk through challenges, and more recently, a course that sits alongside it to help support those who are interested and don’t want to make the same trial and error mistakes that I did. I am far from an expert in reality. There’s too much to learn, and the landscape alters too quickly. What I am is intellectually curious and determined to try to learn enough that every decision I make it better than the last one.

Bathroom based recognition

I started this post talking about a Worshipful Company of Plumbers sponsored event at Mansion House and my bathroom based adventures. I thought I should finish it by telling you why I was there and how this transpired in case any of you would be interested in joining me at future versions.

As I said, there don’t seem to be that many people who work clinically who are interested in water safety, although I’m pleased to say the number is increasing. There are, however, amazing women working in this area from the microbiology perspective, women like Dr Susanne Surman-Lee and Elise Maynard. The brilliant thing about these women is that they are truly interested in engaging with others and also raising up other women. I first met Susanne 17 years ago as a trainee when she was working at UKHSA, she won’t remember the event but she made a definite impression on me, and I’ve known Elise for over a decade. They are my ‘phone a friends’ when I need expert advice. They also lead on a bunch of different guideline writing groups in relation to water, and over the years have been kind enough to include me so that these groups, which are usually fairly heavily engineering led, include a clinical perspective.

Over the years, we have written a few BSI guidelines together, and the one that I think is most useful to those of you out there in IPC is this one, BS 8580-2:2022 Water quality. Risk assessments for Pseudomonas aeruginosa and other waterborne pathogens. It has a wonderful table at the back from Elise that contains all of the kinds of organisms you are aiming to control and if there are any specific areas to be considered, such as Klebsiella pneumoniae and sinks. We’re currently writing a new one to help people make sampling based decisions, and one on atypical mycobacteria should hopefully start later in the year. Susanne also organises the Royal Society of Public Health water webinar series, and I’ve been fortunate enough to deliver a couple.

All of which ended up with me being here:

Worshipful Company of Plumbers Livery Ceremony May 2023

In 2022, I was asked if I’d consider becoming a Liveryman for the Worshipful Company of Plumbers, linked to my work on water and women in leadership. It’s been a fascinating process, and at some point I might do a blog post on it. Needless to say, I agreed and in May 2023 I was clothed in the Livery. One of the great things about joining has been to meet so many people who are also really interested in how we manage water better and differently. There are also so many different perspectives. At the Mansion House event, my one conversion ended up being the leader of a sustainability nonprofit who was interested in using STEAM (science, technology, engineering, arts and mathematics) approaches to change how people think about water. This strikes a bell with me, as some of the challenges in the healthcare setting are around people thinking of sink areas being ‘clean’, whereas they are frequently highly loaded with bacteria and therefore potential risk.

Members of my team now jokingly refer to me as Her Plumbship, and all plumbing queries are light heartedly directed my way. The thing is, in this area, none of us can do it alone. I’m not a plumber (despite what my CV says). Nor am I an engineer, an environmental microbiologist or sustainability expert. If we are to make things better, make thing safer and deliver on key goals like those listed by the UN, we have to come together. We have to embrace the fact that there is no such thing as a stupid question, be prepared to stick our heads above the parapet and be uncomfortable in our lack of knowledge in order to work towards a better shared understanding.

All opinions in this blog are my own

An Uninvited Guest: Food Poisoning and Foodborne outbreaks, who are the villains of the piece?

This month is the start of a painful re-entry into normal life. Normal life in terms of work demands, normal life in terms of commuting and normal life in terms of getting back to not eating party food and leftovers for at least 50% of our meals. Now, mummy Girlymicro, Mr Girlymicro, and I have done our fair share of celebrating over the last few weeks, including eating out at large catered events and throwing our own parties for friends. Clinically, norovirus is now giving us its cyclical peak, and there was also a lot of food related outbreak news over the holidays. I thought, therefore, that I would start this years IPC related posts with one on foodborne outbreaks and the kinds of organisms involved.

Food related sickness and outbreaks can be caused by a number of different microorganisms and through a few different routes. The two main routes are infection and intoxication, and these are related to the organisms that tend to be the causative agents. The foods that are linked to these routes are also different, and if investigating can give you an idea of what you might be looking for, especially when combined with presentation, both in terms of clinical symptoms and speed.

Infection vs intoxication

Intoxication based food poisoning is usually linked to rapid onset symptoms following the ingestion of the food i.e. a matter of hours. This is because the symptoms aren’t related to an infection based process, where symptoms are linked to the invasion and replication process of the organism. There are two main types of toxins, heat stable and heat labile toxins. Heat stable toxins can be problematic, as once present in food these cannot be removed purely by re-heating to an appropriate temperature. Heat stable toxins, such as those produced by Bacillus cereus, are produced when the bacteria are present, hitting the right temperatures then kills the bacteria but the toxins remain. This process can be exacerbated when foods are not rapidly chilled or are left at a temperature where the bacteria could grown, there is therefore a prolonged period when toxins could be produced. Toxin related food poisoning (intoxication) can be caused by both bacteria and fungi.

Infection based food poisoning is linked to the ingestion of the organism itself, and presentations are therefore usually delayed as the organism needs to infect the gut mucosa. Many organisms that produce toxins can also cause infection related symptoms if present in high enough loads, and if suitable temperatures for bacterial kill are not met. Infection based food poisoning can be due to viruses, such as norovirus, parasites, such as E. histolytica, as well as bacteria, and the risks are often related to food hygiene efficiency as well as production factors.

Patient management

Most food related illness self resolves and management is mainly focussed on maintaining hydration and electrolyte balance. There is usually a requirement to undertake a minimum isolation period of 48 hours post symptoms in order to prevent any ongoing risk of person to person transmission, even if the original acquisition is thought to be via a food related source. Isolation may need to be prolonged in relation to certain groups because of the risk of ongoing to spread to others, either through personal hygiene awareness or through work based activity.

Recommendations for the Public Health Management of Gastrointestinal Infections 2019: Principles and Practice has a lot more detail on the main organisms associated with foodborne illnesses and some of these requirements for isolation. I’ve attached a copy below, but the link is also here in case it’s useful.

If symptoms continue for period of a week or are especially severe it may be necessary to take samples in order to identify a causative organism in order to support patient management. When taking a patient history it’s important to capture any patient specific risk factors (see below section on risk groups), travel history, recent event attendance history and details of hobbies (such as preserving) that may impact of food ingestion patterns. Additional individual management options can include antimicrobials (antiparasitic or antibacterial) and for non-bloody diarrhoea without fever antidiarrheal agents.

How do these organisms get into food?

Organisms can get into food from numerous sources. They can be present in the environment in which the food comes from, such as manure that is used to fertilise salad plants can contain organisms, like E. coli, even more so if human waste is used. Food, such as oysters, can be contaminated as part of their life cycle as filter feeders if they are growing in an environment where they are exposed to animal or human waste, and so can harbour organisms like norovirus and become highly loaded. Food can also become contaminated as part of the production or manufacturing process, contaminated from other items that are produced in the same facility, contaminated from the processes, such as the water or preservatives utilised, or from failures in the preservation process that would normally have removed organisms that are naturally present linked to food.

Organisms can also come from the humans involved in the process. Those manufacturing or handling the food may be carrying or infected with organisms, whether symptomatic or not. A Staphylococcus aureus colonised person making sandwiches may contaminated the food they are making. An asymptomatic norovirus infected canteen worker could expose those being served food by unwittingly contaminating food and/or serving implements. In the case of bacteria, low level contamination from those producing the food may then be able to grow up to levels where ingestion results in symptoms if the processes are not well enough controlled.

Food processing and manufacturing

Most food preserving techniques aim to ensure that if contamination occurs during production or manufacturing it is not able to replicate to the point where the organism would cause symptoms in those who ingest them. Many preserving techniques aim to control organism survival or replication/loading via either temperature, cell lysis/resource availability or both. There are two main groups of techniques, either physical or chemical. 

Some of these processes are more prone to risk of failure than others, both depending on the process and where is it being undertaken. When undertaken in food manufacturing, these techniques are usually undertaken under highly controlled conditions using the HACCP process in order to manage some of this risk variance:

Food preparation in the home

Obviously, none of us are following HACCP processes when we are preparing food at home, that doesn’t mean that there isn’t any risk to home cooking. One of the hazards linked to cooking at home can be the home environment itself. I’m still aware of people who wash out chicken or turkey cavities in their kitchen sink, unaware of the droplets that are produced and how they can then deposit on other surfaces, which are now contaminated whilst appearing visibly clean. Other hazards can link to the fact that most of us don’t have access to rapid (blast) cooling, and therefore when cooking big batches of food and putting in the fridge, the cooling process may not be fast enough to prevent bacterial growth. Also, in terms of equipment, I work in IPC and I’m a bit of a control freak so I possess things like meat thermometers, in order to ensure that meat has reached appropriate safe temperatures. I am aware that not everyone lives in this particular world, and so may not have some of these pieces of kit lying around. 

Most of the time if you end up preparing food less well at home the consequences are non-ideal but not massively serious, however, if you have an ‘at risk’ member of your household or visiting then it becomes more important to focus on controlling these risk, both through the food that is brought and how it is prepared.

Food preparation (catering)

We’ve already talked a little about the HACCP processes that are put in place to control risk in formal settings. Catering can be a tricky area of risk, even if undertaken by professionals. It is one thing to undertake catering in your restaurant or a space you work in all the time. Catering however, is often undertaken in sites that are not the ‘home’ of either the professional or the average person. Catering equipment can be hired to serve food in church halls, for weddings or other special events. It can also be undertaken on beaches, in forests and other remote locations with variable levels of power to support refrigeration. This can mean that control processes, such temperature control, are undertaken in atypical ways, such as temperature control using ice packs, which will have variable efficiency depending on external factors, such as ambient temperature.

Home catering for parties also brings risks. I love to throw an afternoon tea party for charity, but that means that I am suddenly trying to put waaaaaay more in the fridge than I normally would. Food may be out on a table for a number of hours. Some of the food may also be high risk, such as cheese or smoked fish, and it will be next to less high risk foods. Also, if you are not used to prepping food for large groups, you may inadvertently increase risks by the order in which food it prepped. That is without the risk of people bringing food to contribute to yours which you don’t know the origins of, or people picking up food with fingers and therefore increasing risk of spread if they have anything onboard.

Food storage

Once all of that catering is done, you are then left with a decision, what do you do with all the food that is left? Do you then try and shove it all in your fridge or freezer? Do you give it people to take home in Tupperware pots? How much have you taken into account the length of time that food has been non-temperature controlled? What does that do to the use by? Is everyone aware of any re-heating requirements or the dangers irrespective of re-heating of intoxication?

Issues with food storage are true not just for party catering, but also for batch cooking, something a lot of us are doing more and more of now the weather is colder and because food it more expensive. Foods like stews and rice dishes, which are high risk for intoxication, are also the kinds of foods that fulfil a lot of batch cooking requirements. It is really important to bear these risks in mind, ensuring rapid cooling and that temperature is monitored appropriately.

This also extends to ensuring that even dry goods are stored appropriately. We’ve all been there when we’ve found the pack of spice that 15 years old. Spices, canned goods and other preserved food have been identified as the source of outbreaks, and even when originally in good condition can become a risk if not well maintained, such as dented cans or if moisture has gotten into packets.

What kind of incidences are we talking about?

Over the Christmas period there have been two well publicised food related outbreaks, one linked to E. coli in cheese and one linked Cronobacter sakazakii (previously Enterobacter sakazakii) in infant formula.

BBC News – One dead after E. coli outbreak linked to cheese

This outbreak was linked to the presence of STEC toxin producing strain of E. coli. This leads to an intoxication that can impact of kidney function. Although not stated, elsewhere it was reported that the cheese may have been made from unpasteurised milk, removing one of the stages used to control organism risk in food production.

Advice for individuals from UKHSA included:

“Washing your hands with soap and warm water and using bleach-based products to clean surfaces will help stop infections from spreading. Don’t prepare food for others if you have symptoms or for 48 hours after symptoms stop.

“Do not return to work or school once term restarts until 48 hours after your symptoms have stopped.”

https://www.bbc.co.uk/news/health-67840758

The other recent recall was linked to possible contamination of infant formula detected at manufacturing. Formula feed outbreaks linked to Cronobacter sakazakii have been noted in the past, with a large outbreak in France being the last large scale event. Infection does not just lead to GI symptoms but is associated in some patients with presentations such as blood stream infection and/or meningitis.

The formula included in this recall is mostly used in healthcare or is prescribed to individuals. This makes it critical as it is likely to have been given to an ‘at risk’ population. Milk related contamination is particularly challenging as heating impacts the nutritional content of the milk and so use of thermal risk reduction is not straight forward. Some hospitals, such as the one where I work, undertake an additional step, pasteurisation, for any formula feeds due to be given to high risk infants because of this well acknowledged risk in order to support infection risk reduction.

BBC News – Baby formula recalled over bacteria contamination fears

Current and Future Perspectives on the Role of Probiotics, Prebiotics, and Synbiotics in Controlling Pathogenic Cronobacter Spp. in Infants
October 2021 Frontiers in Microbiology 12

There are obviously multiple examples every year of foodborne risks linked to contamination at source or HACCP failure, but these are the ones that have been most recently featured in the national press.

Are any groups at higher risk?

Although food related infection or intoxication can impact anyone, certain groups are more at risk of significant symptoms requiring treatment or are more at risk linked to certain organisms in terms of presentation. These groups are your very young, very old, the immunosuppressed and pregnant women. The very young and very old are more likely to need support linked to dehydration, and all 4 groups are likely to be less able to mount immune responses to invasive infection. The immunosuppressed and pregnant women have specific guidance linked to avoiding high-risk food groups because of severity of impact if infection occurs.

One particular organism linked with significant infection risk for pregnant women and the immunosuppressed is Listeria monocytogenes.

Microorganisms 2022, 10(8), 1522

Listeria crosses the gut wall at locations known as Peyer’s patches, and from there invades lymph nodes and blood. Once in the bloodstream, it can progress to cause meningitis/encephalitis by infecting the brain. In pregnant women it can also cross over into the placenta, where it can cause infection in the foetus/unborn child. Foodborne listeria outbreaks have been associated with a wide variety of foods, but are often linked to preserved foods and cheese.

https://www.gov.uk/government/publications/listeria-monocytogenes-surveillance-reports/listeriosis-in-england-and-wales-summary-for-2021

How do we investigate foodborne outbreaks?

There are a number of stages to investigating foodborne outbreaks. Initially, there will need to be some sort of flag to suggest an outbreak event. This is usually a number of people attending GPs or A&E linked to a single event, an uptick in samples positive for a specific organisms that is noted through lab reporting, or any cases of specific reportable organisms which will then get followed up.

Depending on the circumstances, a combination of the following steps will be undertaken:

  • Patient questionnaire (case)
  • Questionnaire of those who attended the same event but did not get sick (control)
  • Sampling and microbiological testing of possible implicated food, if still available
  • Sampling of the production environment, such as factories or restaurant kitchens

Investigation needs to be undertaken to identify the target food or batch as most production facilities will make more than one kind of food and will have multiple batches. If the outbreak is linked to a specific event, multiple types of party or other food is likely to have been available. Getting more information about what those who got sick ate vs the others enables you to narrow down what the culprit might be.

Once you have your questionnaires, it’s time for a little bit of stats. This enables you to calculate something called the relative risk for the cohort. The cohort being all those people who were at the same event, ate at the same restaurant, brought food from the same factory etc. This will include those who became unwell and those who did not. For each type of food or batch you can calculate a ratio of the risk of disease (infection/intoxication) in people who have been exposed (ate that food) compared to those unexposed (decided that food was not for them).

You then get a list of risks for different food types eaten. So if the following food was available at our event you can then undertake the calculation:

  • pigs in blankets
  • mini fish and chips
  • turkey and stuffing roulade
  • mini pavlova (with cream)
  • cheese pinwheels

If the number if >1 then it indicates and increased risk, if RR = 1 then it doesn’t impact on risk, and if RR <1 then there is a risk reduction. So in the case of our party food:

  • pigs in blankets RR = 1
  • mini fish and chips = 0.98
  • turkey and stuffing roulade = 1.73
  • mini pavlova (with cream) = 1.1
  • cheese pinwheels = 0.99

In conclusion………the turkey probably did it!

I hope that’s helpful, I know there’s loads more that could be covered, and if you are interested in anything in particular drop me a comment and I’ll see if I can post a follow up. The main take away is that there are multiple organisms that can cause foodborne infection/intoxication, and whether it’s home or out and about we can all be impacted. For most of us, it’s an unpleasant but low consequence event, but there are are people and populations where the outcomes can be much more severe. So, if you’re ever asked to complete a questionnaire please do so, and don’t ignore those news articles that tell you to throw an item away as it’s not a risk worth taking.

All opinions in this blog are my own

Guest Blog from Sam Watkin: Researcher in a clinical space

As I continue the slow road to feeling more like myself again I thought it might be nice to have a guest blog from the wonderful Sam Walker on some of the things that have been happening in the research Girlymicro world, so you know I haven’t been entirely resting on my laurels and eating copious amounts of chocolate. One of my favourite papers ever is based on the release of cauliflower mosaic virus DNA into a ward space, to support prospective tracking of where organisms go, instead of trying to guess based solely on where we find them without origin data. Due to a number of technical factors this approach to improving environmental transmission pathways hasn’t widely been repeated………..until now!

Sam is a Doctoral Research Student whose research focusses on the development for environmental surface monitoring protocols to inform clinical risk assessments and infection control procedures. His project aims to develop an evidence base for the presence of nosocomial pathogens in the hospital environment, as well as model the transmission of pathogens in clinical spaces. He obtained an MBiol degree from Aston University in 2020, with projects focusing on C. difficile spore germination.

Infection Control Research

“I imagine the swabbing part will be easy, it’s the data processing I’m worried about”. I think I said this about a month before the largest, and final, sample collection campaign in my PhD project. Famous last words.

A little bit about me – my name’s Sam and I’m one of Elaine’s PhD students. I’m finishing off my third year now (crunch time!). My project focusses on developing evidence-based surface sampling guidance to inform infection prevention and control practice. Practically, this involves collecting a range of samples from different clinical spaces and seeing that they can tell us in terms of microbial communities and microorganism dissemination, then using this information to target guidance for designing the most effective surface sampling protocols. In order to best inform this, we designed a study which looks at the movement of microbial surrogate markers through several different wards at Great Ormond Street Hospital. This involved a lot of preparation and many evenings swabbing sites across four wards. As of last week, all this sampling work has finished and I thought I’d share a few reflections on what the experience of conducting research in an active clinical space was like.

Working across settings is amazing!

For many projects focusing on clinical practice, particularly ones relating to IPC, working in collaboration with a clinical institution is absolutely essential. As my project involves collecting evidence from clinical settings to then process and develop into guidance, in my case this work wouldn’t be possible without this collaborative approach. As the end goal of my project is guidance that will inform clinical practice, not only is it important that the evidence is gathered from clinical settings, but it’s essential we understand the routine challenges faced by IPC teams. We can design the best set of guidance with all the technical detail in the world, but if we don’t take into account every day IPC challenges and what implementing this guidance will actually look like, then in a way it would fall flat. Being in the clinical space also opens up the possibility for conversations with the people who live and breathe IPC all day – the hospital staff! Informal discussions we have had over the course of this most recent sampling project have given me completely new insights and ways to view the work we’re undertaking which I never would have thought of otherwise! Getting this insight from working in clinical settings will ultimately improve both the quality and utility of the work we produce.

Stepping out of my comfort zone

As a lot of project is lab-based, the trips outside of this setting into clinical environments can be a bit of a shock to the system. I’m used to, and probably most at home in, a quiet laboratory space with a few other people at the most, maybe the odd visitor and the trusty PCR machines. The majority of the time I make the journey from UCL to GOSH, it’s to meet either with Elaine or other members of the IPC team, or maybe to pick something up from the microbiology labs there. When it’s time to collect samples however, this is a completely different experience.

The units we looked at in this most recent piece of work we did were two outpatient and two inpatient wards, serving different patient populations. One of the first things I really noticed was just how different these wards all were. I knew that there would be some big differences, for example I knew that the cardiac intensive care unit would be a very different experience to the oncology day care unit. What I didn’t necessarily expect however, was just how different the two outpatient wards would be from each other, and how different the same ward could be on different days.

With these differences came a different way to approach the research at hand. For the outpatient units, that often meant waiting until all the bed spaces were free so we could go in and collect the samples from the environment. This wasn’t always possible though, and sometimes we just had to accept that we weren’t going to get all of the samples we set out to gather. This took quite a while to get used to – my inner laboratory scientist was wincing at the thought of lost data points. Being able to put this to one side and carry on was a skill that took a while to master, particularly when sampling with a team. No-one will thank you when you’ve been on the ward for an hour and a half and you propose “just waiting a few more minutes” to see if a bed space will become free. Having that skill to just move on however turned out to be very useful when collecting the data, as it meant we could focus more effort in the areas we could collect samples from.

All this boils down to how the space is used completely differently. The hospital is first and foremost for providing care to patients, and as a researcher I have to acknowledge that I am a guest in the space. Understanding and accepting that we won’t always be able to collect all of the 65 or so samples we planned to on a given day is just part of the process when conducting sampling in the real-world hospital setting. At first, I remember feeling like this may be frustrating when it came to analyzing the data, and that it would make interpreting my results harder due to data gaps. However, looking back on it now, I actually feel it makes understanding the story the data tells easier, and much more insightful. Being able to relate the information we gathered to how the space was used at the time of collection, even where samples could not be obtained, just makes the story all the more applicable to real clinical practice and, in this case, how microbes could move through the clinical space under all sorts of conditions.

Anticipate the challenges

While embracing the dynamic environment of the clinical space is really important for putting data gathered in these settings into context, it doesn’t mean that there isn’t a fair share of challenges with it. Before I began the sampling campaigns, both my supervisors absolutely insisted that I pre-planned every tiny detail. Down to the exact number of extra swabs I would take for each day. And I cannot think of better advice when it comes to performing this sort of work. Planning is absolutely everything. One of the reasons missing some data points during collection didn’t impact the overall quality of the data was because we anticipated that we may miss some points each day, so planned to take extra to account for this. We planned a detailed sampling sheet, so we could not only check off samples as we took them, but could make notes as we went around the ward on the environment to help with the downstream analysis. I cannot stress it enough; thorough planning made the whole experience so much better.

One challenge of conducting this piece of work was the intensity of the settings. I have a very much academic background, having done my MBiol degree and gone straight into my PhD. In other words, I have no clinical training whatsoever. This wasn’t so much of a problem in wards which were not high dependency, however I really noticed this lack of clinical exposure when we did the sampling in the cardiac intensive care unit. I knew it may be a difficult experience, given the nature of the ward we were going in to, but it still was a shock the first day of sampling there. I’m incredibly grateful for the team I did this part of the work with, who had the experience to navigate the space as well as make sure I was alright being in the setting. I think that this support, alongside taking some time to reflect on the overall experience, was invaluable for this particular component of the work.

This leads me on to the other absolutely key point for doing this sort of research – having the right people with you. As academics, we often won’t have been trained in clinical practice. This can not only make some clinical spaces quite intimidating, but also can make them hard to read. For example, without a clinical understanding of what is going on in a bed space, it can be hard to know whether to ask if it’s alright to take a swab of the bed rail quickly, or if you should leave the space and move on. Having people with you who can help read these situations is so important, both for help with collecting the data but also for supporting the researcher. Another massive benefit I noticed was the links formed between me, the researcher, and the ward staff. Having someone involved who has experience in both worlds can really help break down any barriers on entering the space and help everyone understand the work that is being done, and how it relates to the ward.

Top tips for laboratory researchers gathering samples from clinical spaces

So, having said all that, my top tips on performing research in clinical spaces as an academic are:

  • Planning is everything!
  • Anticipate and embrace the unique challenges of this sort of research
  • Have a good team who can support you in the clinical space
  • And finally, get involved! Undertaking research in clinical settings is very rewarding and I would highly recommend it wherever possible!

All opinions in this blog are my own

Clarity of Role and Its Impact: Why knowing and being clear about your professional boundaries matters

This one’s been on my mind for a while, and by posting it the aim is to explore my thinking, not to target anyone or any group. I’ve been seeing a lot of posts on twitter and having a lot of conversations about identity, especially in relation to professional identity, and so wanted to take this opportunity to reflect and process.

I’m going to start with myself based around a non-clinical example of what I’m talking about. I am a scientist who communicates. I am not a science communicator. It took me an age to really get the difference, but the difference is this………it’s about where my expertise lies. I hope that I happen to be a scientist who has some decent communication skills, and it is a subject that I am pretty passionate about. My qualifications and expertise, however, are in the science, that’s where I sat my exams, that’s where I have almost 20 years of practice.  My expertise is in science, not just that, but my real expertise is actually in quite a small subset of science. I took a zoology degree 20 years ago, but I am not a zoologist, that knowledge is old and only at undergraduate level. My expertise is probably in Infection Prevention and Control.

Now, if I were a science communicator, my expertise would be somewhere else. My skills would be around communicating science in general. Many science communicators haven’t worked in science for some time and some may only have undergraduate levels of science specific expertise. What they have, and I don’t, are qualifications and vast levels of experience in communication and pedagogy. These skills enable them to break down highly complex topics and also pitch in a way that I can only aspire to. They have significant levels of pedagogical skills that I can’t pick up by attending a couple of courses, just like they can’t pick up mine by attending a week long course on whole genome sequencing.

So, to me, the difference is where my expertise and knowledge lies. This doesn’t mean that I couldn’t transition from one to the other, but I have to acknowledge that I’d be moving from my area of expertise and therefore would need to rebuild both it and my qualifications to demonstrate skills within a different area. It would be a growth area rather than a straight transition.

OK but why does this matter?

I’ve been reflecting that we are definitely in a period of substantial change within the NHS and one that isn’t likely to stop any time soon. This means a lot of our pathways and traditional professional boundaries are changing with it. I think, in the end, that this can only be a really good thing. (Although I think if it is going to work it needs to be implemented across staff groups with no ivory tower protections). With this change comes fluidity and, because our pathways are embedded, change can occur before we have the processes to keep up.

During this period of change and recognition of different skills and pathways, for instance, the HSST, more Healthcare Scientists working in education, IPC becoming more interdisciplinary and the development of Clinical Academic pathways outside of medicine, clarity is key. I’ve been number one in a field of one when I didn’t know anyone else working as I did in IPC and it was a balancing act. I’ve been through people asking ‘are you one of the nurses’ and hanging up if you said no, but also I can’t claim to be a nurse. If we don’t understand our boundaries, it can be hard to be clear about them with others. If we can’t be clear about them with others, assumptions can occur about knowledge and skills that can lead to potentially dangerous practice or misleading those we’re interacting with. To me, it’s about owning your difference and being open to talking about the benefits it brings, whilst being very aware of when you should defer to someone else.

Labels not hierarchy

I guess what I’m talking about is actually the importance of labels. Now, this may seem a little ironic as I’m not a labels and silos kind of girl, but bear with me. The reason we use labels as human beings is that they enable a cognitive shortcut. One of the reasons that they can be bad is that they come with a bunch of assumed information that is not nuanced, and may in fact not be true. In the case of knowledge and professional roles, they come with an expectation that if you say you’re a virologist, you have a significant amount of knowledge about virology and virological processes. If you say you’re a consultant, you will be assumed to be practising at a certain level with certain qualifications behind you. These labels mean that when we interact, assumptions are made about our scope of practice based on an assumed level of knowledge or experience.

The problem with some of the developing pathways is that the information behind those labels is not yet established and embedded widely across the NHS or for the public we’re interacting with. The assumptions made linked to those labels may, therefore, be incorrect. Due to this it is really important to be clear about who we are, our experience, knowledge and boundaries, not because one label is better than the other, but to ensure that all involved have clarity in order to not increase risk. If you are in a new or developing area/role, the onus is therefore on you, to clearly communicate about you practice boundaries in the absence of a default label.

Asking, where is my expertise now?

Everyone wants to feel like they know what they are doing. Everyone likes it when someone comes to them and asks them to engage in events or answer questions due to perceived expertise. The problem comes when we respond to the request based on the pleasant feeling it creates without self-checking if we are the right people to undertake the task.

Obviously, the risks are not always the same and occur on a continuum. I’ve been asked to give talks on antimicrobial stewardship and have referred on to someone else as it was for a conference, and that’s not my area of study. If that request was to teach an undergraduate class, however, I have the knowledge base and experience to do so if there was no one better available. I would however be very open with the organiser that I might be better placed to speak on a different topic. Being clear about your boundaries in a clinical environment obviously holds much greater importance. I have FRCPath and used to regularly do ward rounds. Since the pandemic and moving entirely into IPC, I haven’t given clinical microbiology advice in the same way. This doesn’t mean I couldn’t run a round, but I would want to re-up my skills before I did so, there is a difference between what I could do on paper and what I would feel comfortable to do in practice.

When I interact with others or get requests, I always run a quick internal check with myself about whether I’m the best placed person to respond. There are tasks that are always best served by having input from multiple viewpoints and backgrounds, and these I will bring back so we can discuss them as a team. There are other things where I will refer to someone else specifically, as I know they have a greater understanding of that clinical practice. I’m aware that this all tied into our professional registration, but I am often slightly struck by how, when people are trying to define a new identity, they try to own the label they want before they have fully developed enough to go it solo. I think this is often the moment of greatest risk in any development pathway.

None of this is about restricting access

I want to be clear that I am truly excited by the change towards more dynamic progression in healthcare and recognition of the skills different professions bring to the mix. I do think that when you are already established within a profession, it can be challenging to go back to actively undertaking that gap analysis and flagging your difference all the time, especially when others don’t necessarily know what your role is or react negatively, as we are used to being the ones in the know. The thing is, the only way that you can establish the new pathway or role is to start the work but be mindful to continue to flag your scope/difference as needed. No one hangs up on me anymore when I say I’m not a nurse or a doctor. People have gotten used to it. They wouldn’t, however, if I’d not been open about it in order to engage with the conversation and just defaulted to their expectations.

It is easy to get drawn into the conversations with some conservative colleagues about whether this is the right direction for the NHS to go in and to feel defensive about it. I think that being willing to engage calmly in those conversations is part and parcel of being a pioneer. To see each conversation as a learning opportunity, both for yourself to communicate your role better and for the other person in terms of knowledge exchange. Change is unsettling, especially when it goes against traditional structures and hierarchies, and it will take time for people to adjust.

You can be passionate about something without being an expert in it

Finally, and just one side thought that is not related to clinical work as such. It is OK to have an interest in something and not be an expert in it. It is OK to say for me to say that I’m interested in science communication but not to claim expertise in it. It is OK to be an interested participant and to want to engage in an area because of the growth that engagement offers. You don’t have to enter every space wearing your expertise as a shield. It’s just worth being honest and open with yourself and others when you do it. Not claiming expertise will open doors to shared learning that you might not otherwise be able to access. We don’t always have to be the smartest person in the room. We should just should aim to be the most able to communicate our purpose and vision for being there.

All opinions in this blog are my own

Holding the Line: What it feels like to be seen as the ‘Big Bad I Said NO!’

When I was a kid there was a cartoon called Stoppit and Tidyup. It was a kids world where the baddy was the Big Bad I Said NO! This particular post was started during the pandemic when I was thinking about perceptions of the word NO but has kind of lingered as one of those things I wasn’t quite ready to get my head around. The last few weeks have kind of shown me it was still relevant outside of the pandemic however, and so this week I thought I would post about what it feels like to be seen as the gate keeper or to be the person who feels like they are holding the line. In essence, what it feels like to be the person who likes to be liked but who has, as an adult, turned into the villainous Big Bad I Said NO!

I have previously posted about the inevitability of not being liked by everyone, and the challenges of speaking truth to power. The thing that’s unique about becoming the Big Bad I Said No is that it can be a mask/hat/role that is needed in all kinds of settings, and the stakes can vary widely – anything from 1:1 relationships to impacting Trust or wider level decision making. It can therefore feel very stressful to manage, and that stress can be protracted when discussions and scenarios go on for months or longer. Having now spent some time thinking about this though, here are some of my thoughts on the how, whys, and inevitable consequences of saying NO.

Sometimes, it’s all in how you say the words

The word NO can feel pretty loaded. The very use of it often brings a feeling of judgement. Worst still, in a world where as leaders we should be trying to bring people with us, it is the ultimate reminder of hierarchy. As a leader, if I have to go there I will just saying NO can make me feel like a failure, as I feel I should have been able to find an alternate solution or compromise. Also, as a previous recipient of NO, it can make you feel powerless and lead to you questioning your understanding of your relationship or the organisational values.

It is crucial therefore, on both sides, to communicate more than just the NO. NO, without an understanding of the values and drivers that led to it can be pretty destructive. So it is important, although the temptation may be to drop the NO and get out of the room, that it comes with context to support the why.

Sometimes, you need to be direct

Sometimes, being a gatekeeper can be pretty uncomfortable. Interestingly, I find it easy with an infection control hat on versus with a Lead Healthcare Scientist hat, probably because patient safety trumps personal feelings. It can be tempting when you are in a position where the NO is going to be hard or challenging to try to say NO without saying NO. The problem with this approach is that although you may leave the encounter feeling less scarred or exposed, it is likely you are also leaving it with less clarity. Worst than this, not only have you said NO, but you also have taken away the recipients’ opportunity to question and gain a clear understanding for their own processing. It may feel easier in the moment, but you are probably just kicking the problem down the line rather than working towards a resolution.

Please note that this sketch has an 18 age certificate

Sometimes, it’s about being clear that you are living your values

I think one of the reasons that a NO and holding the line is easier (although still hard due to the stakes) in infection control is because it so clearly aligns with my core values, and ones that I hope are represented more widely within the NHS. We should all put patient safety first. Therefore, you can respond in a way that you feel enables you to speak to someone else’s shared values. I hope that the same is also true when I speak to people about equity of access, but in truth this one can be more challenging, as sometimes you are asking people to give up something for someone else, this can occasionally overrule this personal value for the recipient.

Sometimes, it’s harder to make that shared value assumption, and so it becomes especially important to share clearly why you are doing something, both from a factual, but also value perspective. This can include things like wanting someone to be in a better prepared position before they undertake training course X so they can get more out of it by starting with a better grounding. It can also be that a change would be better placed after we’ve set it up using pre steps. It’s important, though, that if it is a true NO, not to fall into negotiation, as that can result in confusion.

Sometimes, it’s about showing someone the big picture

Frequently, when I have to say NO, it’s because I have access to information that the other person doesn’t. This may be information that enables me to have a more holistic view of risk or success. When saying NO in these cases it’s crucial to talk someone through that wider picture, not only because it helps them contextualise the NO, but it may enable them to come up with an alternate approach that might result in a YES. I hope that by taking the time to do this it may result in the recipient being empowered when they leave the conversation rather than deflated. Obviously, that’s not always the case, and sometimes, individuals will need time to process the information. At least by investing the time it offers an alternative perspective and hopefully demonstrates that I value both the person and the dialogue.

Sometimes, it’s about showing your thought process

This one is a little bit of an extension of sharing your values and the big picture. In my case, as a scientist however, it also includes sharing data and evidence and using that to explain how I came to my conclusions. I sometimes go too far down this particular rabbit hole, as it’s my comfort zone, and it does not always work.

Some people will respond better to different things. Some people like me respond to evidence, some will respond to patient led and other values, some are pushing a vision, and others will respond if you share the big picture stuff. Knowing who your audience is helps you pitch, but including a bit of everything in your prep and being able to pivot to what is landing best for greater focus is a skill worth developing.

Sometimes, it’s about being prepared to defend whilst maintaining being open

Despite your best efforts to explain and justify, you like me, may end up being pulled into rooms of people who don’t particularly like your conclusion or what you have to say. This is leadership, and particularly in infection control, it’s kind of what we get paid for. Drawing a safety line and holding it is key. Now, that doesn’t mean you shouldn’t be able to re-evaluate in the face of further information. It also means you should be prepared to defend it. You will need to defend your thought process, your evidence and your conclusions.

I have to be honest, sometimes this is the one I find most challenging. Not because I don’t feel able to justify my process, but when the evidence is clear, I can struggle to understand why others don’t see it. It can also be easy to feel like you’re being personally attacked when it is actually just the scenario. As I wear my heart on my sleeve, I can find it hard though. Trying to take yourself out of the process and focus on the role and the reason you are in the room is something that I’ve found can help.

Sometimes, it’s about finding support

One of the other things I’ve found really helpful is to know where your support lies. In my case, that may be Mr Girlymicro offering me a martini as I walk through the door and telling me it will all be OK. It can be having some trusted colleagues that you talk and walk through your rationale with before meetings. Colleagues that you know may be comfortable challenging you in order to help you see gaps or assumptions in your thought process. Sometimes, it’s about knowing who’s going to be in a particularly difficult room and being aware of where their support may lie, so you know who you may count to support your rationale.

A lot of this is about the work that you need to do ahead of time to build your networks, to get to know other people and their values so you can understand their drivers when you are thrust into a gatekeeping scenario. It can be as simple as moving the dial so you know your unknowns and can therefore better prepare for the unexpected.

Sometimes, a no is actually a not yet

The other thing that’s worth addressing is knowing when a NO is a not now, or not this way. If you can work your way through a scenario so that you can see different routes or avenues to the same destination, it may open a different type of conversation. I’ve mentioned some of these things above, but again, it’s about having put in the time to think things through prior to your response. Often, in infection control, it is tempting to take the path of least resistance, when with extra resource or input, a YES may be possible. Checking ourselves to ensure our motivations are correct is always worth doing and making sure that we are open to the presentation of new ideas or new information that might impact our risk assessment or evaluation is key.

Sometimes, it’s just about sucking it up

Recent years have convinced me that you don’t join infection control to win popularity awards, hardly anyone gives us chocolates at Christmas. The job is hard. Leadership is hard. Saying NO and gatekeeping is hard. The thing is, we do it because it needs to be done. Sometimes, it needs to be done in order to not set someone up to fail. Sometimes, it needs to be done for safety. Sometimes, it needs to be done for equity across your workforce or because of resource limitations. Every now again, it has to be done because the request is just not that reasonable, and the person making it either hasn’t considered or doesn’t have access to the big picture. Denying it’s hard doesn’t get you anywhere. Denying it’s hard can lead you to avoid the hard moments and therefore dilute your impact. Someone has to be the gatekeeper, especially when it comes to patient safety. Someone has to be the Big Bad I Said NO! Some days, that person is me, and despite it being hard I think that the world is just a little safer for it. So know you are not alone, but when your moment comes, be prepared to put on your big girl pants and own the importance of being the person who both says and owns the fact that they said NO!

All opinions in this blog are my own

Celebrating National Pathology Week (Delayed): Talking about routes to registration as a Healthcare Scientist

I have the best job in the world, and people often ask me a) how I got here and b) how to get here themselves. Now, I have gone a long and circuitous route as you can see below, so I’m not necessarily the best person to ask, although personally I think the circuitous route had quite a lot of unexpected benefits:

That said, when I was a lass the world was much more straight forward with the routes and options being much more restricted and a much greater need to establish your own pathway. There was only one place where you could register, and that was with the Health and Care Professions Council (which even had a slightly different name), where yo reach registration in 1 of 3 ways:

  • Registration as a Clinical Scientist via the Association of Clinical Scientists (route one) – this was the route I followed as a grade A trainee, which later developed into the STP (Scientific Training Programme) as offered by the National School of Healthcare Science
  • Registration as a Clinical Scientist via the Association of Clinical Scientists (route two) – this route still exists and it involves the following ‘those who may not have completed the formal training associated with Route ONE, but have extensive experience in the relevant field sufficient to demonstrate our competences based on a cross referenced portfolio of evidence, and (if approved) an interview.’ This is usually for those entering the field with a PhD who then spend some time working in the role of a supervised pre-registered clinical scientist with the supervision of a registered Clinical Scientist or medic.
  • Registration as a Biomedical Scientist via the Institute of Biomedical Science

All of these routes led to you being registered with the HCPC and the ability to practice as an independent practitioner. The market place has changed a lot since then however and the profession is now filled with so many opportunities and entry points to permit an enriched career progression. So in order to celebrate National Pathology week I’m hoping to answer some of questions about how to become a Healthcare Scientist and sign post to some great resources that others have created.

Although in many ways I still believe the system was great when I joined, it cannot be denied that there were a number of flaws. There was no pathway as such, it was incredibly difficult to move from a starting non-registration requiring position to registration and onwards. Also, once you had your registration there was no structured progression route. It was hard to demonstrate pathways to Consultant Clinical Scientist posts, Advanced Practice posts didn’t exist, and so it was also difficult to demonstrate parity or equity of access. Thus modernising scientific careers was born, an example is below although it’s been through many interactions since. Many aspects of this are still in place, but some like the clinical academic careers route are still being developed, whilst others like the apprenticeships have been developed significantly further. Other entry routes, like T-Levels in Healthcare Science, didn’t exist at all when this was last updated.

This means that anyone wanting to entering the career now has a lot more points at which they can enter, A-Level equivalent (T-Levels), undergraduate, post-graduate, post PhD. There also routes available to move from stage to stage in a variety of ways. Having so much choice can be a little overwhelming however, so I thought I would try (with the help of the wonderful Dr Jo Horne) to collate some of the different info in one place in case it might help.

Apprenticeships

Apprenticeship standards change frequently and are tweaked based on what we learn and the workforce needs. They are great however as they are not only entry points, but progression points no matter what level you are coming in at. The Level 7 apprenticeship will also soon be a thing, and so for a Clinical Scientist like me, training may look a bit more like it did when I was a grade A trainee. They are also great as you can balance progression with your needs in terms of non-work demands, as you have control about when you choose to access them, permitting a lot of flexibility.

Entry Overview Clinical Microbiology and Clinical Virology

Dr Jo Horne has been pulling together some really amazing infographics on healthcaresciencenews.co.uk in order to help clarify not only the apprenticeship routes, but also the direct entry routes into the various formal and informal training programmes that can lead to HCPC registration. She is also actively working with Healthcare Scientists via her coaching website to help support them in their careers and making career progression decisions.

Other Routes to Clinical Scientist Registration

Finally, I’ve previously posted about my experience applying for Higher Specialist Scientific Training programmer equivalence. This is a way of demonstrating that you have an equivalent skill set to those coming out of the HSST programme, which is a formal training programme to support training to consultant level.

There is an equivalent scheme for equivalence to the Scientist Training Programme, but this isn’t the only route to registration as a Clinical Scientist if you haven’t gone through the formal STP programme. I think there is an understandable excitement and engagement with the STP equivalence programme and I am a big supporter of that engagement. I do however think we have to be conscious of the word equivalence. If the STP equivalence process is about demonstrating equivalence to the STP then not everyone will be able to go down this pathway, as the training they have to demonstrate is very broad and, with the new curriculum, very clinical. This doesn’t mean that they should not be able to gain registration as a Clinical Scientist. As I said at the very start, the ACS route 2 existed when I was training and it still exists now. If someone has vast amounts of specialist knowledge and meets the requirement for having practiced in a clinical setting then they may not be suitable for equivalence, but more than suitable for route two via the ACS. I’ve know a number of candidates put in a lot of time and end up being delayed by going for the more well known AHCS route and struggling, when they would have been much more suitable for the ACS route. I think we need to talk more about these alternate routes, and the ones that are available across the profession to recognise advanced practice, in order to support people applying for the right schemes and not getting disillusioned in the process. The route needed will be varied based on the individual but the end point is the same, and we should therefore embrace all of these options.

Hopefully some of these links will be helpful to those of you who are looking to enter this awesome career, and for those of you who are already working as a HCS, maybe they will inspire you to take the next exciting step in your career. Please let me know if helpful and thanks again to Jo.

All opinions in this blog are my own
Would You Like That Explained in Words of One Syllable? Thriving in the world of a mansplainer

This post is in honour of international women’s day, I hope by talking about this and sharing some thoughts it will make us all more able to stand up for ourselves and support others in moments like the one below, when we encounter the mansplainer in their natural habitat.

I was at a conference last week, and I was struck yet again by the number of questions that were asked that were commentary and not indeed questions. I paid attention, and, in this case, 100% of those undertaking this behaviour were older men. The reason I started to pay attention was because the first session I attended was filled with a panel of young female scientists. The Chair of the panel, however, was an older man, and when this commentary occurred from one of the attendees, instead of shutting it down, he actively participated and even exacerbated the issue. Not only that, but the commentary was also inherently incorrect and was not even helpful. I must admit I found myself becoming pretty infuriated and later found other women who’d been in the room who found it equally maddening. So this week I thought I would channel some of that science rage into a productive place and talk about survival in the world of the mansplainer.

NB please note I recognise that there are also some women that exhibit these behaviours routinely (and we probably all do periodically). In this post I talk about mansplaining as the behaviour and not linked to gender, unless I’m recounting specific personal experiences.

In the interests of full disclosure, I’ve also had a fair amount of men recently lecturing me about what it is I do and do not know, as well as some ‘interesting’ comments on my blog. I therefore may not be feeling as balanced about this topic as I would otherwise. The thing is, it’s not like it is as unusual as it should be, and you would think, therefore, that I should be less bothered by it. In fact, the opposite is true. Now I’m aware and see it happen to others. I’m even less tolerant. I’m pretty fortunate that it only happens to me 3 or 4 times a year to a level that irritates me. It happened less when I became a Consultant, and I suspect that it will happen less (to my face) now I’m a Professor. Even so, with all of these benchmarks of knowledge and experience, it still happens. So here are my thoughts on living in the world of the mansplainer and how we might all work together to make it more tolerable.

Don’t worry little lady

Let’s start with talking about some classic mansplaining that has happened to me. I’m partly starting out with this because I had a really lovely male boss who just didn’t believe that these things happened as no one had talked to him about it. By putting it down here prior to talking about what we can do in response, I hope to contextualise some of what it’s like for any allies out there who have experienced it less as individuals.

My all-time ‘favourite’ example of mansplaining that has happened to me was an email sent to myself and a female colleague that actually started with the words ‘don’t worry little ladies’. The email in question was sent in response to a query about engineering standards. Now, these days I would respond with ‘that’s Professor Little Lady and I am worried so please explain………and what you are going to do about it’. At the time, though, I was completely thrown by how 4 words could effectively minimise my years of experience, my authority to ask the question, and impact my feelings about my ability to follow up. In my defence, I did follow up and insist on further information and a review, but something so small could actually have impacted my ability to do my job and would never have been undertaken with my male consultant boss. These comments, therefore, are not insignificant when, especially in healthcare, they could lead to a reduction in safety. That said, did I escalate? No, did I forward the email to his boss and explain? Also, no. It’s so normal that it never even occured to me. I suspect if I had, it would have just been called ‘banter’ and waved off.

One of my other favourite things (not really) is when I’m called into a room to have a technical discussion, and when it becomes apparent I’m not convinced by the argument, the room full of men call in yet more men, not to enhance or bring more information to the discussion, but because they somehow believe that having more men in the space repeating each others words will somehow intimidate me or force me into conceding that their science is suddenly correct. I do not enjoy conflict and I generally believe it’s bad form to point out the flaws in someone’s argument in front of others, in a way that could be seen as aggressive or embarrassing for the individual. However, if you pull >20 men into a room to lecture me on, for instance how HPV works, when you are neither a microbiologist or have any experience with viral loading or kill, and think that calling in a further 10 will change the underlying fact that I have just finished writing about it for my thesis, my argument is unlikely to change. All that will happen is that I will cease trying to cover up my level of knowledge in order to play nice and I will quote papers and research at you until you let me leave.

Have you thought about?

One of the other scenarios I’ve found where some interesting male commentary occurs is on some of my blog posts. Now, don’t get me wrong a) most of the commentary I receive on my blogs is super supportive and is what gives me the impetuous to continue to write them and b) I acknowledge that by writing and (over)sharing the way I do I also invite engagement and discussion of the content I put out. Every now and again I get a comment that I don’t approve for public sharing and just leave in the archives as I’m not sure that they are part of the discussion I want to have.

When I posted earlier this year about being overwhelmed and shared some tips that have helped me to get through I received some comments from various male subscribers. These comments were very different from those of my female subscribers, who shared how grateful they were that we were talking about the fact that everyone has days when they struggle and that coping mechanisms are key. These comments all came from a place which I assume was kind and supportive, but ran along the lines of ‘if you feel overwhelmed maybe you should have spent the extra time working and clearing your emails rather than writing this blog’.

On the surface I kind of get it, but also a) it is my right to choose how I spend what free time I manage to have for myself, without commentary from others as long as I’m breaking no laws and hurting no one b) blog writing, for me, has become a method of processing my work load and stress levels and therefore suggesting I abandon it would be removing a key coping strategy I utilise c) the blog post was about sharing experiences and methods to move through feeling over whelmed, not a pity party post about how it sucks, therefore the suggestion that I focus my time on not supporting my community is against the ethos of what this blog is about and frankly kind of sucks and finally d) the assumption that I wouldn’t have considered doing less and not over stretching myself probably doesn’t give me very much credit in terms of self reflection or self awareness. So, I suppose my point is this, sometimes by stating the obvious and your opinion about it, it can come over as pretty patronising, as if it wouldn’t have occured to me and I haven’t done the thinking myself. That said, intent matters, and I don’t believe that these are often meant with any ill intent, so I leave them as unapproved and a source of future consideration and move on.

If you look for it, you will see it

Frankly, some of this is insidious, as I discussed in the intro, I only really started paying attention at the conference because there was such an extreme version of it that it drew my attention and I became deliberately aware of it. Sadly, when I posted about it on twitter the almost universal response was ‘only one’ to my retelling of the male commentator. It’s so universal as a stereotype that we laugh about it, but my thinking is also what can we do to challenge it or support others when we see it.

Summary.   

Role incredulity is a form of gender bias where women are mistakenly assumed to be in a support or stereotypically female role — an administrative assistant, nurse, wife, or girlfriend, for instance — rather than a leadership or stereotypically male role, such as CEO, professor, lawyer, doctor, or engineer. While this slight or mistake might seem innocuous, it can have real ramifications for women. Women must expend extra energy and time to assert and prove their role. Their words may lack the credibility and authority inherent in their position. And when women are not seen as a leader, they may be less likely to be hired into male-dominated roles or to be considered for promotions.

While the real issue of role incredulity is systemic, there are steps organizational leaders, workplace allies, and women themselves can take to prevent and correct it., including setting organizational norms, being an ally, owning your mistakes, and, if you’re a woman, proactively identifying your role.

https://hbr.org/2021/12/when-people-assume-youre-not-in-charge-because-youre-a-woman

I suspect there are few women amongst us who haven’t been asked to ‘sort the coffee’ despite being one of the most senior people in the room, or who haven’t had their bank card saying Dr handed back to their partner. These are little things, and I for one am completely OK with getting coffee, but not because I’m a woman, but because I think we should all take our turn and hierarchy shouldn’t remove us from that. I find it hard therefore to know when to draw the lines over such things, I’m a team player and want to do my part, but I also don’t want to sustain a stereotype that might negatively impact others. Honestly, even thinking about these things in the moment and having that constant dialogue with yourself can be pretty exhausting when it happens over years or decades.

Do these things actually matter?

Even though I feel that I own my place and have so much more strength than I did when I was younger, these comments, decisions, and moments still take up cognitive space. I may rebound more quickly but I still go through the ‘experience-self recrimination spiral-replay’ cycle in order to process it and decide where fault may lie with me or where the learning is.

“What we found was that women largely had negative outcomes as a result of being mansplained to, whereas it didn’t affect men as much,” said Briggs, whose research was published in the Journal of Business and Psychology. “They tended to register that their competence was being questioned more than men did, and to attribute this to a gender bias – so, maybe this person doesn’t think highly of me or doesn’t like me because of my gender.”

This feeling wasn’t shared by male volunteers who were given a condescending explanation by a woman. “Maybe they perceived it as ‘this person is being rude to me’, but they didn’t perceive it any differently if it came from a man or woman, and they didn’t attribute it to a gender bias,” Briggs said.

https://www.theguardian.com/science/2023/feb/03/let-me-mansplain-studies-reveal-negative-impacts-of-behaviour?CMP=Share_iOSApp_Other

It may be therefore that we have to acknowledge the role we play in how we receive the information and the fact that some of the behaviour we experience really does not have any ill intent. However, that also doesn’t mean that those undertaking such behaviours don’t equally have a responsibility to understand how their behaviour impacts others, and in some cases leads to the active detriment of the women who are the recipients. Especially if this behaviour is endemic in institutions/settings or originates from the same individual over protracted periods of time.

So, how do we handle it?

I’ve previously posted about how I learnt to own the place I found myself in with some tips on managing this as individuals. I do think that dealing with direct interactions rather than our own imposter syndrome needs a different set of skills, ones that may indeed help with how we see the world over all. It all starts with being conscious of ourselves in the moment, where do we sit, what do we say when we introduce ourselves, how do we respond in the moment and how do we let our view of ourselves drive these dialogues?

Below are some areas of thinking that have helped me and I hope might also help you in traversing the particular challenge.

Decide which truths to believe

I am often considered over emotional because I wear my heart and values on my sleeve. It’s a running joke within my team that I have absolutely no poker face, and the time to be concerned when in a room with me is when I stop being expressive, as it probably means I have become coldly annoyed.

For a long time, I thought that this was the biggest weakness. I had many a person (male and female) explain to me that I couldn’t be successful as I was and that to proceed I really needed to change and fit the stereotype of what a boss/consultant/professor should be. Well, frankly, screw that. Hiding who we are and pretending to be someone else should not be the only path to success. Being open and honest about my values and who I am is not a weakness. It requires integrity and fairly often bravery to function openly as who you are. We are supposed to be assertive but not too assertive, smart but modest about it, passionate but not emotional. I, for one, don’t want to play that game and, in many ways, just opted out and found ways around it. I strongly believe that we no longer need to play by the rules of those who came before us, let’s set our own rules, let’s choose our own truths and empower the future to be different and better for those who will follow on behind us. Choose your own path and let that be your truth.

Practice makes perfect

Now, I’m not sure I would be comfortable saying any of the below as they are written, I think I would be too scared of coming off as aggressive. For all you women out there who could and own being that assertive, I am not worthy. That said, I have used many of these responses, if not these exact words, in order to manage conversations.

The thing for me is you need to know what language you are comfortable with and practice it before you need it. In the moment I am often surprised and lose my mental footing, therefore if I haven’t practiced how to hold my ground and be assertive I lose it to hesitancy and upset. Practicing enables it to almost be a reflexive approach that you can draw on, so that you don’t have the cognitive additional load of making those nuanced word choices in the moment. So the sentences above may not fit you, but find ones that do and try them on for size well before you need them.

One of the things that also helps me is wearing a different head space when I go into rooms where this is likely to be an issue. ‘Dream’ would never hold up in these spaces, and when I leave them, she often crumbles in the replaying of the moment. Professor Cloutman-Green, however, is much more able to hold her own. It’s almost like my science shield enables me to suffer less from impact in the moment and so allows me to maintain or re-establish myself in that moment much more readily. This is different from not being my authentic self in a space, I am still me, but it gives me the emotional distance to process things later rather than being overwhelmed in the moment.

Self-awareness is key

Ever walk into a room, and there’s a single chair left and you offer it to everyone else who comes in after you? I do this all the time. It’s just polite, right? Absolutely. However, if you are in a room that internalises hierarchy and everyone sitting is a Consultant like you and everyone else standing is more junior, by undertaking this action you are unconsciously giving away your seniority in the room. You are signally you’re difference to your other consultant colleagues. Being aware of your surroundings and what cues you are sending out is important.

Ever sat listening whilst a colleague towered above you? The person who deliberately chooses to lean against your door frame whilst you sit in order to explain X or Y to you. Dominance positioning is a thing, we are primates after all. If we have small and closed body language it says a lot more than our verbal responses in the conversation. Sometimes, when you find yourself in a mansplaining situation the mere act of repositioning yourself can impact the conversation. Stand up, gesticulate using wide body language when speaking. It may be that this merely changes the way you receive the exact same dialogue, but sometimes that is half of the battle. If it also supports you in using some of your practiced dialogue, all the better!

How do we help others?

When sat in the conference room mentioned at the start of this article, I had so much rage at the way these young scientists were being treated. My PhD student who saw and understood my response asked ‘are you going to say something?’. I responded ‘no, these girls are going to handle it’, and they did. They did so perfectly. I think one of my biggest pieces of learning over recent years is not to run in like an amazon warrior to save people, as this can in actual fact be diminishing and takes away their opportunity to act. My response now is to be there as a back up if they signal they need help and to offer support and reinforcement with ‘you were amazing in how you handled that’ afterwards to let them know how successful they were from an independent observer view. By rushing into save we can be as bad as the mansplainer as it indicates we don’t have faith in their ability to handle the moment. That said, if I’d had an official role, such as Chair, I feel it would have been my responsibility to stop the situation from happening in the first place. My take home is this, how you respond has to depend on your role and the situation.

I still love the females from the Obama administration who used their voices to amplify those of other women in the room. Not all actions need to be direct or confrontational, sometimes just being there to repeat the voices of others is enough. I wish that I had been able to breath through my rage and find an amazing follow up question to allow that panel to shine even more in that moment, but I didn’t and that’s my learning. That moment wasn’t about me, it was about them and next time I will have practiced how I can then act to amplify them better in the moment, rather than worry so much about the mansplainer in the room and giving him my energy. Every day I learn a little more.

Right, I’m off to the growlery until I find myself in a better mood. See you on the other side.

All opinions in this blog are my own

Learning to Take Your Place: The path to owning the space you find yourself in

I remember my first attendance at the CSO Healthcare Science awards incredibly clearly. It was probably around 2015, and I had been nominated for the Rising Star award (I didn’t win, the amazing Lisa Ayres rightfully rocked it). It was my first dinner event, and I didn’t really know anyone. Everyone was in their finest evening wear, they’d all done their make up, they all knew each other. I remember sitting there on my own and feeling how much I just didn’t fit into this world. When the Lead Healthcare Scientist award was given out (we didn’t even have one at that point) I remember the banter on stage about where the winner had brought their dress from. I wouldn’t even know where my dress was from, at best M and S, not something that would be discussion worthy for over 100 people. I was so aware on that night that this was a world where I didn’t fit in, or have the tools to navigate.

Despite being Girlymicro, I’m not actually particularly good at the getting dressed up thing. I’m not one of those girls who has ‘wardrobe choices’ and saints help me if I have to paint my nails. It’s just outside of my wheel house. I’ve also posted before about how bad I am at networking and how I’ve had to develop coping strategies to be able to feel comfortable in rooms at conferences. I have friends and colleagues who are naturally gifted in this regard, but I am not one of them. I am not ashamed of who I am, or where I come from, I’m a proud brummy girl who has worked hard, but that doesn’t change the fact that in 2015 I stared at out at a room full of people from my profession, supposedly from my world, and just felt as other as it was possible to be.

Roll on eight years, and through some twist of fate I don’t think I will ever truly understand, I find myself standing outside of Westminster Abbey, waiting to go in to witness the Coronation of King Charles III. I have gone through a lot of emotions in the journey to this spot, but when standing here I didn’t feel like the girl who didn’t fit in. I arrived through those doors comfortable in my own skin, proud to be representing my profession and not scared to represent all that I am in the process. So how did I get from there to here? How I did I change and grow to feel like I could (most days) own the space I find myself in?

Honour the reason you’re here

The first thing for me was the realisation of how many people, woman in particular, have fought and sacrificed so that I could have the opportunity to even feel like an imposter in a space. I’ve posted about my mum and her journey to support science before, but there are so many woman who have faced so many challenges just so I would have the opportunity, or the door opened. Over time I’ve realised how important it is to seize those opportunities in order to honour those that came before. To move the dialogue on and to ensure that I leave things more open and equal requires me to do my bit, to make my sacrifices for those who will come after, to go through that open door and wedge it open so that others can follow behind and then take even bigger strides than I will. The cost of my feeling uncomfortable and experiencing self doubt is nothing compared to what those who went before experienced. If I think of myself as part of a wider picture, of just another brick on the yellow brick road, then it becomes less about me and more about the journey, and what I do to support others. That doesn’t require me to know anything about hats, false lashes or designers, that only requires me to be passionate about why I’m doing what I am doing. Suddenly everything else feels slightly less intimidating, after all, I know my why.

Be decisive: decide who you want to be in that space

So, you are not like everyone else, congratulations! I think that may just be a very good thing. When you enter a new world, a new network, a new experience, you have an opportunity to be deliberate in deciding who you want to be. You aren’t carrying the baggage of being know as ‘the new girl’ even though you’ve been there 20 years now. You aren’t that girl who spilled adenovirus tissue culture. You are shiny and new. You therefore have the opportunity to tell your tale, to share your why and really focus on the impact you want to have. Most of the time you have been invited into that space, so try to reflect on why that is and what you want to achieve. If, like me, you want to move the dialogue forward than it is OK not to be like the other people in the room, you have probably been invited into that space for just that reason. Don’t lose sight of who you are because of the newness, see it as opportunity to be the essence of what you want to bring into that space. If you can focus on why you have chosen to be there, rather than being overwhelmed by the choices of others, then I find it very grounding. For me, that reason can be anything from, I came to have 1 conversations with X that I couldn’t have other wise, to I came because I want to raise awareness of Y. Sometimes, for me, that can just be me actively introducing myself as a Healthcare Scientist and opening the door for people to ask me what one of those is, so I can discuss how awesome this work force are.

Acknowledge your fears

One of the things that has helped me most is to not just ignore my fears and pretend they don’t exist, but to spend time in reflecting on why they exist and what triggers lead to them overwhelm me. For me, it’s often about letting people down, or standing out in the wrong way – thus diluting my message and meaning I lose my voice. For the Coronation, because I knew not feeling like I was fitting in appearance wise would be a trigger for me and therefore not achieving the representation I wanted to achieve, I took steps before I went. I researched what to wear, I learnt to understand the dress code. This meant on the day I didn’t worry about that part at all, I could just focus on representing IPC and the Healthcare Scientist profession, this isn’t hard, because I have the best job in the world and love my profession. Suddenly I’m freed up to focus on joy and not fear. In 2015, I hadn’t done this work and it’s not something that happened over night. I had to take the time to learn more about me so I could then manage my responses. The work is worth it though. Obviously, this doesn’t always mean you won’t be taken from left field, but most of the time if you’ve put in the work you can free yourself up to be present and enjoy the moment.

Understand that the world is not you centric

The other things is, and I don’t want to ruin anyone’s egos here, you’re just not that important. The BBC did not care what I was wearing at the Coronation, in 2015 I was probably hardly noticed at that event, let alone anyone bothering to think enough about me to judge my outfit or elevator pitch. Frankly, we are mostly just not that important to other people. Therefore a lot of the fears we have about being judged are really not that relevant, we’re just not that seen. Also, even if the worst happens, and you spill that red wine all over the carpet at the House of Commons drinks reception (yep, I did that) the likelihood is that no one will remember. In my case the only person who remembers is Professor Mark Fielder, mostly because I almost spilled it on him too, and we just laugh about it now. I have been to some truly awful conference presentations, but I remember the topics, I don’t remember the speaker. Even if the worst happens, when you get over the mortification, you will be the one that remembers it, it is unlikely that anyone else will. So be braver, the worst is probably not that bad, spend less time worrying over it and embrace the good that could happen instead.

Have the bravery to keep being you

Finally, and this may be because I’m just growing old disreputably, but be brave enough to be you. You find yourself in this moment, and no matter the reason you arrived at it you are the master of your own destiny. Be brave enough to bring all of you into that moment and be who you want to be. It’s not always easy in the moment but I promise you, you will regret the moments when you wuss out and toe the party line or try to be someone else so much more then any moment when you were truly yourself, no matter what the reception. For me, I guess its always about having honesty with myself, and building relationships with others based on the trust that I will be seen. Relationships and moments built without that honest and courageous authenticity will never be really real, you’ll always question them and yourself within them. By being who you are then, good or bad, what you create with others is the truth and has real meaning. I feel it is only by being bravely who we are that we can have the impact that we want for our lives and for changing the world for those who will come after. So lets raise a glass, to being authentically and completely us, and celebrate all that we are, both the good and the work in progress!

All opinions in this blog are my own

An Unexpected Invitation: Representing the Healthcare Science & IPC workforce at the Coronation of King Charles III

Please note, this is a rather self indulgent post written to help me remember in future years what was a truly spectacular day and set of events.  Please forgive me and feel free to skip.

Let me start off by saying what an incredibly normal person I am.  I have a job I am passionate about, friends and family I love, but apart from quite how fortunate I count myself to be, I am incredibly normal.  I don’t have ‘connections’, I didn’t go to private school, and neither I nor my family are part of any clubs or other exclusive societies.  So imagine my outright shock when in March this email dropped into my inbox on a Friday afternoon:

This is a joke………right?

On the 31st January 2020, I was fortunate to be awarded the British Empire Medal for services to healthcare and I wrote a little about how I didn’t believe it in a blog post.  That was a fascinating process in itself, especially as I couldn’t tell anyone. When this email dropped into my inbox however, frankly it felt like someone was playing a bit of a joke.  I opened and returned the form, almost on auto pilot because it felt like the kind of thing you should do, but as soon as I hit send I phoned my mum and Mr Girlymicro and had a bit of a breakdown after I calmly got the words out.  Just saying the words ‘I think I’ve just been invited to the Coronation’ put me into a complete spin.  You see, I’m the girl that snuggles down with a cup of tea and Agatha Christie when I manage to get time off, or to be completely honest, some truly awful reality TV (hated by my husband 🙂 like Love is Blind.  I am not the girl that gets invited to fancy dinners or big events, let alone something to be seen on the international stage.  Writing the Girlymicro blog is often the most down time I get on a weekend.  So after sending my reply I sat back and just assumed that they would at some point realise their mistake and life would carry on.

Costume drama

As time went on and more emails went back and forth it gradually hit me that I may, in actual fact, need to attend the Coronation.  I went through a period of properly freaking out about how I wouldn’t fit in, and how I’d have nothing sensible to say, my family pointed out it was too late for that, I’d accepted the invitation.  I was locked in.

Then I proceeded to have, what a dear friend, referred to as a ‘Costume Drama’. Now, I get up in the morning and dress in the clothes in front of me.  I am guaranteed to have covered myself in food/tea/detritus within an hour of dressing.  I don’t wear makeup, and when I do I am lucky to not poke my own eye out with my eye liner.  As the reality dawned on me, it also occured to me that I was going to need to have something to wear.  Bear in mind that when I went to the Garden Party at Buckingham Palace I had a tail spin because I had never brought a hat and I just didn’t know what to expect. It took me 6 months to find something to wear and I had a little less than 6 weeks to get this sorted.  This also felt like a complete level above what I had needed to achieve for afternoon tea.

I have previously posted about how I feel about clothing expectations.  In this case, I began to increasingly feel like clothing would have a role as armour, as a way to step into a space where you felt like you needed to put your best foot forward.  I needed to find something to wear that would help me feel like I deserved to be there and could occupy the space I had been given.  At the same time, I wanted to balance the costume with who I am, I wanted to feel both like I belonged and still feel like me.  So, being a scientist, I hit research mode and pulled together as many sources as I could to find the ‘uniform’ that was likely to be worn at such an event, and then to find ways to modify it so I could ‘fit in’ and still be me.  I know some of you will be reading this and feel disappointed that I was not prepared to stand out. To make a statement.  Sometimes, I feel that the freedom to make a statement comes from a position of privilege.  Not always, sometimes it’s merely bravery and not worrying about the consequences.  In this case, I didn’t feel I wanted to make a statement, I don’t feel like I come from a place where I have enough privilege to go against the tide. You may think it shows a lack of bravery, but the last thing I wanted was to stick out in anything but a ‘that’s a nice dress’ way.  I was nervous enough, and a lot of those nerves stemmed from knowing that I was representing not just myself but all of you, my family, my profession, and my friends.  What I wanted most was to make everyone proud, and so standing out needed to be done in the best possible way by rocking a look that acknowledged the event and still felt like me.

Feeling the weight of representation

You see, as time went on, I became more and more aware that the invitation I’d received wasn’t really about me, it was about us.  I didn’t get a BEM for my work in isolation, it was for the work we had done as a community, I was just lucky enough to be the one who got a medal pinned to her chest.  As the event drew nearer, I was so aware that I was representing both Healthcare Scientists and Infection Prevention and Control on an enormous stage.  I am so proud to be part of both of those groups.  I am prouder than I can state about my profession, a profession that is so often hidden and doesn’t get mentioned at the big events.  I knew that the one thing I would be able to do on the day was talk about it and shine a spot light, if even just to a few people, on the amazing work my colleagues do and the sacrifices that they all made during the pandemic.  I was aware that even though it was my name on the invite, in point of fact, in many ways, it wasn’t about me at all.  I needed to use this unique opportunity to shine that spotlight on the people who deserve to be seen.

Coming, ready or not

Knowing it wasn’t really about me didn’t stop me from feeling nervous, however. I often get in my own head about big moments or events, especially things like this that feel too big and outside of the normal, for someone as normal as me.  At times like this, I like to remember a quote of one of my favourite TV series:

“Bottom line is even if you see ’em coming, you’re not ready for the big moments. No one asks for their life to change, not really. But it does. So what, are we helpless? Puppets? No. The big moments are gonna come, can’t help that. It’s what you do afterwards that counts. That’s when you find out who you are. You’ll see what I mean.”

Whistler – Angel Season One

My family, friends and colleagues did a great job of helping me get out of my own way.  I really struggled at first with people asking me why I’d been invited.  I didn’t know, I didn’t have an answer, but with the help of those around me I practiced an answer I could use on the day, ‘I got invited because of the great work that IPC and Healthcare Scientists did during the pandemic, coming together to really make a difference for children and young people, in terms of not only testing but also in keeping them safe in healthcare.  I’m representing a great group of people who all go above and beyond every day, and I’m really honoured to be invited.’ I was as prepared as I was going to be.

A fairy tale day

So, the day arrived.  I continued to be nervous, but I had all the lists and instructions to make me feel prepared.  In the end, everyone I have to say was simply wonderful.  I had been prepared for the formality, but I don’t think I had been prepared for the nice bits, the bits where we laughed and the bits where the event was in some ways just like every other event, just bigger and shinier, and with some of my hero’s present.

The day started at 5:15 am.  I knew that there wouldn’t be many bathroom opportunities and so I could only have one (yes, that’s right, one!) cup of tea.  Because I also knew that doing my hair and make up would stress me out and I wanted to enjoy the day, and because London has people who will do this for a very reasonable price at 6am, a wonderful lady arrived to make me feel pretty.  I was made up, hat on and in a taxi by 7:45.  All the time, with the news running in the background saying people were arriving and making me feel like I was already late.

I had that strange anxiety, like getting to an airport, where you just want to get through security and take your seat.  I have to say that from the minute I showed my invite and started walking from Victoria Gardens down towards the Abbey, everyone was just so lovely and the nerves started to fade.  Security was easy, and the atmosphere just felt really special.  I felt like I do when running a half marathon, when everyone on the side of the road cheers you on, with less running and more hat.  This part was made even nicer by running into another IPC legend Clare Johnstone as I was nearing the Abbey.  This was great because not only did I have someone to experience it with, but we could also take a photo of each other to record the occasion. 

Clare and I weren’t sitting in the same area, so I made my way to find my seat, just behind the North Quire.  I was in some way saddened to realise that I wouldn’t have a good view of the procession, although to be honest, I’d not been expecting one.  What I hadn’t expected was that everyone from Rishi Sunak to Ant and Dec would have to walk right by me both before and during the ceremony, as the Quire was mostly blocked with performers.  This meant I got to do some grade A up close people watching in the 2 hours plus you had to be seated prior to the arrival of King Charles III, including Lionel Richie being a complete gentleman as he went by, asking how I was doing and saying he like my dress.  The other thing that was interesting to note was that everyone had to scrum for seats.  Now, as a pleb I’d expected this to be the case for me, but no, it was also the case for those much more famous than I.  Those entering through the West Door had reserved seats, but everyone else was very much equitable in terms of finding your own within the section you had been allocated to.  I found this somewhat pleasing.

We all knew the toilets were going to be locked down at 10am, and having been sitting since 8am it seemed sensible to try to get a visit out of the way as there would be no further opportunity until after 13:30.  I state this here because, although the event was spectacular, the fact that toilets are always an issue somewhat amused me.  There were 3 female toilets for the entire of the Abbey, for everyone from Hollywood celebrity to little old me, it made no difference.  My colleagues have often heard me swear I will never use a portaloo, as I hate them from an IPC perspective.  The available toilets were a step up, but they were still just temporary toilets.  Of the 3 cubicles available, 1 did not have a working lock on the door, and 1 was blocked, only leaving 1 toilet in reality for everyone to use.  Also, the cubicles were small.  Normally, this would be less of an issue, but as I’m not someone who has often tried to negotiate such things with a rather large hat, it was challenging.  Toilets are an issue, even if you are a King.

When the ceremony started I was fortunate enough to have found a seat next door to the seating reserved for the Heralds.  This was very cool as I got to see them process, but also got to sit and get an up close view of all their regalia and to see a lot more of their roles.  The advantage to being off to one side and therefore not quite on camera was that although the event was still very formal, I got to enjoy some informal moments that made us all laugh.  Some parts of the order of service did not quite go as planned, such as the Prince and Princess of Wales entering iut of order. Because we were in quite close quarters together there was a real sense of comradery, which I hadn’t expected, as we all got up at incorrect points or couldn’t work out when to sit down when things were not quite as stated.

There was also some slight drama, when during the first hymn, the older lady next to me tried to drink some water, choked and then vomited water all down her, me and quite a chunk of the floor.  Trying to silently signal and collect tissues, check she was OK and clean her up was significantly easier given where we were seated, but again our whole section silently pulled together to try and help.  This is the disadvantage of telling people that bathroom access is limited, as over 5 hours is a long time for some people to not feel like they can drink.

There was never really a dull moment during the service, and it felt like the congregation were constantly involved in small ways during the service.  The moment when the enormity really struck me however, of where I was and what was happening, was during the singing of the national anthem, it made me choke up a little, it just felt truly historic, it really felt like I was living through a never to be repeated moment, and I felt so lucky to be there to witness it.

And then it was over, and yet somehow the time after the Coronation itself felt like the nicest bit.  You could almost feel the collective sigh of relief, and the atmosphere suddenly became much more informal, with people taking selfies with each other, talking and introducing themselves and mingling much more freely.  At this point I could really talk to people about the amazing work my colleagues do and what an honour it was to be there.  It also meant I could get a couple of pics of the Abbey in a way you weren’t permitted before the ceremony.

Then, as I was leaving the Abbey something happened that really made my day.  I got to leave the Abbey and walk with Dame Judy Dench and Sir Kenneth Branagh.  I mean, I didn’t have the courage to say anything, especially as they were just talking to each other in a really normal way, but I got to wander down the road with 2 complete legends, and then say hi to Stephen Fry.  The only way I could have been  more excited was if I’d gotten to meet Michelle Obama, but it appears she didn’t get an invite.

It was a truly magical day that exceeded all my expectations, I got to talk to people about the work we do, I got to feel part of history, and I got to visit a world, however briefly, which I never believed would welcome someone like me, and yet it did with open arms.  I felt like I was welcome, I felt like I was seen and unexpectedly I felt like I deserved to be there.

My 7 seconds of fame on the BBC, plus the legend that is Dame Judy Dench again!!

Carrying your family with you

My friends and family mean so much to me, and they properly stepped up to the occasion, from sending gin minis for after the service that I could use to celebrate, to sending me pieces of jewellery that I could wear on the day and therefore carry them with me to help me deal with the nerves, and to help me feel like I belonged.  They helped me move from feeling worried about the need to represent people and a profession who mean so much to me, to feeling the joy of doing the same.  They helped me stay in the moment and understand that rather than fearing letting people down, I should celebrate making them feel seen.

Seeing their excitement, feeling their support for me stepping onto this enormous stage and celebrating me embracing all of who I am and where I’ve come from made all the difference, and no amount of drizzle could dampen the day.

I was collected by my husband Jon after the ceremony, and not only did he bring me an umbrella, but he also brought me comfortable shoes to switch into. I’ve rarely loved him more. Sharing the build-up and the day with people I love, as well as seeing the responses on social media, really did make it a day I will never forget. Thank you for sharing it with me.

All opinions in this blog are my own

Learning to Live in the Grey: Moving back to a risk assessment based approach for IPC

This is the post I was supposed to get out last week but didn’t quite make it as my mind latched onto dealing with what was directly in front of me, rather than being in a more conceptual space. That said, after having just run a course, where the main theme was supporting participants to be able to use frameworks to make risk assessments, it still feels like an important conversation to have. Now, these are just my observations and thoughts. They are not meant to be criticisms of any person or indeed the system itself. I hope it will just continue the conversation about what serves us and our patients best, and we all know there is not a one size fits all approach.

Pre-pandemic it felt, to me, that there were guidelines frameworks out there, particularly linked to things like Carbapenemase Producing Enterobacteriales (CPE’s), but in the main part Infection Prevention and Control (IPC) teams used a lot of personal judgement and experience to determine routes to management, with input from Health Protection Units as needed. The pandemic led to a big switch, where a command and control approach was undertaken. This made complete sense, as resources were restricted and shared across the system. Therefore, frameworks supported us all practising in similar ways and with expectation setting. They also supported large scale evidence collection to improve interventions. We were also in a scenario where some of the diversity of what we were dealing with was removed, in terms of IPC, the focus was mainly on one key organism. Now we are moving back into ‘business as usual’ both in terms of patient flow, and in terms of organisms, that one size fits all approach feels like it may do us a disservice, as the challenges are now so much more diverse. We therefore need to think about how me move back to a much more risk based approach, where instead of having a single organism focus, we also take the setting and the patient into consideration.

Risk assessment and risk based decision making

Those of you who have read some of my other blogs, about the fact that I genuinely believe that IPC is 90% risk assessment will not be surprised that I believe that we need to empower people to undertake these risk assessments better. For 3 years we have given everyone very specific instructions for their actions on every part of the pathway, when to test, what test to use, what PPE to wear, all possible because we were focussed on one thing, much like the standard risk matrix below: risk = SARS CoV2, and all risk mitigations are rated against this in a 2:2 matrix.

We are moving back to a world where, instead of using a matrix where everything is measured for it’s efficacy against against a single pathogen, we need to consider multiple pathogens, their characteristics, and how these play out differently in different patient populations and in different settings. Therefore a standard risk matrix approach does not serve the outcome of increased patient safety we all want to achieve.

Sadly, it also gets even more complicated. We have been living in a healthcare system for the last 3 years where everything, action wise, felt like it was determined by testing and test results. That means that we have been functioning using a test based action algorithm for a very long time. Now, I’m a scientist, and therefore love a good diagnostic test. However, in healthcare there are so many things that can impact on test outcomes: timing of the sample, factors such as antibiotics, quality of the sample, test requesting accuracy, specimen type etc etc etc. We are not just optimising all of our testing pathways for improved sensitivity in relation to a single organism, we are trying to use the best choice we can in order to maximise information output for a wide range, there will therefore be things that bias the accuracy of those results. So we are back in a healthcare world where we need to stop being so focussed on the test and the test result, and start seeing the patient in front of us again, irrespective of what the negative test may say. We need to move back from a test based approach to a symptom based approach. If my patient has respiratory symptoms, they should be in droplet/airborne precautions, irrespective of what the test results say. If my patient has diarrhoea, then we need to put them in contact precautions irrespective of a negative gastro panel, unless you have clinically evaluated other reasons for the symptoms. This clinical evaluation step is key, and you can’t put all of the information linked to that in a flowchart, therefore we need to switch from command and control responses, to supporting the experts at the bedside to use their clinical knowledge to evaluate patients, and support them in better risk based decision making to support IPC. We have to acknowledge that the assessment process is complex, but also feel that we have supported staff enough to be able to make those complex judgements.

Acknowledging the uncertainty in the system

The problem with a risk assessment based strategy, managed primarily at the bed side, is two fold. Firstly, you have to be prepared to support with the education to enable it to succeed and to know when to escalate and question. This can be time consuming and it is a task that needs to be continuously supported, as staff, patient mix and environments change. Secondly, we have to have honest conversations with staff to help them to understand and become more comfortable with some of the principles of uncertainty. This is because algorithm based approaches often offer, sometimes unreal, certainty. If I do A and then B in compliance with a flow chart everything will be alright. By increasing complexity in decision making, you also introduce uncertainty, and that needs to be acknowledge and addressed as part of our approaches. Otherwise staff will never feel empowered to take the steps required.

Types of uncertainty

The first thing to say, is that not all uncertainty is the same, and therefore you need to approach different types using different tools. Epistemic uncertainty, is the one in healthcare we can probably do the most about. It’s the kind of uncertainty which we can, sometimes, address by asking better questions. Questions like, I notice you seem to be using a lot of tissues, do you have have a cold or feel like you have a bad chest? Questions like, have you been in contact with anyone who has had an infection or been unwell recently? Or have you been travelling a lot recently? If we can support our staff to feel more confident in collecting the information they need, and then knowing what to do with it, they will feel more confident in making decisions without escalating all of those decisions up to someone else for sign off.

Other forms of uncertainty, such as aleatoric uncertainty are harder to address. This isn’t uncertainty that you can address by gaining more or better information, it’s the kind of random chance events that you have to manage by becoming more comfortable with the fact that healthcare is multifactorial, and you may never be 100% about any action or solution. An example I always use in my head for this is a 4 bedded bay where someone has just vomited due to norovirus. We know on the balance of evidence all 3 other patients are likely to acquire norovirus, as it will stay in the air for ~2 hours and up to a million copies of the virus will circulate prior to deposition. What we don’t know is, did 1 of those 3 patients have norovirus last month after a wedding, and therefore currently has sufficient immunity against the circulating strain? Is 1 of the others one of the small number of people who have receptor variance which means they are less likely to acquire infection? You can’t get that information by looking at them, you are unlikely to be able to get that information by testing or asking questions. Therefore you have to manage the uncertainty and deal with the decision making you can undertake, with the information available to you. That decision making also becomes much more complex when consensus making is difficult, and so supporting staff to know how and when to escalate when this occurs is really important.

So how do we deal with uncertainty better?

For me, the first step is to acknowledge that it is there, rather than trying to persuade ourselves that bedside risk assessment is a) easy and b) doesn’t come with any discomfort for the staff we are asking to undertake it. It takes time and space to be able to this well, both for the required educational component and for the staff to be able to have the cognitive space to ask and process the questions, as well as undertake any follow up. It also takes us to really recognise that we are a single team working across that healthcare pathway, this isn’t about IPC putting their responsibilities onto someone else, it’s about improving patient outcomes by having the people evaluating patients as close as possible to the ones making informed decision about those patients. It does not stop the requirement for complex decision making to be escalated or remove the need to be able to ask for support. It also requires feedback and monitoring so that staff do not feel like they are being left alone to carry a risk or fearing consequences for inappropriate decision making. It is about empowerment in patient care, not resource saving.

I personally believe that we need to move away from central dictates for IPC decision making, patients are unique, and combining that with different environments and organisms means that numerous factors need to be taken into consideration if we are to provide the best possible care. That cannot be done well centrally, where we never see the patient and are not aware of the minute by minute changes in their wellbeing. Supporting those at the bedside to make better decisions and empowering them to be the people who respond to those changes is key to moving away from the single organism focus of the pandemic. IPC teams are key, they should be the ones educating, empowering and being the escalation points, but there are simply not enough of them to have one at every bedside and so we need to look at spreading the knowledge and IPC love!

All opinions in this blog are my own

Guest Blog by Lilian Chiwera: Surgical site infection prevention day initiatives – making change now to help tomorrow

I wanted to quickly write and introduce you to the passionate and energetic Lilian Chiwera. Lilian is leading on a new project that aims to raise awareness of and better embed surgical site surveillance in healthcare. Her enthusiasm is infectious and she has swept many of us up in her wake, so grab a cup of tea and read why this piece of work is so important and why we should all want to step up and see how we could get involved.

Lilian Chiwera is a independent Surgical Site Infection (SSI) surveillance & prevention expert with experience setting up and coordinating a very successful SSI surveillance service at Guys & St Thomas’ NHS Foundation Trust (GSTT) from 2009 – 2022. Currently working in Digital Transformation, Lilian is exploring how best infection prevention and SSI prevention can be aligned with current digital transformation agendas. Blogs via: https://www.lilycompassion.com/

“I think I can officially declare that I’m now married to surgical site infection (SSI) prevention! There is no day or hour which passes by when I don’t think about what we can do to prevent avoidable SSIs and promote patient safety in our organisations. Yes, my passion for this important patient safety initiative is overflowing. I am honoured and humbled to have so many people supporting our latest push for SSI Prevention Day (SSIPD) initiatives.”

I must thank Elaine for asking me to write this blog. I have always looked up to Elaine, she is fun, very knowledgeable and always inspiring us through her fabulous blogs. When Elaine asked me to write this blog, I thought… where do I even begin. Elaine coached me on how to write blogs and I have never looked back. Check my previous blogs here and a fabulous selfie I took at the 2022 Infection Prevention Society Conference in Bournemouth, UK.

Given the number of people now supporting these initiatives I thought it was prudent for me to open this up to our SSI Prevention Day Group. I was not disappointed! Everyone came all signed up to do everything possible to support our call to action. It was no surprise therefore when Karen Ousey was so quick out of the blocks to write the piece below, thank you Karen!

Why surgical site prevention?

“Surgical site infections (SSIs) are among the most common and costly health care-associated infections, leading to adverse patient outcomes and death. The continued global discussions identifying the importance of reducing and preventing anti-microbial resistance and embedding antimicrobial stewardship strategies into practice highlights the significance of raising awareness for prevention of SSI for clinical staff and patients alike. Despite there being published SSI guidelines, there is still a lot of work needed to ensure improved compliance with implementation of evidence-based SSI prevention measures. Recently there have been some awareness campaigns that are attempting to raise awareness of wound infection. These include the International Stop Wound Infection Day (ISWID) held virtually on the 3rd Thursday of October annually which embraces Europe, Oceania and the Americas. The campaign features a range of free to access resources relevant to different countries and short videos from global wound care key opinion leaders and recordings demonstrating skills such as taking a wound swab. This campaign led by the International Wound Infection Institute states: Wound infection is a significant problem in both acute surgical wounds, leading SSIs, and non-healing, chronic wounds. Antimicrobial resistance is also a growing public health challenge worldwide which was identified as one of the top 10 threats to global health by the World Health Organisation in 2019. The ISWID campaign has been running for 2 years (2021 and 2022) and has seen lots of interactions from clinical staff across the world through social media posts and people being able to download free resources relating to prevention of wound infection.” Karen Ousey

It’s clear from Karen’s piece above that there is already lots of work going on around tackling wound infections. My desire has always been to ensure that we promote this important patient safety initiative together! In other words, an annual SSIPD can only be effective if all key stakeholders are involved and actively participate. Key stakeholders include all healthcare professionals and consumers of healthcare – covering a broad spectrum of specialisms i.e., Infection Prevention and Control (IPC) and SSI Surveillance and Prevention (SSISP) societies and collaboratives as well as patient safety advocates, journalists, musicians, quality improvement, human factors experts, psychologists, and many others. I therefore hope to see more stakeholders, in addition to those already signed up (see figure 1) collaborating with us on this important patient safety initiative.

Figure 1: Confirmed and proposed supporters

So, what are we really proposing?

Raise the profile of SSIs via:

  1. An annual SSI Prevention Day (SSIPD)/week
  2. Annual regulatory style SSIP inspection tool that will allow us to monitor surgical safety practices throughout the year via our dedicated SSI champions. These SSI champions will disseminate key findings/learning from inspections and action plans for the following year during the annual SSI Prevention SSIPD
  3. An SSI champion model that will give us an opportunity to standardise existing SSI surveillance and prevention processes in the UK and all countries around the globe through our dedicated local hospital, regional, country, and continent SSI champions.
  4. Proposed SSI champions will span a variety of healthcare professionals and consumers of healthcare. Our ambition is to embrace arts (journalism, music, etc.), science, other IPC branches, human factors experts, implementation science specialists, psychologists, Patient and Public Involvement (PPI) groups and many others to help us raise the profile of this important patient safety initiative.

Figure 2: proposed SSIP champion model and areas of initial focus

Proposed benefits include but are not limited to the following:

  1. provision of SSI/infection prevention expertise from ward to board by compassionate local champions, experienced SSI prevention champions, patient safety and infection prevention and control experts.
  2. Opportunity for collaboration and learning from each other.
  3. Opportunity for Chief Nursing Officers (CNO) and Chief Medical officers (CMO), Politicians and Journalists to champion an important patient safety initiative in the UK and globally.

From humble beginnings

What started as just another tweet in April 2022 has turned out to be perhaps one of the best SSIP campaign I have ever coordinated on social media (SoMe). By October 2022 I was presenting our SSI prevention day initiatives proposals at the largest Infection Prevention conference in the UK. Interestingly, the main reason I submitted an IPS conference abstract was because I just could not imagine myself missing seeing my friend Lisa Butcher being inaugurated as new IPS President. Therefore, I ended up taking the opportunity (aka killing two birds with one stone as some say!) to share our SSIPD aspirations with many conference attendees. Our IPS poster which was produced with input from many of our SSIPD group members was very well received. I left the conference believing that this campaign could become as popular or even surpass successes of the WHO annual Hand Hygiene campaign. Check out the timeline of activities via our Twitter handle here and hashtag #SSIPreventionDay.

Engaging our senior leadership

I presented our proposals to the Head of IPC at NHS England, after being given the go ahead by the Chief Nursing Officer. Engaging senior healthcare leaders and politicians is a critical component of our proposals. This draws from my experiences at Guy’s & St Thomas’ NHS Foundation Trust where with Dame Eileen Sills support, we established a very successful SSI surveillance and prevention service.

Proposed next steps

We held our first ever virtual brainstorm meeting which was kindly chaired by the wonderful, very experienced Infection Prevention Champion and Clinical Director at Gama Healthcare, Karen Wares on the 4th of January 2023. Everyone came ready to brainstorm! Check some of our highlights via our Twitter handle here. We’re planning our next meeting in February 2023, where we hope to consolidate and firm the future direction of our work. We now have a WhatsApp group where we’re ‘bouncing ideas off each other’, have a Facebook and LinkedIn page which you can join and be part of our exciting patient safety initiatives.

Conclusion

We’re proposing a novel patient safety initiative which we hope will bring enormous surgical patient benefits.  We believe our proposed SSIPD initiatives are feasible, given the level of traction gained over a short period. Thank you to our supporters and advocates who got us to where we’re today… buzzing with excitement! They call me the SSI Queen and I think I have lived up to my title on this occasion, with amazing support of course.

Surgical Site Infection Prevention Day Initiatives Group at the Inaugural Meeting on the 4th January 2023

Join us

Get involved by interacting on our Twitter, Facebook and LinkedIn pages

All opinion in this blog are my own

It’s Not All Bad in the World of Infection Prevention and Control: The most wonderful time of the year is approaching!

NB this article was originally written for the Association of Clinical Biochemistry and Laboratory Medicine and published December 2021

There’s no getting around the fact that it’s been a tough couple of years in the world of Microbiology, Virology and Infection Prevention and Control (IPC), but at this time of year its worth reviewing the bits of our jobs that are to be honest pretty awesome.  The bits that energise rather than drain us and remind us of why we love our work. 

Before I go any further, I should probably make a confession and declare that I am a bit of Christmas fanatic.  I’m the person who goes to Christmas shops when on holiday in June and thinks that as soon as November hits Christmas films and music are go!  So it’s probably of no surprise that my favourite IPC event occurs in December as part of the build up to Christmas.  Hopefully, you will also appreciate how great it is even if you don’t love Christmas as much as I do. 

I work in a paediatric hospital and every year the patients are lucky enough to be visited by not only Santa, but also his reindeer.  What does this have to do with IPC I hear you ask?  Well any animals brought onto site need to have an IPC risk assessment as they can be linked to zoonotic transmission of infection and thus pose a risk to patients.  My colleagues’ favourite time of the year is when she gets to do this for the rabbits and ducklings at Easter, but for me the reindeer assessment is very much my favourite.

Reindeer can be a source of ticks, which can harbour organisms that lead to Lyme disease and other tick borne infections, as well as being a source of more exotic bacterial infections (List of zoonotic diseases – GOV.UK (www.gov.uk)).  The reindeer that come to us are captive rather than wild, but even so they are still coming onto healthcare premises and need a review. The task therefore, although a joy, does have a serious aspect in terms of ensuring that the area is properly set up in order to permit the patients to visit, whilst ensuring that they are kept safe and not exposed to any risk.

We work with both the school and Santa to ensure that:

  • All animals are established in an environment that supports safe handling of the reindeer to avoid injury for them and anyone interacting with them.
  • Signage and other provision is made to ensure that there is no eating or drinking near to the animals or their enclosure, to reduce any infection transmission risk.
  • Hand hygiene facilities are available for hand hygiene after contact, especially as the patients will feed the reindeer.
  • Decontamination equipment is available to ensure the area can be adequately cleaned after Santa and his reindeer leave to visit other children.

Last year when we inspected we also had the added aspect of ensuring that Santa was SARS CoV2 free and was protected from any exposures whilst on-site.  This included having Santa complete a health screening questionnaire, including questions like whether he had any symptoms or SARS CoV2 household contacts, such as Mrs Claus, in order to assess his SARS CoV2 transmission risk.  He also needed to wear personal protective equipment i.e. fluid repellent surgical masks, to protect him and the children and young people.

This was a new aspect to the visit that made it more challenging and certainly inspired the patients to be differently engaged and ask questions such as: how does Santa manage to avoid the quarantine restrictions linked to visiting red countries?  and if Santa was vaccinated?  We responded that Santa was of course vaccinated as he had been part of the SARS CoV2 vaccine clinical trials and was therefore an early adopter of the vaccine.  We also talked about the fact that because he could manipulate time, he and the reindeer had plans about how they were still going to be able to safely visit all households and quarantine as necessary.  We also discussed that whilst he was with us we would provide him with personal protective equipment training, in the same way their clinical teams have, to ensure that he is kept safe and also protects the children he encounters along the way.  It turned into a really good way to talk to families about how we use a variety of measures in hospitals and healthcare to keep people safe, and to emphasise that although masks look scary they are actually a really good way of protecting everyone.

This experience brings me joy every year but last year in particular it reminded me that keeping people safe and raising awareness of what we do, does not have to exist in isolation from activities that are fun and engaging.  I love visiting the reindeer, however seeing patients be inspired to ask questions and explore IPC in a way they may not feel confident to do normally, also made me aware that it may be not only a joyous experience but a useful one.  It turned something fun for all involved into something that was also educational and supportive of good practice.  So this year as well as making sure I have enough carrots I will be ensuring that I’ve thought about how to make the most of this unique encounter to make a difference for everyone involved.

All opinions on this blog are my own

Guest Blog by Phillipa Burns: Part 2, the view from the finish line

In the final of a series of blog parts linked to taking FRCPath parts 1 and 2, the wonderful Phillipa Burns has written a guest blog about her recent experience of sitting and passing part 2 in Medical Microbiology.

Phillipa Burns works as a Principal Clinical Scientist (HSST) at Hull University Teaching Hospitals NHS Trust. She has over
two decades of diagnostic microbiology experience, and is currently completing the Higher Scientific Specialist training Programme, with a planned Doctoral graduation in 2024 from the University of Manchester. As she recently passed the her FRCPath in Medical Microbiology in 2022 she is ideally placed to talk about what her experience has been, especially now the exam has gone back to face to face after several years online.

I read the guest blog by Ren Barclay-Elliot about her recent Part 1 experience; it was so generous and thoughtfully written that I thought the kindest gift I could give back would be a piece on preparing for Part 2.

I must say though that the kindest thing you can do for yourself after Part 1 is to take a break, revive and recharge, irrespective of the result, before reaching for the books again.

Trust me when I say that HSST is a marathon and not a sprint; build your reserves before stomping up the next hill.

The caveat to my gift of kindness is that I only have experience of the Medical Microbiology exam; but hopefully this will still be helpful to other life science pathways.

A little about me

I started HSST in 2018, after 16 years working as a Biomedical Scientist in Medical Microbiology.

I think my career can be best described as “mostly wore a white coat and often wore different hats!”; this is true of many scientists that pick up the hats of quality, safety, research and management.

Entering HSST as a direct entrant allowed me to leave all my previous roles and responsibilities behind and to focus on the completion of the programme; I know that the vast majority of HSSTers are master jugglers who are completing this course alongside another role.

Truly, you are all amazing.

First Steps

Part 1 was the first examination I had sat in 14 years and I was revision rusty; I got by with a little help from my friends and by reading guidance and making short notes.  I knew that this approach wasn’t going to cut it for Part 2.

Decide when you want to sit

Plan the best time for you and be honest with yourself about your readiness and your resilience

Look at what is ahead in the calendar; you will be giving up a lot of time and social events in the name of revision so if you have huge life events on the horizon factor these in.

Even if your sole reason for preferring the attempt to be in the Autumn is that you revise best in the outdoors, then make that choice and enjoy reading in the summer sun

Timing really makes a difference, especially if you have children to factor in. I have small children and I couldn’t sacrifice another Christmas to revision; find your redlines and stick with them.

Find some study buddies

Ideally a small group, 4 or 5,  that covers a range of knowledge and skills.  Studying with a both medical and scientific trainees worked best for me.

You need to like who you revise with and it needs to be a safe space; you will share your worries, knowledge gaps, the things everyone expects you to know but you just can’t keep in your head!

It has to be judgement free and welcoming.

Do not worry if it takes a few groups before you find your tribe; I knew that early morning revision groups were never going to work for me but a few fellow night owls were a great find.

Keep the information flowing with chat groups and emails; it is amazing how much information a determined group can gather.

Be prepared to do your fair share of the prep work; exam revision is stressful – especially towards the end and it really helps if everyone does their bit.

Notes

Part 2 checks your knowledge recall under pressure in the format of OSPEs, SAQs and LAQs.

The whole curriculum is covered; this feels daunting but if you break down the revision into key topics and cover one or two a week you easily get through it.

Most of the exam is skills learnt from doing the day job; they are just “stretched” to cover every series of unfortunate events that can happen with cases. It really helps to reflect on the calls you have had during the day and think “what would I have done if that was a child/drug resistant/linked to another case/pregnant woman etc.,” Let your imagination run wild and really challenge yourself until you reach a layer of confidence with your reasoning and decision making. If there are things missing in your day job, find courses and ask for placements.

Make notes that are aligned to the exam format; covering the clinical, infection control, treatment, public health and laboratory identification elements.

Revision

Team event or lone wolf; your approach has to work for you.

I learnt more with a team, and they added depth to my knowledge; the diversity in the both my study groups was phenomenal – I was always awed by the talent in the room and the experiences that my peers had

The exam covers guidance and it is easy to know what you do in your workplace and why; but you need to know if that is evidenced in national guidance, recent studies – be critical of your own practice and look at the quality of the evidence. Also prepare for situations on the edge of the guidance, the grey areas and when you need an expert consult.

Read around the subject; big studies that have changed practice – challenge yourself to understand the design and outcomes. Social media is invaluable for “Top 10 ID papers this year” and tweetorials.

Be able to write, the exam is 6 hours of handache! I spent the last month of my revision hand writing until I was quick enough to tackle a 3 hr paper. A lamy fountain pen proved to be my saviour.

The Exam

Get to the venue early, ideally the night before.

Plan your route and make sure you have all your ID and stationery in your bag.

Take snacks, the need for a sugar hit mid paper was very real

Take study leave before and slowly ease off the revision so that you are rested; this is really hard to do but it is easy to become sleep deprived and to underperform in the verbal stations due to fatigue

Wear smart casual, but comfortable, clothing – it is a long day

Take time after the exam to decompress and debrief, by this point you will know if your study group are sharers and talkers, respect the wishes of those that just want to forget until results day

The whole experience left me very tired, unsure if I hit the brief; this is completely normal.

Results Day

Have a plan, my consultants checked my result for me! I was horrendously nervous and sleep deprived.

Agree with your group if you are going to wait for people to check in; remember this is a tough exam and fail is just a “first attempt at learning”

Check in with the quiet people, give them time to talk about it and reflect.

Celebrate the milestone, pass or fail, reaching this peak in knowledge is a huge achievement.

HSST is so relentlessly busy it is easy to swap the FRCPath preparation for the other items on the to-do-list; I have taken my own advice and had a little pause to just look back at the progress I have made in the past four years.

I have timetabled in events with my much missed extended family & friends; these became the extras that I struggled to fit in whilst revising and I have put some other books, rather than podcasts, on my audible app.

Tomorrow, my fellowship with the Royal College of Pathologists will be ratified and I can officially use the designation, FRCPath; I have asked others – “When does it feel real?”,  this seems to be a common feeling when you have recently crossed the line. I cannot pretend to be unaffected by the enormity of the achievement, I will be smiling for months (maybe years) and I fully expect to sob with joy when I see my study buddies at the investiture ceremony in February.

My final words are “that if you can see it, you can be it”; be proud of the seven little letters (and the many others you have earned), show your career path and light the way for others to follow.

Plenty of people showed me that this is possible, and to them I am forever grateful.

Check out the other blog posts in this series:

Guest Blog by Karen Barclay-Elliott: Life, the universe and surviving FRCPath part 1 – December 2nd

Your Wish is My Demand: Here are some of my tips for sitting MRCPath in Micro/Viro – November 29th

The Trials and Tribulations of High Stakes Assessments: How I still remember everything about FRCPath – November 25th

All opinions on this blog are my own

Guest Blog by Karen Barclay-Elliott: Life, the universe and surviving FRCPath part 1

I put out a post earlier this week on my experience of sitting MRCPath or FRCPath part 1, but as, in Healthcare Science terms, I am a bit of a dinosaur and sat mine so very long ago I put out a call for someone to help out who has more recent experience. The wonderful Ren Barclay-Elliott was a life saver and jumped to my aid. Ren is a virology clinical scientist based in the Midlands with an interest in congenital and childhood infections, fantasy novels, and cats. She also has demonstrated she has a generous heart by not only agreeing to write this but turning it around so quickly for the enjoyment and aid of all of you 🙂

It’s Me, Hi!

A quick introduction to who I am and why I’m writing this – my name is Ren, and I’m a clinical scientist in Virology and Molecular Pathology. I completed the NHS Scientist Training Program in Infection Sciences in 2020 and have been working in virology ever since. After a year or so of putting off sitting my FRCPath Part 1 exam, I finally gathered up the courage and willpower to attempt it in Autumn 2022. (Spoiler alert – I was fortunate enough to pass on my first attempt.)

I found Part 1 incredibly dauting for so many reasons – not least of which was the fact it was the first exam I had sat since finishing the STP, and there had been a whole pandemic in the interim! Not to mention it is an incredibly broad exam, and as a virologist I had promptly forgotten about 90% of the bacteriology I had ever known the second I finished the STP. I was given a lot of advice about studying for, and sitting, this exam over the last year, as well as gathering some (possibly questionable) wisdom of my own – I hope that in sharing it, I can make Part 1 a less intimidating prospect for anyone sitting this exam in the future!

The Exam Itself

In this post-pandemic world, many things look a little different to how they used to. Part 1 is no exception – at least for the time being, the exam is entirely online. This can be quite an odd experience for those of us used to huge, drafty exam halls and ominously pacing invigilators. There are certainly a lot of perks to this way of doing things – mainly not needing to travel to physically attend the exam, but also the comfort of being at home and being able to think out loud if you come across a tricky question.

The exam itself is simple – 125 best-answer multiple-choice questions in 3 hours. When they say “best answer”, they are not kidding – be prepared to think “but these could ALL be right!” at least 30 times throughout the exam. Fine-tuning your decision making to be able to narrow in on the most likely to be right is a skill in itself, and one that takes time and practice to develop. I found that practicing multiple choice questions from a few different sources really helped – more on that later! Almost everyone I know who has sat the exam finished well before the time limit and had plenty of time to go back and check their answers a few times.

Help – How and When Do I Study?

So now you know what to expect on the day of the exam. But what about the weeks or months leading up to it? How do you prepare for an exam where the syllabus is just “literally everything you have learned up until now”? How long do you need to study for, and how much time do you need to spend on any given topic? Unfortunately, as with many things in life (and in Part 1 for that matter!), there is no single right answer. I was given the general rule of thumb of starting to prepare about 3 months prior to the exam, but I know people who have spent as little as 2 weeks or as long as 18 months preparing for their first attempt.

Personally, I started off very slowly about a year before the exam – not with full-on studying, but by doing fairly low-effort things like listening to podcasts, making a point to attend MDTs where I knew interesting cases would be discussed, and starting to note down areas where I knew I had a weaker knowledge base and reading up on them whenever I had downtime at work. I started studying in earnest about a month before the exam and found this was sufficient time for me to cover everything in enough detail to feel confident.

AS for how to study – there’s as many correct answers to that as there are people on the planet! However, I have tried to summarise my best advice below…

Find Different Ways To Learn

I have always thought of myself as a very visual learner – come exam season in uni, the walls of my room would always be plastered in meticulously colour-coded mind maps covering every possible topic I could be examined on.

An actual picture of the walls of my bedroom circa March 2017 while I was studying for my MSc exams

However, once I got to studying for part 1, I found this approach wasn’t working so well for me anymore – not least because I don’t think I have enough wall space in my whole house for the number of mindmaps I would have made! For a while I kept stubbornly trying to stick to my tried-and-true method (after all, it had gotten me this far!), but eventually I had to admit that I needed to be more flexible in how I learned. I ended up with a huge variety of methods depending on the topic I was learning and how I was feeling on any given day – printing and highlighting guidelines, writing flashcards, making (and delivering) powerpoint presentations, and teaching my (non-lab-scientist) husband, who now knows WAY more about carbapenemases than you’d expect from a high school chemistry teacher.

Trying out practice questions was massively helpful, both for getting me ready for the multiple-choice question format in the exam, and to give me a way to assess my progress as I went along. I found the BIA LearnInfection resource to be invaluable, as well as the infamous “orange MCQ book” (more formally known as “Infectious Diseases, Microbiology and Virology: A Q&A Approach for Specialist Medical Trainees” by Luke S P Moore and James C Hatcher).

I also found listening to podcasts to be a great way to learn – I would thoroughly recommend ID:IOTS (bonus points for the hosts’ Scottish accents, which really helped to alleviate my homesickness!) and Febrile (bear in mind that this is American so not all of their guidelines are identical to those used in the UK, but it’s a great resource and very entertaining). Both are available on Spotify!

Make It A Game

Let’s face it, studying can be incredibly tedious. After finding myself staring blankly at textbooks for hours on end, barely taking in a single word I was reading, I realised that I needed to make studying fun – or at least, not mind-numbing! I found that games were a brilliant way to re-approach a subject with fresh eyes and remember that I am studying this subject because I genuinely love to learn about it. One of my favourite resources with Microbial Pursuit (https://firstline.org/microbial-pursuit), an online trivia game that my colleagues and I got very competitive over! One question is published each day, so it’s great for doing a little bit of learning every day, or you can dive into the back catalogue if you want a more extended study session. It’s a fun way to test your knowledge across the whole breadth of infection science, and useful for picking up little facts that you may have missed in your reading.

I found this approach really important the closer I got to the exam – it was a useful way to remind myself that learning can be fun and exciting, and I wasn’t just memorising screeds of information for the sake of it.

Create Systems That Work For You

Part 1 covers a frankly enormous amount of content, and it can be utterly overwhelming trying to find a way to cover all the necessary material without accidentally missing things out. There are plenty of ways to split it up, and some may work better for you than others! Some systems that I, or people I’ve spoken to, have used include:

  • Going “head to toe” – learning organisms associated with clinical syndromes starting with brain/CNS infections, then down to ENT, respiratory, cardiac… you get the idea. Don’t forget to include skin and soft tissue infections if you’re using this method – it’s surprisingly easy to forget about!
  • Going through organisms by classifications – e.g. start with Gram-positive cocci, then Gram-positive rods, then Gram-negative rods… you get the idea. This can be particularly useful if you’re struggling to remember things like viral structures – if you learn all of your DNA viruses back-to-back, it’s easier to remember they are all in the same group then if you learn them individually by the clinical presentations they are associated with
  • If you have a lab background, then going “bench to bench” can be helpful – learning about organisms/lab tests/clinical presentations associated with wound swabs vs blood cultures vs tissue samples can be a great way to learn if you have a lab background since you might already unconsciously group things in this way
  • Picking interesting cases – if you have a lot of clinical time and see plenty of cases, then you might come across (or be able to construct) memorable cases that help you to learn about lots of different concepts, from diagnostic tests to antibiotic stepdown choices, associated with a single patient

You may find a system that works perfectly for you first time, or (like me) you may need to chop and change as you go along. I would definitely advise going in with a plan though – even if you end up changing it later, it gives you a good framework to start with and refer back to so that you can be sure you haven’t missed anything.

There Will Be Some Questions You Know the Answer To, And Some You Don’t…

While this seems like a fairly obvious statement, it was one of the most helpful pieces of advice I received while I was preparing to sit Part 1. You are never going to know absolutely everything – there will always be at least one question that throws you for a loop and makes you think “how on earth am I meant to know that?!”. All you can do is make your best guess and then move on – while the exam isn’t unfair or out to get you, it is meant to be challenging and everyone has blind spots – don’t let it faze you, just move on. On the flipside, everyone has strengths as well, and you are likely to find far more questions that make you think “Yes! I know this one!!”.

I had to learn to bear this in mind especially when talking to friends or colleagues who had sat the exam before me – people love to tell horror stories starting with “You wouldn’t believe what they asked about when I sat it…”! There are always going to be questions designed to stretch people and test the limits of their knowledge, but these do not make up the majority of the paper. 

Don’t Stress!

I am fully aware that my friends, family, colleagues, and literally anyone who has been in my general vicinity in the last few months will all laugh uproariously at my hypocrisy when I say this, but try not to stress about Part 1 too much. While preparing for any major exam can feel overwhelming and world-ending, it is not the be-all and end-all, and does not reflect your worth as a scientist or as a person. I know many excellent scientists who are outstanding in their fields who did not pass on their first attempt. While Part 1 is a significant milestone, even getting to the point of sitting it is an achievement to be celebrated, regardless of the outcome. Treat yourself with kindness, take breaks when you need them, and ask for help early and often.

Best of luck to everyone sitting Part 1 in the future – I sincerely hope that my ramblings have been at least a little bit helpful. And remember – at the end of the day, it’s just a test. You will be okay. You got this!

All opinions on this blog are my own

Your Wish is My Demand: Here are some of my tips for sitting MRCPath in Micro/Viro

I posted about the FRCPath exam last Friday and in response I’ve had some people reach out and ask about MRCPath (or FRCPath part 1) and if I had any thoughts that might help in preparing for it.

Now, I have a bit of a part 1 confession. I sat part 1 in 2007, the exam was in September and my contract was due to end in a matter of weeks, and I had no idea what my next steps might be. In those days you had to work for 4 years to get your registration as a Clinical Scientist, but the training scheme only funded 3. You therefore had to find someone prepared to fund your 4th year, otherwise you dropped off the scheme with no registration and therefore you couldn’t get a subsequent role. I registered to take part 1 in case my contract ended, as I thought it would give me the best opportunity to try and find someone who would pay for my 4th year if my Trust couldn’t keep me. When I registered the exam conditions (as that time) said it was possible to defer the exam, but didn’t really give any more information. Two weeks before the exam my contract was renewed, and to be honest as it was looking likely I hadn’t even begun revising. I was just waiting for it to become official so I could confirm the deferral with the college.

My continued employment confirmed I phoned the college to defer, they said, of course! They also said that they hoped that I knew that although I could defer I would have to pay another £384 (see I still remember it to this day) to sit in the spring. I put down the phone and hyperventilated in the infection control office. I couldn’t afford another £384, I was a trainee who barely made ends meet on less that £20,000 a year in London. I walked out of the IPC office and into see my consultant (John Hartley, always a legend) who looked me in my tear-stained eyes and said, ‘well you’d better go home and start revising, see you after the exam’. My husband told me to hit Foyles bookshop on the way home, and that was that. I cancelled everything for the following 2 weeks, revised for 18 – 20 hours a day, and my poor husband asked me more exams questions than I’m sure he’d care to remember. I sat the exam and passed with (I believe) 80%, but this all means that my pathway to part 1 is probably not the one I would recommend for others. So instead of telling you more of what I did, below are some thoughts about how I would do it if I had to sit the exam over again.

Know what’s expected

Part 1 hasn’t changed much in structure since I sat it, although some of the focus of the question content has been updated as medical trainees are now joint Infectious Disease/Microbiology. There is, as expected, plenty of information on the Royal College of Pathologists website about this, but here are some of the things that I think are important to be aware of. The exam is aimed at people who are fairly early on in their speciality training, so for medical trainees this means those who have spent a year or so as a registrar. The exam itself is a different beast from what I described in my post on sitting FRCPath. It is a single 3 hour exam, consisting of what the college calls ‘best answer’, what the rest of us call a ‘multiple choice’. It covers Microbiology and Virology, as it is the same part 1 for both later FRCPath options. For context, unlike FRCPath, most people I know sitting part 1 prepped hard for about 6 weeks rather than for 6 months before the exam.

I’ve spoken to a few people recently who were prepping for part 1 and they were spending most of their time running case studies and learning a lot of detail about HIV treatment etc. I can only talk from my experience (I don’t write or have anything to do with the exam) but for me that is much more FRCPath prep. I think part 1 is much more about understanding the fundamentals of clinical microbiology: whether viruses are DNA or RNA, single or double stranded, what is the difference between decontamination and sterilisation, what are the key toxins associated with Clostridial species? There is more clinical in it now than when I sat it, and if I can I will find someone who passed more recently to write a guest blog (drop me a line to volunteer), but it’s mostly about identifying clinical risk. Part 1 is a lot about facts and memorisation of microbial characteristics and so books are where it’s at!

Get a current view

This brings me onto my first top tip. Find someone who has sat the exam recently and pump them for information. The thrust of the exam changes from year to year and so to really get prepared you need to get the most recent view you can. No one is allowed to share question information, but they can talk through and prepare you for what the current clinical vs organism balance is. They can also talk you through how much basic microbiology you need to bring into the room, and what the best resources are currently available to help you prepare. Most of your consultants will have sat this exam a long time ago and so you really need to be reaching out to your peers. If you are lucky enough to have a consultant in your department who is involved in writing the exam questions, they are still likely to be restricted as to what guidance they can give, so using your network is key.

Find a study buddy

One of the things that I would recommend for any college exams is that you find a study buddy. I did both of mine on my own, partly because of circumstances and partly because not that many scientists were sitting the exams back then. If you can pair up with someone else you will have a much easier time of it. I think this is probably true for three main reasons:

Firstly, you will probably have different areas of strength and weakness. For part 1, if you are a virologist try to find someone who is mainly a bacteriologist, you will then have a ready-made expert to help you go through concepts and visa versa. Even if you are both from the same main domain you are likely to have different interests. This is likely to help you with splitting some of the prep work. Also, if you are like me, you may only realise the gaps in your knowledge when you are trying to verbalise explanations to someone else and so it helps to have someone you can talk things through with.

Secondly, networks are really important and the more of you there are, the larger your combined networks are going to be. You will use your network to find good resources, have prep conversations and sign post you to key topics or challenges. They are the people you will go to in order to discuss how long you should prepare for ahead of the exam, to send you some test questions if you struggle to access them elsewhere, etc. As I said, you can do this on your own, but the richer your access to these, the easier your prep is likely to be. They may even be able to guide you to places that support funding the exam.

Finally, these exams are periods of high stress, by doing it with a peer you can provide each other with support during the process. Sometimes just having a friendly face to walk into the exam room with can make all the difference, or who you can text ‘OMG what is Citrobacter, I’ve had a massive blank’ when doing your reading. Building these relationships will help you throughout your career, and there’s nothing like shared high stakes moments to help bonding 😉.

Read not once but twice

There is a lot of exam technique that can help in passing both part 1 and part 2, and the sooner you start refining yours the easier it will be. The greatest piece of advice I received about sitting part 1 was ‘read through the question twice so you answer the question they’ve asked, not the question you think they’ve asked’. To be honest, I think this is the reason I passed, not because I am super smart or because I was well prepared.

The questions themselves are sometimes long. There will often be a bunch of information that can lead you to jump to conclusions about the answers the examiners are looking for. Most of the questions will have 4 options for answers. A lot of the time you can easily exclude 2 of them, just by reading the question properly. If you skim read the question though and don’t take a minute to appreciate what they are actually asking you can however go down a rabbit hole in your train of thought and pick one of the 2 that were only there for this reason. Save time by reading each question twice and asking yourself ‘what is it they are really asking me’.

Reading not once but twice also extends to checking the barcode answer sheet (if they still use these). It’s far too easy to get out of sequence or accidentally skip a line. No matter how close you are for time (and to be honest you should have plenty to spare), make time to cross-check your answer sheet at least twice. It will save you from unnecessarily losing precious marks.

Don’t over complicate things

Having said that you need to read the question carefully, there was one other thing that I remember finding really challenging in the exam itself. There was an extended matching question where you had to match the type of organism with the right molecular diagnostic test. I remember looking at the list for ages and thinking, ‘I could make a case for using any one of those for any one of these organisms’. Therein lies one of the other problems. It is possible to overthink your responses if you know too much in an area. As I said before, this exam is aimed at medics roughly a year into their training. If you have been a jobbing scientist for some time there will likely be things that you know in far greater detail than they would. It’s important if you find yourself in that kind of spiral to step away and think what would be the approach to someone just starting out in answering this question, what would the most obvious answer be, and let that guide you. Sometimes you may need to move onto other questions and to then return with a fresh set of eyes.

Go old school

One of the common traps we fall into as scientists is believing that all the questions will be based on the latest techniques. Now, it may have changed, but when I sat the exam there was a LOT of old school microbiology in there. Some it now feels old school as most of us don’t use many APIs and biochemical tests anymore. There is however quite a lot of this information that is intrinsically linked to organism characteristics, and as I’ve already said that is a lot of what this exam is about. So, if I were you, I’d pull some microbiology textbooks (not just clinical microbiology) and remind yourself what a VP/citrate/indole etc, test looks like and what they could differentiate. Remember that parts 1 and 2 are sat by international clinicians and so the exam has to serve a global purpose and reflect widely available diagnostics.

Listen to the advice but go your own way

Now, I’ve just written 2000 words of advice but I suppose this is one of the key ones. You don’t have to listen to any of it. Everyone prepares and studies for exams differently. What works for me may be completely the wrong thing for you. There is plenty of advice out there, and there are many people who will be more than happy to share their thoughts and opinions with you. Only you know what might work for you. If you’re unsure, try out different things in plenty of time and discard the ones that don’t serve you. I’ve already talked about my rather unconventional route to sitting part 1, but I made it work. You will make whatever route work that is right for you.

If at first you don’t succeed

Finally, sometimes these things don’t go your way first time. Sometimes, the questions aren’t what you expected. Sometimes, you frankly just have a bad day. I’ve known plenty of people who did not pass first time, all of whom are excellent in their posts. This can be a bitter pill to swallow for high achieving scientists who aren’t used to failure. Bear in mind however that it is more common in medical exams for people to sit multiple times. These exams are benchmarks for safety, and so there is understandably little wiggle room in terms of marks.

Sometimes, when people fail they close off to that failure and double down, rather than opening themselves up to what it can teach them. If you can, be open and take all you can from it. You will come out all the stronger. If failure happens to you, and I know this is hard, you have to let it go. Sitting these exams is in itself a learning experience. You will gain valuable insight into the exam itself to help you prepare for the next time. You will learn a bunch about how to revise, what to revise and how to read the questions. In short the process in itself will make you better, irrespective of the outcome, if you open yourself up to the learning it can provide.

Resources

There are a lot of great resources out there, and I’m sure your networks will help you identify even more. Below are just a few things I found useful when I was sitting the exam or that some of my amazing trainees have signposted that have been useful to them. I wasn’t involved in creating any of them, so they are just suggestions. As ever, pick and choose what works best for you.

https://firstline.org/microbial-pursuit

Not a resource, but if you want to sympathise with my husband for living with the girl who just won’t stop studying, here is a Girlymicro podcast that we recorded about that very subject.

Hope this is all a little useful and please do drop me a line and let me know how you all do and if you’ve got any advice to add!

All opinions on this blog are my own

The Trials and Tribulations of High Stakes Assessments: How I still remember everything about FRCPath

Seven years ago this week, I found out I passed the exam to be awarded Fellowship of the Royal College of Pathologists (FRCPath) in Medical Microbiology. It is still the only exam, other than my PhD viva, where I vividly remember not only how it felt to sit it, but also how I felt both awaiting and getting the results. As others currently await their outcome, I’ve been reflecting on what it was about this exam that means, even 7 years on, it has had such a lasting impact on both my career trajectory and my memory? Also, why did I, as a scientist, decide to sit it in the first place?

For me, it started with you can’t

I’ve started a post that I’ll publish another time about the journey from trainee to Consultant Clinical Scientist, and the joys and pitfalls that entailed. For me, although my path may appear winding, I always knew what I was working towards and had a list of things I knew I would need to accomplish to get there. Knowing what was needed was never the issue. Knowing how to achieve it was often much less clear.

Getting FRCPath is essential to becoming a Consultant Clinical Scientist in microbiology. There are, however, 2 common ways of achieving it, by publication or by exam. I knew plenty of people who had FRCPath by publication, and it was a route that was achievable by me, as I was also on a clinical academic pathway. The problem for me was, however, that I was in a patient facing role, making patient-based decisions over a broad spectrum of activity. To me, FRCPath by publication would have given me credibility in a different way and would not, therefore, have been perceived as equivalent by my medical colleagues. I was just not sure it would fully support the work I was undertaking or aspired to undertake. So it was that I started to think that FRCPath by examination was the only way forward for me.

(Side note – I truly believe that either way of attaining Fellowship is valid. I believe it’s just about the kind of work you are going to do once you have it. That decision should drive your thinking about which is the right choice for you.)

I don’t think I’d realised how many feathers I would ruffle along the way by making that decision. One of the challenges, and also eventual benefits, is that a lot of people will give you advice along the way, and some of it will make you question your decisions. This eventually enables you to have an even greater understanding of your choices, but at the time, it can lead to a lot of self-doubt and require a lot of self-reflection. In this case, I was told you can’t by a LOT of people on the road to even sitting the exam. I was told that you could only pass if you worked as a registrar in a teaching hospital for 3 years. I was asked (even at the mock and the exam) why on earth a scientist should be allowed to sit a medics exams and what kind of job did I think I would get afterwards. In just about every way I was told that someone like me should just give up and choose a different path. Any readers of this blog know how well I deal with those kinds of responses. So, like so many other times, I had my reflections, dusted myself off, and came back with even more determination that this was the right path for me. Determination, however, doesn’t always change outcomes. All I’d done was decide to sit an exam, that was all rather different from passing it.

No one said it was going to be easy

What is FRCPath by exam all about anyway and why do people think of it as such a defining moment? It has changed a bit more recently, especially through the pandemic, but when I sat it, the exam was about 30 hours carried out over 4 days. I’ve always described it as a bit like The Great British Bake Off of microbiology exams, but without the benefit of ending the day with cake. Day 1 included written papers (essays, short answers, critical appraisal). Days 2 – 4 were wet lab practicals, with 9 written exams interspersed throughout the days. You would just be told during these to put down your loop and move to another room where a written paper would be waiting for you. These further written tests included: virology, quality, spots and public health. In my year they were closed book, but in previous years some of these had been open book. Between sessions you would be given new specimens or further clinical information on ones you’d already processed to make further laboratory actions. Doesn’t sound too bad…….right? I didn’t think it would be, or I hadn’t quite conceived of how hard it would be until I attended the mock exam up in Blackpool in June 2015.

I knew before going to the mock that the pass rate was about 40% for the real thing and I knew that everyone described it as the toughest exam they had ever sat. I just don’t think that I KNEW it. The challenges of the exam are hard to describe. Some of them are physical, how many of us physically write essays for 8 hours a day these days. I have a history of repetitive strain injury and so it was interesting to come up with a painkiller strategy that would enable me to perform as well at the end of the day as at the beginning. I was surprised at the extent of the exhaustion. Usually, I prep enough that I arrive at the exam in a ball of flames and adrenaline gets me through the day so I can collapse in a heap afterwards. With this exam you can’t do that. At the end of day one you need to study and prep more for day 2, at the end of day 2 you know there is stuff you need to pick up hinted at in the specimens so you can be more sure you know your stuff for day 3 etc etc. The exhaustion therefore accumulates until (at least for me) by day 4 I was working in an exhausted haze.

The other thing that makes this particular exam challenging is that it covers EVERYTHING. They can ask about any organism, any presentation, any vaccine, any treatment. Part of the reason it was designed that way I think, was to ensure that come day 4 when you are exhausted you can still make safe clinical decisions and spot pitfalls and risk. Normally when you walk into an exam room you have a syllabus that enables you to have a fairly reasonable chance of targeting some of your learning and determining likely content. This isn’t that exam, and therefore a lot of the exam techniques you’ve previously used are not quite as applicable. This one is more about maintaining your calm, being structured and clear in your responses and making life very easy for your examiners, in terms of finding and making your points. You have so little time for each of the components that clarity of both thought and communication are key, and practice is the only thing that will get you there, that on top of all the revision you can cram into your brain. (If useful the link to some of the content I prepped to help with revision in 2015 is here)

The ugly truth of coming face to face with who really are

All of the challenges, physical and mental, are nothing compared to the emotional and psychological roller coaster that you go through. I’ve always been fairly fortunate, in that until FRCPath I’ve never come up against a challenge where I thought I couldn’t conquer it if I worked and applied myself hard enough. It’s why I talk all the time about how it’s important to know you’re why. Your why will get you through when other things fail, your why means that you know quite what price you are prepared to pay and what you are prepared to sacrifice. Everything in life comes with a cost, life itself is resource limited. Knowing how much you value something means you know when to stay in the game and when to walk away. That has been true of every exam I’ve faced until FRCPath. FRCPath forced me to face something different. It’s the first time in my life where I’ve had to look myself in the mirror and ask myself whether I actually had what it takes. Not whether I had what it took to put in the time, to face the physical toll or wanted it enough, but whether I had actually reached my limit. Was this just something I would never be able to achieve no matter how hard I worked, but that I as a person would just fall short. I can tell you, apart from fear for my loved ones, I have never felt fear like it.

Now I’m not telling you all this to put you off sitting the exam, far from it. For me it was a life changing process, not just because of the fact that it changed my career, but because of what I learnt about myself. It made me look myself in the mirror and face something that really scares me………….failure. I can in a logical way sit here and talk about how the things I’ve previously post about impact on how I feel about failure, or how because of what happened to my sister this career means more to me than I can logically explain. The thing is none of that can encompass how I felt when having a full on panic attack outside of the exam room before going into short answers, because it had gone VERY badly at the mocks. Just not being able to find my breath. Knowing I could walk away, and just take the easy way out. Then finding the strength of resolve to make a choice, to press the button on my phone and turn on my ‘get psyched mix’. To forcibly calm my breathing and to walk into that exam room, face my fear and turn over the front page of the exam paper. I learnt more about who I am in that moment than sitting 100 easier or more straight forward exams could have shown me, and for that I am strangely grateful.

Is this the best way to test competence?

The question is, should any exam take you to that place? What is it really testing? I was told that most medical exams involve candidates sitting multiple times, it’s common for people to fail at least once, which with a pass mark of ~40% for FRCPath feels likely. I don’t know for definite that this is the case, it’s just what I’ve been told by registrars who’ve trained with me. It is true that I know many highly competent Microbiology Consultants who failed at least once. The other thing is that this test doesn’t really represent clinical practice. In the real world I would consult guidance and other sources if I had any doubts, competence isn’t just a matter of recollection, it’s mostly how we use that information in practice. At the end of the exam one of the education leads at the college turned around and congratulated us, they said not having quit and making it through 4 days was a success in itself. I do see the value in making sure that those sitting these exams can make safe decisions when they are exhausted, after all most of us will take calls when that is the case. I’m not sure however as an educational driver we couldn’t be doing something better. The exam has changed a lot since I took it, it’s now a one day exam. In some ways I’m saddened by this, it was almost a rite of passage that me and others bond over to this day. I also worry that by removing so much of the lab side of things and reducing the exam hours so drastically it could be pretty hit and miss about the content suiting candidates, rather than truly testing against the curriculum. Anyone who works in education knows that assessment design however drives educational engagement. Although I’m not by any way an expert in this, I do think that high stakes summative assessments have cons as well as pros, and just because I’m sad that the exam/rite of passage is under review does not mean that change is a bad thing.

What happens when there is no plan B?

One of the problems with high stakes summative assessments i.e., those taken at the end of learning and are pass/fail, is that there is often no plan B. This is especially true for FRCPath where there are a limited number of times you can sit it before you are not permitted anymore (x4) and will therefore never become a consultant. For someone, such as myself, who is not from a wealthy background and was being paid a junior scientist salary, the costs associated with this exam could be prohibitive. Sitting the exam was over £1000, that combined with hotel accommodation, books, paying for the mock, meant paying over £3000. I have friends who spent over £10,000.00 in 2 years sitting the exam 4 times. In a world where accessibility matters a financial barrier should not mean that someone cannot progress in their profession. Currently the exam in online and so the barriers are not the same, but the exam fee itself can add up. I needed to pass first time, not just because I couldn’t face losing another 6 months of my life, but because I was pretty sure I couldn’t afford to sit it again. I went all in and came out the other side, but I know of people who have found the process damaging, rather than the freeing experience it ended up being for me. It is an immovable block to your future and failing really does mean that you could be dealing with the consequences for the rest of your career, a career that you will have already invested years into.

The payoff was worth it all

Having been through the process though I don’t regret it for a minute. It is still one of the things in my life I am proudest to have undertaken. It has given me the courage and conviction to fight as I had stared into my soul and knew that this is what I wanted. I wouldn’t be a consultant without it, not just because I wouldn’t be qualified but because I wouldn’t have had the courage to fight for it. I still remember my candidate number, it’s become one of my favourites. I still remember crying uncontrollably when I looked at the website and saw the below, and then sent this screen shot to everyone I knew in order to make sure I hadn’t read it incorrectly.

The other thing to say is that there are lots of people out there who will tell you there is only one way to pass this exam and frankly I don’t believe that is true. The exam is a milestone on the pathway to where you want to end up. In the same way that FRCPath by publication is the right route for some people, you can pass this exam by not being a registrar for 3 years in a teaching hospital, after all, I did. It all depends on what your aspirations at the end of it are. If you work in public health you are probably not aiming to switch to being a Consultant Clinical Scientist doing on call in a district general, but to upskill and improve your clinical competence to continue working in your area. If you are like me with an aspiration to work and specialise in Infection Control in a paediatric setting, then your aspirations will be different again. It is OK to sit the exam and plan with this in mind and to make your own path. Everyone is different and where we want to end up does not have to be the same, nor the path we take to get there. The challenges we face along the way are sometimes more important that the destination. Even when it’s hard enjoy the journey, enjoy the challenge if you can and for sure enjoy the person it enables you to become. Finally, if it doesn’t work out first time know that there is life beyond, don’t let my fear of failure make you doubt that that is the case. We are after all definitely more than the sum of our grades.

All opinions on this blog are my own

A new Girlymicro podcast where we talk about what it’s like for someone living with an FRCPath candidate

Clarity is Key: The role of learning agreements in supporting learner success

It’s that time of year again and many of us will be taking on new trainees, getting to know new students or supervising new PhDs. I thought it was time therefore to share something that I’ve found increasingly useful and have now set out to cover in initial meetings with learners, and that is the development of learning agreements.

What is a learning agreement and why is taking this time worth while? Surely everyone knows what they’ve signed up for when they take a training place? The truth of the matter is that students often know the logistics of what they’ve signed up for, but any learning placement is a whole lot more than just the nuts of bolts of the curriculum. There’s a lot of expectation setting/management required for one thing. We’ll cover what learning agreements look like in a bit, but in short they are agreements based on conversations between the learner and their supervisor where they actively set out the expectations and boundaries of their relationship.

At STP/HSST and PhD level it can be the learners first experience of formal education routes within a professional setting. As supervisors we often expect learners to be able to undertake independent study at this point, identifying their own learning objectives and being responsible for any escalations. If this is the students first experience however, they may believe it will follow the pattern of the prior learning they have experienced, which may have placed a lot more focus on structure and consistency.

What is a learning agreement?

In light of these complexities what is a learning agreement and how can it help? Well they take quite a few different forms depending on what it is that you want them to fulfil. In short they are a working (and therefore dynamic) agreement between you as the supervisor/education officer and your new student/trainee. I tend to refer to them as learning agreements rather than contracts as the term contract to me implies penalties and learning contracts are what I escalate to if challenges occur during the time someone is with me.

They can include all kinds of things:

  • What topics are in or out of the learning objectives
  • How deadlines will be set and a broad plan of work
  • Expectation setting around students identifying additional learning objectives
  • Ideas for how the learner will benchmark their progress and/or learning
  • How the educator will assess progress/learning

Although the above is often the framework the most valuable parts of a learning agreement for me are less structural. It is my time to ask:

  • What kind of learner are you?
  • What kind of support do you prefer (close vs supportive supervision)
  • What are your main objectives that may or may not be topic based?
  • What are you hoping this will lead to?
  • How do you prefer to communicate, face to face, email etc?
  • Why this course? Why this training? What attracted you? In order to understand their drivers

Making the implicit explicit

In general I think most of us are good about talking about the nuts and bolts of what a course/placement entails. We are good at giving the ‘this is the bathroom’ tour and ‘this is where your desk is’ plus ‘our supervisor meetings are on Tuesday’ type of information. What I have discovered over the last few years however, is that imparting curriculum or logistic based information just isn’t enough to support a good supervisor-learner relationship, where both get what they want out of it.

I think as supervisors we have quite a lot of expectations that we don’t necessarily voice, after all for many of us this is something we do a lot of. It can therefore be easy to make assumptions about the level of awareness of these expectations from someone coming into that supervisor-learner relationship with us. The thing is, you may have been doing this a loooooong time, but your learner almost definitely hasn’t.  They won’t have that implicit and often organisational linked cultural knowledge that you have been embedded in for so long. Worse than that even, they are likely to have a whole lot of different assumptions based on their last educational experience that they are bringing with them. Unless we all work therefore to make things that we implicitly understand explicit, you won’t know where those differences in practices and expectations lie.  It is when this happens that problems often occur that could easily have been addressed early on, but have significant impacts on learner experience and supervisor stress levels.

Supports orientation to a new field/culture

As I’ve said a few times culture matters, as culture and cultural norms are intrinsically linked with the expectations we all have. Having these conversations is about more than expectation management however. Learners are coming into an environment that may be pretty alien to them. This can make students feel like they are floundering, right from the start, meaning that they don’t feel like they fit. A small percentage of students are likely to walk away because of this, not really understanding the cause. This is often combined and amplified by the fact that they may have moved or lost their support networks in the transition.

Talking about your role (and similar roles) with learners helps, not only to build your relationship and set expectations, but also to support them in making the transition into being a scientist in practice, not just in name. It took me years to feel like a scientist, to feel comfortable calling myself that, to feel like I belonged. Having conversations where students understand what it takes to succeed as a scientist, not just in a placement, can be invaluable to learners re-establishing support networks. Also, supporting learners to find other trainee groups,  to join twitter, or of timings for lunch clubs, can help them settle into their new role and their future profession.

Setting matters

Having these conversations can feel uncomfortable and challenging, mostly because of the fear of the unknown. They may also take time we may not have. All of these are reasons to make sure they are done correctly and given the time required. If you are nervous having them with your learner then imagine how nervous they may be to have them with you. You are asking for a lot of honesty and self reflection from someone who doesn’t know you well, in a relationship where trust may not yet have been built. Furthermore, you are asking for all of this in a relationship where you probably have all the power and where your learner is likely to be highly keen to please, rather than representing their true self..

So how do we hold these conversations and support them getting the best outcomes? I think there a couple of things we can be mindful of. The first is not dropping them on the learner. If we want the conversation to deliver we both need to do the work. I need to be honest with myself about time and also what kind of supervisor I am. The student needs to be given the questions or a framework beforehand and supported to have time to reflect on themselves to be able to answer the questions asked. They may need to be encouraged to speak to friends or family to support them in this reflection if they’ve never done it before. They can then start the process of reflection by thinking in the presence of people they trust, if needed.

Think about where you physically want to have the conversation. I tend to take learners out, to a none Trust space where we can have tea and cake (or other suitable consumables). I’ve written before about the power of tea. The main reason that I do this is that it means we are no ones turf, we are in a neutral space, and the provision of food further helps to reduce/remove hierarchy. When thinking about where however, you need to consider privacy. Your learner may need to share things that are private or important to them, and so considering the type of location is also important.

The other important thing about getting the conversation right is setting the conversational scene before you start the conversation itself. You need to be clear about the objectives that you want to achieve, why they are helpful to both parties and set some ground rules. It’s key to say that honesty is the most important part of this process. It’s OK to have styles that don’t match, by knowing this early you can sign post and find additional support to ensure that the learning process itself still works.

What happens when the expectations don’t match

Hopefully by going through the process of creating a learning agreement you will avoid any significant bumps along the way later on. The process needs to be done thoroughly though, so you don’t just hear what you’d like to hear. As stated above it’s ok to have areas of difference, it’s what you can flex in response to that information and how you respond that matters.

For example, I am never going to be a good micro manager, I have neither the time or personal inclination to work this way. I have fallen foul of not having had the learning agreement conversation and subsequently had learners who felt they were inadequately supported. If I find out that I have a learner who feels they need close support I need to therefore make some pragmatic choices. Is it they will need close guidance for the transition period? If so I can likely change my style for a period of a couple of months in order to support that orientation to a new location. Is it that this is their learning style long term? In this case I need to think about pairing them up or seeking support from a colleague who is better able to provide that close support during the periods in between our catch up sessions.

I have also struggled previously with learners who have not met the outputs that I had expected. This may be more of an issue with PhD students, but to be honest if I’m not clear about publication expectations how will they know? Therefore if it becomes apparent that the timeline expectations don’t match it is worth considering drawing up a broad, high level, delivery plan so you are both working towards the same mental models

Finally, it may be that learners make it clear that they have pastoral care expectations that you may or may not be able to support. Prior to going into these sessions it is important to be aware of the different additional support services that learners have available to them. Whether they need them or not in the moment it is crucial that you sign post to these, especially if you are not the kind of supervisor who will take on this kind of support role. Additionally, there are likely to be plenty of networks that offer peer support that you can sign post learners to. There will always be things that they want to talk about that they won’t want to talk to you about. Let’s be honest, no matter how well you get on there will be times they need to moan about you as a minimum. Being open about this being OK and linking them into peer groups can be incredibly valuable

No matter what you hear in this space it’s important to be open and judgement free, in order to support honest sharing. If you hear something you don’t agree with it’s important to take a beat and try to understand the drivers of that view point. By being open to opinion and challenge now you are investing in success later on. I don’t know about anyone else but I studied in a different time, my undergraduate degree finished 20 years ago. My expectations of learners and learner experience therefore is, to be frank, well old. I’ve also worked in one place for 18 years. It is naïve therefore to believe my experience and expectations are going to perfectly match the learners who are coming through now.

There is a big difference between being someone’s educational supervisor and someone’s manager. In some cases we are both, but we need to understand that they are different roles with different requirements on both sides, and be aware of what hat we are wearing when. Techniques such as learning agreements can help make sure that we do the ‘education’ part better by having the kinds of conversations you would not have with someone you just had a managerial relationship with. It encourages self reflection, expectation management and consensus forming. All of which are skills that we should be modelling for those learners we are supporting. If you don’t ask, you’ll never know. So let’s start this new academic year by having conversations better and talking about how we can all be the best we can be.

All opinions on this blog are my own