Killer Bugs for Halloween: Microbes and murder through the lens of Agatha Christie

I don’t think this is a surprise to any of the regular readers of this blog, but I adore Agatha Christie novels. Reading them has seen me through many a difficult period. They are a source of comfort, escape, and inspiration. I even wrote a previous blog about how there are parallels between solving her ‘who done its’ and my day job, as a hospital detective. What could be more Halloween than a little bit of murder, however, and so today I wanted to talk about how she uses microbes to kill in her books and why the science behind their use brings me so much joy.

When many people think of Agatha Christie murders, however, they think of her as the Queen of Poisons. They are even a number of books written about her experience as a apothecary’s assistant (pharmacy technician) during the Great War (First World War) and others breaking down her use of toxins. Most readers probably don’t necessarily think of her books having much to do with microbiology, even I hadn’t really made the link despite having listened to, read, and watched, all of her content multiple times.

I’ve been going through a difficult period at work, that combined with the hormonal chaos of the perimenopause, has led to a lot of being awake from 2 – 5am. In order to manage the anxiety I’ve been hitting the audiobooks pretty hard, and of course that has meant listening to a LOT of Christie. Imagine my surprise, therefore, that I finally clocked that although many of the deaths include death by poison, there also a few where the death featured is not by toxin, but by microbe! The excitement of this revelation probably didn’t help with the sleeping or resulting sleep deprivation, but it has inspired me to write this blog. So, not all bad then.

WARNING – THERE WILL BE SPOILERS AHEAD!

Who was Agatha Christie?

Dame Agatha Christie wrote 66 detective novels between 1916 and 1976. Her first novel, The Mysterious Affair at Styles, was written in 1916 and published in 1920. Her final work was published after her death in 1976 at the age of 85 and is one of my favourites, Sleeping Murder. Her work features so many wonderful characters, including detective characters that most people will have heard of, Hercule Poirot and Miss Jane Marple. There are many more however, including two of my favourites Tommy and Tuppence, and a girl who will forever hold a piece of my heart, Miss Ariadne Oliver, who is a novelist with some parallels to Christie herself.

Today we’re going to be talking about three main books, published over almost 30 years and featuring three different detective characters:

  • Cards on the Table, 2 November 1936, featuring Hercule Poirot (and my girl Ariadne Oliver)
  • Murder is Easy (originally Easy to Kill), 5 June 1939, featuring a one off appearance by Luke Fitzwilliam as the detective character
  • The Mirror Crack’d from Side to Side, 12 November 1962, featuring Miss Jane Marple

Cards on the Table

This book is based around a dinner party organised by Mr. Shaitana. He is an interesting chap, with an interest in collecting and also murder. He organises a dinner party with a pretty varied guest list, four detective or crime solving characters (Poirot, Oliver, Superintendent Battle, and Colonel Race), alongside four characters who may or may not have been involved with death under suspicious circumstances (Mrs. Lorrimer, Major John Despard, Dr. Geoffrey Roberts, Anne Meredith).

Shaitana is murdered after dinner, in plain sight, whilst sitting in an arm chair, as our suspects play bridge in the same room, and our detectives play bridge in another. The solving of the crime, in the most British way possible, comes down to an investigation of the Bridge hands played. On a side note as a Bridge player in my youth, albeit a very bad one, I kind of love this.

So where do the microbes come in? Not in the murder in the room, but the deaths by suspicious circumstances that one of suspects is trying to cover up.

The first murder by microbe is linked to an affair and the associated cover up, and the way it is done is pretty cool. One of our suspects has an affair with a married woman, and when he realises her husband has discovered what has happened by over hearing a conversation he takes a trip to the bathroom on the pretext of washing his hands. Whilst there he takes the opportunity to contaminate the bristles of a shaving brush with Bacillus anthracis spores, so that next time the gentleman shaves, and ideally has a few shaving cuts, the anthrax will be inoculated into the wounds.
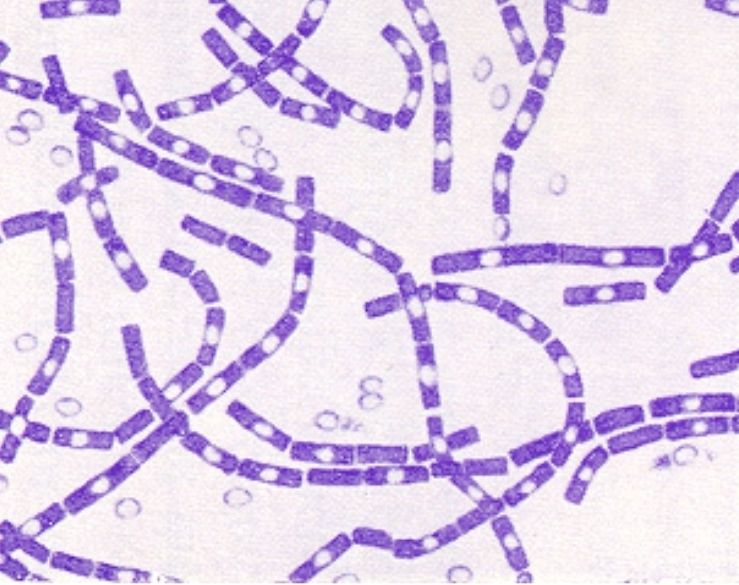
So what would the anthrax do? The association with wounds is key, ideally a deeper cut, as there are 2 likely infectious outcomes from this. The most likely would be Cutaneous Anthrax, resulting in a surface lesion that gradually progresses to turn into a very characteristic, painless, coal-black necrotic eschar. The bacteria then release toxins that cause localised swelling. If the bacteria then enter the blood stream they then can lead to a 5% to 20% mortality rate if untreated, which of course they would be in 1936. Penicillin, which is the main treatment and fortunately the first antibiotic developed, didn’t become widely available until 1945/1946.

Even if penicillin was around it may not have helped if the bacteria entered the blood stream, as you would usually like to use either ciprofloxacin or doxycycline plus one or two additional active antibiotics like vancomycin, imipenem, or meropenem – none of which would be available for some time.

If the inoculation had been deeper, he may have developed Subcutaneous Anthrax, which could result in deep tissue infection and even anthrax meningitis. So the death of his target is not unexpected, especially given the consideration that the victim is likely to have multiple daily exposures every time they shaved.

Why is the shaving brush a clever idea? Well, firstly it’s an object that is likely to be used very regularly, and the spores will survive a very long time upon it. Secondly, not only will it be used often, the likelihood is that it will come into contact with broken skin sooner or later, increasing the chances that severe infection will occur. Third, the inoculation event will be temporarily distinct from the infection, with days to weeks separating the contamination of the brush and the presentation of the infection, making it very hard to trace back to an individual or time point. Finally, and probably most cleverly, these kinds of shaving brushes were often made of badger or boar bristles. During the Great War, however, there was a large scale cutaneous anthrax outbreak linked to shaving brushes that were made of untreated horsehair, some of which were mocked up to look like more expensive badger. This means even if someone identified the shaving brush as the cause, they would have reason to believe that it was an unintentional exposure and there would be even less likelihood of connecting it to our suspect.

Having succeeded once, like many murderers, our suspect decided to try again. The wife of his first victim, yes the one he was having an affair with, appears to become a little too much now her husband is no longer in the picture. He uses the cover of a routine typhoid injection (which had been available as required since the 1897) prior to a trip abroad to inject her with an infectious agent that resulted in her death. It doesn’t list what but if direct injection is an option, and no antibiotic exist, the world is your oyster in terms of bacterial choice.

This may feel a little far fetched, but the video below includes information about the way genetic evidence was collected to show that a doctor within the US injected his ex girlfriend with HIV under the cover of it being a vitamin B injection in order to infect her. Sometimes reality is even stranger than fiction.

Murder is Easy

This is one of my favourite Christie books, and I think it is one that is less known to many. It also has one of my favourite microbial deaths, this time of a main character. Under interrogation it would not be possible for me to deny that all these facts are connected. Luke Fitzwilliam, our detective character and a retired colonial police officer, meets Miss Lavinia Pinkerton on a train to London who is planning on visiting Scotland Yard. She confides in him that a serial killer is operating in her quiet English village, Wychwood-under-Ashe, and that the deaths have been disguised as ordinary accidents. She names a number of deaths that have already occurred (Amy Gibbs, Tommy Pierce, and Harry Carter) and says that the local doctor, Dr. John Humbleby, will be next. I do think this is why I don’t speak to strangers on trains.

Luke mostly thinks that Lavinia just has an over active imagination, until he sees in the newspaper the next day that Miss Pinkerton has been killed in a hit-and-run accident in London. As a result he travels to Wychwood-under-Ashe to investigate further.

He finds that the 3 deaths he’s been told about have occurred in a wide number of ways:

  • Amy Gibbs: Died after drinking hat paint swapped with her cough mixture bottle
  • Tommy Pierce: Pushed from a high windowsill (while cleaning) to his death
  • Harry Carter: Pushed off a footbridge into the river, where he drowned

Dr. Humbleby then dies under suspicious circumstances of sudden onset septicaemia (blood stream infection), but how does it happen? Although anthrax is cool, this method is even cooler. So let’s talk pus.

Dr Humbleby dies as a result of our killer accidentally-on purpose injuring him with scissors whilst he visits their home. When dressing the injured hand our killer uses a bandage that they have deliberately contaminated with pus discharging from the ear of an infected cat, named Wonky Pooh.

Pus is not just fluid; it is a dense mixture of dead white blood cells, cellular debris, and often billions of microorganisms, frequently from different species, combined in one sample. The act of introducing pus (even a small amount) has an infection rate of close to 100% (although obviously no trials on this) as it will overwhelm local tissue defenses, frequently leading to localised tissue damage, and delayed healing. As we are talking about the pre-antibiotic era here, systemic infection (i.e. infection impacting blood or organs) is very likely to occur as the local wound infection cannot be treated. It means our killer has a very high chance of fulfilling their deadly objective. I personally love a pus sample as they are such great specimens to work with…I don’t know what that says about me.

The Mirror Crack’d From Side to Side

Although I have only found three deaths directly linked to microbes, Agatha Christie didn’t just use microbes for murder, she also used them as the motivation for murder.

There is no avoiding spoiling this one I’m afraid, so skip this section if you don’t want to know the core of the plot

The story starts out with film star Marina Gregg and her husband, film producer Jason Rudd, moving into Gossington Hall (the same Hall that features in the Body in the Library) in the village home of Miss Jane Marple, St Mary Mead. The stylish couple host the local village fête where a deadly encounter occurs.

One of the local villagers, Heather Badcock, meets Marina and as part of their discussion talks about how many years before in Barbados she had left her sick bed in order to get an autograph from her. Heather later dies of poisoning at the same event. Miss Jane Marple is not well and so is at home and misses both the conversation and the death, but when more people start to die she decides to investigate and find the reason behind Heather’s death.

As she speaks to people she gets many different explanations as to the reason that Heather was sick when she went to collect the autograph, everything from Chickenpox to Flu. Miss Marple works as an infection detective as the causative organism is what the entire motive hangs on. Eventually, she manages to get an accurate recounting of the conversation from the Vicar, who tell her that Heather says she had German Measles. This fits with what others have said, in that she covered her face with powder in order to hide her rash.

First, let’s talk about what German Measles is, as it is not actually a name in common scientific use, and hasn’t been the approved name since 1881. The virus in question is rubella, but when the presentation was originally discovered it was known as German Measles because it was first described as being distinct from measles by German physicians. Prior to this presentation recognition, rubella was considered to be a variant of either measles or scarlet fever. In 1740, the German physician and chemist Friedrich Hoffmann recognised that it was, in fact, a separate infection. The name rubella was given by surgeon Henry Veale in 1866, meaning little red, as a way to more accurately describe the rash and was widely adopted in 1881.

Why does it matter that Miss Marple identified rubella as the cause? In healthy adults rubella presents as a rash with small flat spots and a high temperature, with or without joint pain and cold like symptoms. You are infectious for ~1 week before the rash starts and 1 week afterwards. Infection is usually mild and self resolves in a week to 10 days. So why would this conversation with Marina result in Heather’s death?

Well, it turns out that Marina had been desperate to have children, so desperate she had adopted. She finally found herself pregnant, but in a way she had never understood, she discovered she had caught rubella when she was 4 months pregnant. As a result, her child was born with a severe congenital learning disability and was placed in a special care facility from birth. Marina suffered a nervous breakdown and became reliant on medication as a result. When Heather approaches her, for the first time ever Marina knows precisely where she was infected and by whom.
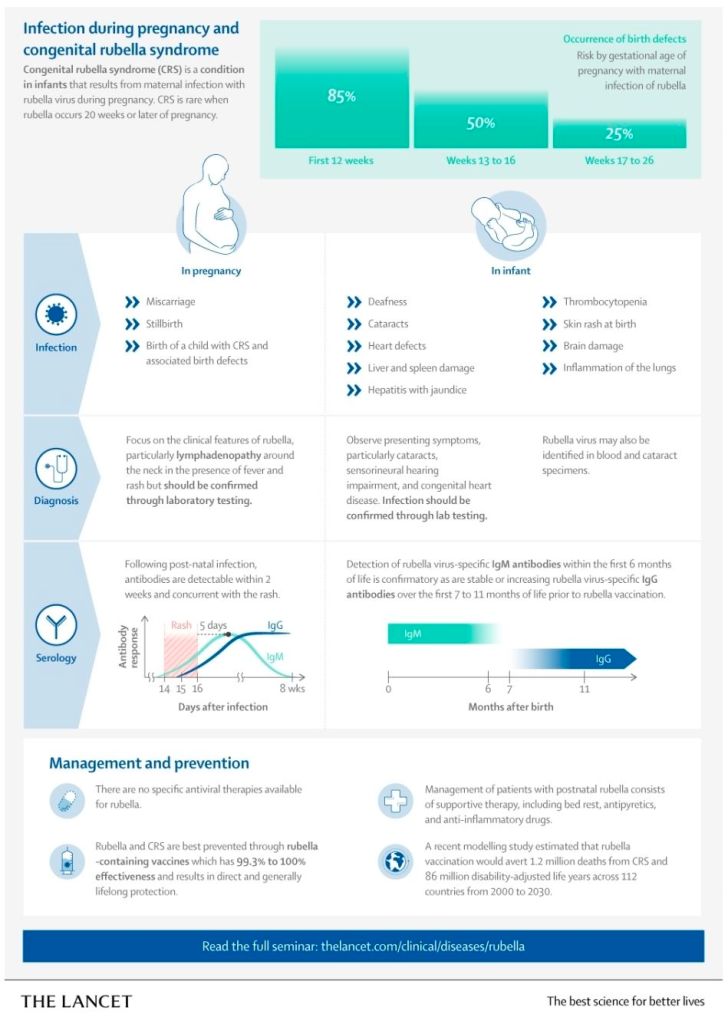
Far from being a mild disease in pregnant women, infection, especially early in pregnancy can have devastating consequences for the foetus. For this reason in the 1970s the rubella vaccination programme was introduced. I remember all the girls in my class being walked into a room separate from the boys when I was in primary school to get vaccinated. The aim of this selective program was specifically to target pre-pubertal schoolgirls and non-immune women of childbearing age in order to protect future pregnancies from the risk of Congenital Rubella Syndrome (CRS).

You may have noticed, however, that the virus infects all individuals, and so by only vaccinating those physiologically capable of bearing children the transmission chain is not interrupted, only the consequences of infection. For this reason the vaccine, within the UK, was extended to everyone in 1988 in order to support better transmission control.

Global vaccine introduction was driven by an outbreak across Europe and the US between 1962 – 1965 that impacted over 12.5 million people in the US alone, and resulted in 11,000 miscarriages and stillbirths. The Mirror Cracked came out in 1962, and so the audience would have been very sensitive to the plot lines within, especially as there was no way to protect pregnancies at the time. Heather deciding to ignore her symptoms and deliberately risk exposing others would have been a particularly heinous act, I image, and there is a powerful quote associated with it as the end of the book:

Heather Badcock meant no harm. She never did mean harm, but there is no doubt that people like Heather Badcock (and like my old friend Alison Wilde), are capable of doing a lot of harm because they lack – not kindness, they have kindness – but any real consideration for the way their actions may affect other people. She thought always of what an action meant to her, never sparing a thought to what it might mean to somebody else.
Agatha Christie, The Mirror Crack’d From Side to Side

I feel that is a strong reflection on some of the more modern behaviours that we see in response to infectious disease, especially post pandemic, and the way vaccine related behaviours are starting to impact wider society. Not only are vaccines beneficial to individuals, but they protect the wider community, not all of whom can get vaccinated. By protecting ourselves we protect others, an option that wasn’t available for Marina, but is available to all of us.

The every present impact of infectious disease

Infectious diseases were part of every day life for most of the time that Christie was writing, and for most of it responding with antibiotics was also not an option. In The Mirror Crack’d, Doctor Haydock says he has to continue his rounds as he has 8 cases of German Measles, Whooping Cough, and Scarlet Fever that he needs to see. Numbers that would be shocking today in a small English village, two thirds of which are now vaccine preventable, and the other readily treated with antibiotics. I think because we don’t see the negative consequences of these types of infection in our every day life, outside of healthcare, we don’t realise how fortunate we are to live in an age where we have such options.

As well as being background, some infectious diseases, especially polio, even provided an alibi…as well as a setting up scenarios for becoming a target for murder in her books.

Christie wrote books at the height of the global polio epidemics and the resulting disease is used as a realistic backdrop to shape the characters’ temperaments, physical mobility, or alibis. Polio is a virus that causes everything from asymptomatic infections to life-threatening paralysis, and nowadays is another vaccine preventable infection.

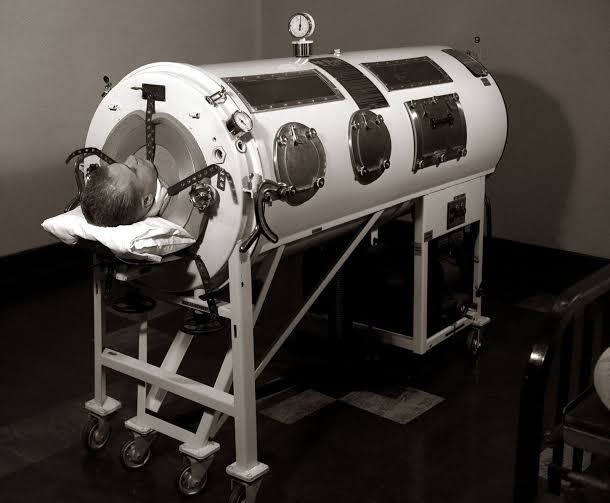
Before modern ventilators became available, patients who experienced muscle weakness due to polio infection were sometimes managed within iron lung machines, that were used to mechanically assist or if needed take over the work of breathing for a patient who has lost control of their respiratory muscles. Having seen historic examples of these when I worked at Boston Children’s Hospital, I can testify to how terrifying they must have been if your child ended up in one.
Within the book, the Crooked House, which came out in 1949, one the main characters is a boy of 16 who is recovering from a mild case of polio. He has a lot of residual stiffness that causes his grandfather to pull him out of school and provide him with a private tutor instead. He becomes isolated by being at home, and the presence of the tutor is also a big driver in the plot after his grandfather is found dead. Polio, therefore, drives a number of the circumstances that result in the subsequent deaths.

Another book that some people may be less familiar with is called Ordeal by Innocence that was published in 1958. The matriarch of the Argyle family is found murdered and one of her adopted children is found guilty, is sent to jail, and subsequently dies.

Dr. Arthur Calgary is a geophysicist who returns from a two year expedition to the antarctic. He sees coverage of the case and realises he is the alibi for the son Jacko who was convicted, but he could not testify as he was away. He turns up to inform the family of the son’s innocence and sets in motion a series of events that reveal the real killer, but also results in many more deaths.

It also causes Philip Durrant, who is married to one of the other Argyle children, to begin his own investigation. Philip has recently contracted a case of severe polio that has left him paralysed and confined to a wheelchair. He hates being dependent and commences his own investigation as a way of asserting his independence. It may not end well for him.

Finally, and I’ve saved one of the best for last. I’m talking about The Pale Horse released in 1961. Some people don’t love this one, but I have to tell you I find it brilliant and clever, and so atmospheric I adore it. I won’t talk about how the deaths are achieved in this one as it is too fun to spoil, but I will mention that one of the main suspects is known as Mr Venables, who requires the use of wheelchair after severe polio infection. An eye witness identifies him close to a crime scene, but his legs are entirely atrophied, making it physically impossible for him to stand or walk. A lot of the discussion therefore centers around whether his has a genuine polio disability or is it a long in the planning elaborate alibi. I’ll leave discovering the answer to you.

Agatha Christie used the times in which she lived, not just as the backdrop for her novels, but as the driver for the plots within them. It is no surprise, therefore, that infectious diseases featured heavily. Living in a pre-antimicrobial, mostly pre-vaccination world must have been terrifying, especially if a loved one fell ill. Using that fear of the unknown, fear of the less understood, makes a lot of sense when setting the scene for murder and mayhem. The inclusion of a detective character, whose job it is to reduce the chaos and make the world make more sense, also explains why it may have struck a cord with those reading who also were experiencing disease within their own daily lives. This deep dive has just made me extra grateful for all the progress we have made in making these organisms much more present in books than they are in my reality, and if possible love Christie even more than I did before.

All opinions in this blog are my own

And now…for a shameless plug

If you love Halloween, or a nice outbreak thriller/zombie film, keep an eye out for my new book ‘Don’t Open That Door: A microbiologist’s guide to infection in movies and TV’ is out in early December, and available for kindle pre order now:

Have you ever wondered whether The Last of Us TV series could actually happen?

Have you ever considered what you would do if you were the one standing at the air lock door in Alien?

Would you open it or leave your crew outside in order to save humanity?

If you’ve ever watched a blockbuster and thought, “Wait, is that how infections actually work?”

Then this book was written for you.

In Don’t Open That Door! A Microbiologist’s Guide to Infection in Movies and TV, Professor Elaine Cloutman-Green (affectionately known to her fans as ‘The Girlymicrobiologist’) bridges the gap between Hollywood fiction and real-world science. Drawing on over two decades of experience as an NHS Consultant Clinical Scientist and infection control expert, she takes you on a fascinating, approachable journey through your favourite movies and TV shows to reveal where the storytelling ends and the real science begins, helping you find the fact within the fiction.

What’s Inside:

  • The Survival Basics: Master the fundamentals of microbiology and infection control, including how pathogens spread from airborne droplets to zoonotic transmission.
  • The Intervention Arsenal: Learn the truth behind pandemic interventions, exploring everything from real-world isolation protocols to the mechanics of vaccines.
  • The Rogue’s Gallery of Pathogens: Dive into dedicated sections exploring the distinct worlds of viruses, fungi, parasites, and bacteria.
  • Hollywood vs. The Lab: Deep-dive into chapters exploring both your favourite cult films and TV series, as well as ones you may be less familiar with. Discover how fictional world-building and cinematic outbreaks stack up against actual scientific investigations.

Whether you are a die-hard sci-fi geek, a horror movie buff, or simply curious about the microscopic partners that share our world, this book will completely change the way you watch television.

Happy Halloween

Environment Network 2025: Investigating Environmental Outbreaks

It’s the most wonderful time of the year! It’s time for the annual Environment Network meeting, where we get together to talk all things environmental microbiology; sharing new research and experience to improve practice. And your guide for the conference this year, live blogging the morning session, is the token immunologist in the group, Dr Claire Walker.

What is the environment network?

Before we get onto todays’ content, a little introduction to what the Environment Network is.

The Environment Network works to support people in clinical, engineering and scientific roles who are interested in environmental infection prevention and control (IPC) and/or the built environment

Do you want to know more about what to do with your water screening and air sampling results?  Are you keen to understand the evidence behind equipment cleaning and the role of the environment in healthcare associated infection?

Then welcome to the Environment Network! 

This is a network for people in clinical/scientific/engineering roles within the NHS and other associated organisations who are interested in the role of environmental infection prevention and control in preventing infection. 

The aim of the network is to support infection prevention and control professionals involved in commissioning, environmental audit, water, air and surface testing within their Trusts.  By working together we can share best practice between Trusts; as well as circulating the latest evidence and discussing personal experiences. 

What are the aims of the network?

  • To support the development of member networks
  • To provide events where shared learning can be supported
  • To permit sharing of experiences and best practice to improve clinical interventions
  • To support and share research in order to achieve improvements in evidence based practice

What is our remit?

  • Environmental testing and monitoring within healthcare environments
  • Environmental audit and risk assessment
  • Surface decontamination
  • Ventilation within healthcare environments
  • Water management within healthcare environments
  • Environmental outbreak monitoring and control

Check out the website for more details: https://environment-network.com/

On to today. First up we have Gavin Wood, an authorising engineer for water who acts as an independent advisor to Trusts. He is covering the fascinating topic of water associate outbreaks and what we can ask of our water safety groups during an outbreak. There should always be a policy which covers how to organise the estates teams and the water safety groups – covering who is responsible for each area during the outbreak. Regular outbreaks are caused by organisms like Legionella and Pseudomonas, but might include non-tuberculosis causing mycobacteria. Detection of these organisms during routine screening is reported to the water safety group to assess potential risk. Most pathogens that we look at will grow within a certain temperature range, so maintaining cold water as cold, and hot water as hot is essential. What we really don’t want is warm water stagnating in the system as the pathogens can thrive in it. On top of this, we need chemical control of organisms – mostly silver and copper ion systems. Stagnant areas of warm water are pockets where the pathogens might thrive so flushing the system and chemical controls are key in maintaining a healthy water supply in hospitals. Controls that are effective for indicator organisms that we routinely test for, like legionella, tend to be effective for any other outbreak organisms. In an outbreak situation the first port of call is the Legionella risk assessment which considers the efficacy of temperature and chemical control. After this, in line with guidance, all trusts should refer to their Water Safety Plan which is contains the detail on actions to take when results are outside the expected limits. Most of the time the authorised engineer already has the answers because the system is repeatedly routinely tested.

Like any system in a hospital, it is vital that the risk assessment and training is up to date. As Gavin says if we haven’t covered everything in the risk assessment, and if the water policy hasn’t been recently reviewed then the whole system is vulnerable. External audit by authorise engineers ensures the system remains optimal. Investigation of an outbreak focuses on the patient pathway – where has the visitor or patient been on their journey through the hospital. This process finds the clues to identify the source of the environmental outbreak. Surprisingly one of the main pieces of evidence comes from review of training and competence records, is everyone appropriately trained and acting in accordance with policy. If in doubt, going an witnessing monitoring and maintenance tasks can provide essential information in a high pressure outbreak situation. Gavin drives home how important practice is in this – we need this information as much on a random rainy Tuesday as much as we need it during a Legionella outbreak!

Our next talk comes from Karren Staniforth from UKHSA. She is a clinical scientist and UKHSA IPC specialist adviser, and is talking to us about the pros and cons of different outbreak investigation techniques. Karren invites us to imagine painting a busy ward in different colour 10cm squares, every single surface with a cotton tip swab. Imagine how long that could take and just how many squares you would end up with! Even if you took 200 samples, how many squares have you failed to test? Usually we can only take 20-40 samples…. So even if they all come back negative, it doesn’t necessarily mean there isn’t an organism there – its just that the sampling didn’t find it. The chances of going in and finding nothing is quite high, but if you put a patient in that room for a week, they will almost certainly find that organism (not that we recommend that as a testing method!).

Karren reminds us that reading environmental plates is quite an art and different from clinical samples, it’s a different skill and guidance from experts is essential. Clinical diagnostic laboratories aren’t accredited to process environmental samples and the staff aren’t trained to process and analyse this work. Commercial companies can come and do testing for you, and they are extremely good at routine work. Bespoke work is harder to commission, and that’s where knowing the network can really help! So if you have an outbreak of something unusual, it’s hard to find the information on what level of environmental organisms – like aspergillus – are ok, and what constitutes a danger to patients.

The questions becomes, what type of samples do we want to take and why? We need to understand basal levels of indicator organisms to work out when to act. Building on what Gavin has shared this morning, you need to look – really look- at what is happening in your environment. Karren reflects on how useful an audit can be but we don’t go into an outbreak with the information already in front of you, so your audit probably won’t ask exactly the right questions. Epidemiology provides the answers – which organisms and then which patients are affected, where and when? Identifying common exposures can be easy when infections match case distribution e.g. sequential patients with the same infection in the same room. However some are less obvious like laundry delivered to multiple sites causing infection clusters which are miles apart or commercial products that might only impact high risk patients in very low numbers, but at multiple sites across countries. This can be exceptionally difficult to trace. Though remember not every exposure results in colonisation and infection, and even if exposure is universal some patient groups are more likely to develop infections than others.

Knowing what kind of sample to take is essential, especially when sample numbers are limited. Negative results can be just as useful as positive results – and identifying the source of the outbreak is as much detective work as it is learning to read plates! Karren reminds us – ‘You don’t always need sampling, somethings are just WRONG!’.

To close the first session, we have Louise Clarke who knows everything there is to know about proper ventilation. Ventilation is essential the movement of air within a system. The law tells us we must provide ventilation under the Healthy and Safety at Work Act, and building regulations set a minimum standard for ventilation. The main reason for good ventilation is to have a safe and comfortable environment; to remove odours, to control temperature and importantly to protect from harmful organisms and toxic substances. We have natural ventilation (like opening a window!), mechanical ventilation which pushes air around the building and a mixed mode – a combination of the two. The preferred method for ventilating a hospital remains natural ventilation, something which really shocked the group. It might work well on a windy day but it certainly doesn’t cover all areas and some times of year, like winter, it’s really no good at all.

Like Lou says, simple is best. When we talk about ventilation, we need to ask what is the issue we are looking at? Human elements are usually a key element to understanding problems in ventilation – you need to think about when the issue arose and who was involved? Often there is a significant time lag between the problem starting and it’s detection in real time. You can be left scrabbling around for details long after the issue began. Lou walked us through the potential information sources to considering during an outbreak, including design records. Which tend to be a little less useful than you would imagine, considering they often tell you the purpose the room was designed for 30 years ago – perhaps not so relevant now! Echoing the sentiments of Karren earlier, one of the most important things you can do is go physically and take a look – not an audit, just turn up and use all your senses!

To kick off the session after a much needed cup of tea (Earl Grey, hot!) we have Dr Mariyam Mirfenderesky who is talking about the challenges of managing fungal outbreaks. Candidozyma auris (note the new name!) is probably one of the most difficult outbreak causing organism to manage. To help with this a Clinical Expert Reference Group was established in March 2025. Candida species are the dominating fungal pathogens of invasive fungal disease and account for >85% of fungaemia in Europe and the United States. Candidozyma auris was first identified in 2009 from a Japanese patient with ear discharge, and is a critical WHO priority fungal pathogen. It is fluconazole resistant and has a propensity to cause healthcare associated infection outbreaks. There are 6 independent clades, with clade 1 dominating in England. Mariyam walked us through the identification of the first neonatal case of C.auris from an eye swab – it was found in two infants, five weeks apart with no direct contact between the children. Fortunately both were colonisation with the fungus only. She then discussed the safety measures that should be in place to manage this difficult pathogen – particularly focusing on why the current cleaning protocols are insufficient to manage this threat. Her final points considered how to act when you detect C.auris – you must be decisive and act!

If you’d like to know more about C. auris, check out this blog post from earlier this year:

Next we have Dr John Hartley who is talking to us about investigating environmental surface mediated outbreaks – what you can’t see may still hurt you. Using the classic movie ‘the fiend without a face’ as a metaphor for IPC, John introduced the idea of modes of transmission between individuals. It feels like a simple problem, its just cleaning and handwashing after all! But we see there is a complex person-organism-environment dynamic system, and as John says, there is always a well known solution to every human problem – neat, plausible and wrong! John highlights the importance of continual surveillance and knowing ‘where the fiend is’. The controls are based on a four pronged approach – clean, replace, destroy or rebuild.

By way of a case study, John told us about his experience of managing adenovirus outbreaks in a paediatric BMT ward. This is a very common virus causing 5-10% of febrile illness in early childhood. Almost everyone has had it, and it can establish latency which can reactivate during BMT. More often it causes severe morbidity and mortality in these patients who can develop hepatitis. What you can’t tell is if the child caught adenovirus from the environment or if it has reactivated post latency. However, whole genome sequencing (WGS) can resolve 1-3 SNPs across genomes – its not like looking for a needle in a haystack, its rather like looking for a needle in the whole of Texas. But WGS can be used to confirm or refute cross infection events.

Of course the next question is, what can be done? Visual assessment is not a reliable indicator of surface cleanliness, John described the varied methods which can be used to detect adenovirus. Then we need to develop the right tools to manage it – including development of environmental PCR as a measure of cleaning efficacy by GirlyMicro herself! Finishing on a Dr Who reference to delight a crowd of scientists is always a win – even if it is comparing adenovirus to the scariest episode, the weeping angels! Of course, when monitoring adenovirus, the most important advice is ‘Don’t Blink’.

To close the morning session we have Dr Sam Watkin discussing research tools to help predict the future of outbreaks. Sam began acknowledging the current challenges facing preventing transmission of environmental organisms. In his PhD he aimed to identify how microbes disseminate through the clinical space, if the starting contamination site determined how is was disseminated and if the usage of space influenced microbial transmission risk. IPC is often retrospective to the aim was to develop research tools to allow the development of prospective knowledge. Sam used cauliflower mosaic virus DNA markers as a surrogate for pathogens, and followed its movement around two different units. It was shocking to see how far this benign organism could spread in such a short time.

I think if we take away anything this morning it’s that nobody likes the new name for C.auris, and death, death to recirculating air conditioning units!

The morning was followed in the afternoon by a series of case discussions in order to help implement the learning from the morning, help everyone get to know each other, and support the sharing of peer to peer learning. The case discussions this year included:

  • Case discussion one (Facilitated by Dr John Hartley):
    • Seek and remove: approaches to source control for environmental surface mediated outbreaks
  • Case discussion two (Facilitated by Professor Elaine Cloutman-Green):
    • How to implement a multi-disciplinary approach to investigation of water borne outbreaks
  • Case discussion three (Facilitated by Louise Clarke):
    • Interpretation of ventilation data and applying it to ventilation risk assessments
  • Case discussion four (Facilitated by Dr Sam Watkin):
    • Determining the role of equipment in outbreaks: how do you investigate?
  • Case discussion five (Facilitated by Karren Staniforth):
    • Introducing new cleaning process: what should you consider?
  • Case discussion six (Facilitated by Dr Claire Walker):
    • Choosing new equipment and furnishings: what questions should you ask?

It was truly inspiring to hear the buzz in the room that all of the discussion created. Thank you to Mr Girlymicro (Jon Cloutman-Green) for being in charge of photography, and to all of our speakers and facilitators for making the day happen. Also, massive shout out to Ant De Souza for pulling the day together, Angela McGee for making sure we all turned up to the right place at the right time, Mummy Girlymicro for running the reception desk, and to Richard Axell for supporting all of the tech on the day.

Now it is all over, the only thing to do is to tap our feet until we all get to meet again in 2026, although the presentations and discussion sheets should go up some time during 2025. Until then however, if you want to know more either head to the Environment Network website to look at info from previous years, or read some of the other blog posts linked to environmental IPC down below.

All opinions in this blog are my own

Going Macro on Micro: Honouring Dr Simon Doherty and collecting all the episode links in one place

This post was supposed to be something quite different. It was supposed to be about One Heath and a great podcast created by Beckman Coulter I was involved with in 2024, alongside some really inspiring people. In some ways it still is that, but because of the cruel reality of life it is actually also something quite different.

”Going Macro on Micro” is a podcast that Dr Simon Doherty and I were involved with that explores emerging themes and pressing issues in the world of microbiology. As the host, Dr Lough, says the podcast covers everything from investigating the global challenges of infection control to unveiling the future of diagnostic technologies.

The week the final episode of the podcast dropped, before Christmas, I got some pretty devastating news. Sadly Simon has passed away. Now, I didn’t know Simon well. We’d emailed since doing the podcase together and I kept an eye on the awards he received and his really interesting posts. In this limited contact though, he still managed to inspire. Recording the series with him was such a privilege. He was kind, open and funny. More than that he was so knowledgeable and I came away feeling like I’d learnt so much. I am so sad that I won’t be able to build on the foundation we laid to continue to learn from him and talk about the challenges/opportunities that face us in the fascinating world we both inhabited. I thought about not sharing these episodes when I heard the news, but then decided that I don’t want you to lose out on the honour I had of learning from him direct. I hope that you will hear both his wisdom and his challenge, and also aspire to do better, as I do, as a result. Thank you Simon.

https://www.bva.co.uk/news-and-blog/news-article/remembering-the-inspirational-life-of-simon-doherty/

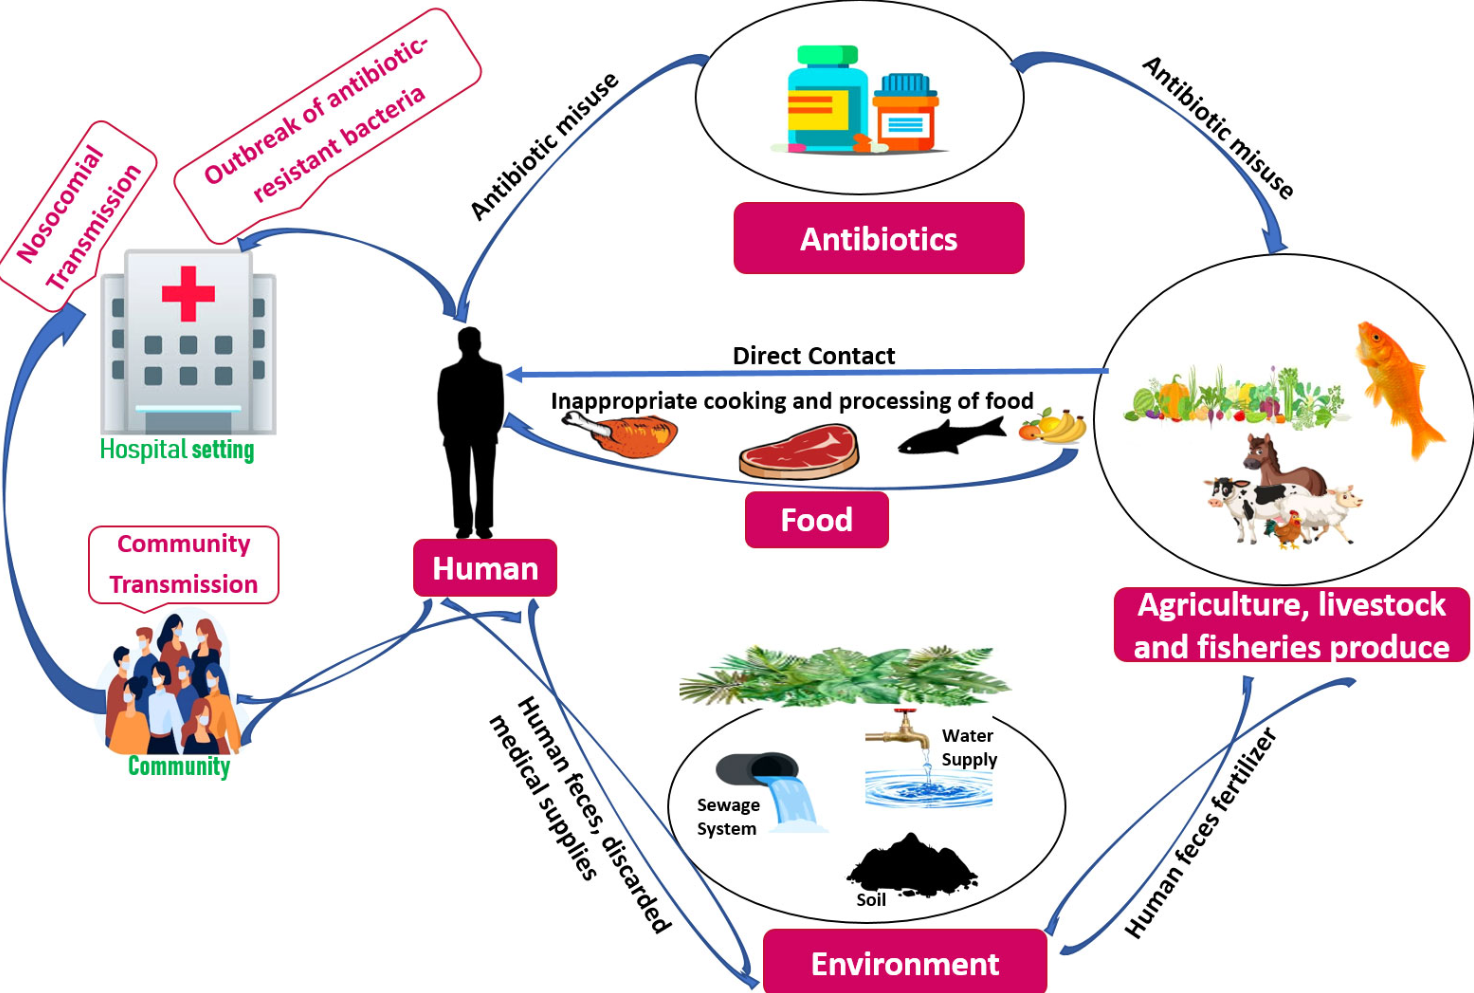
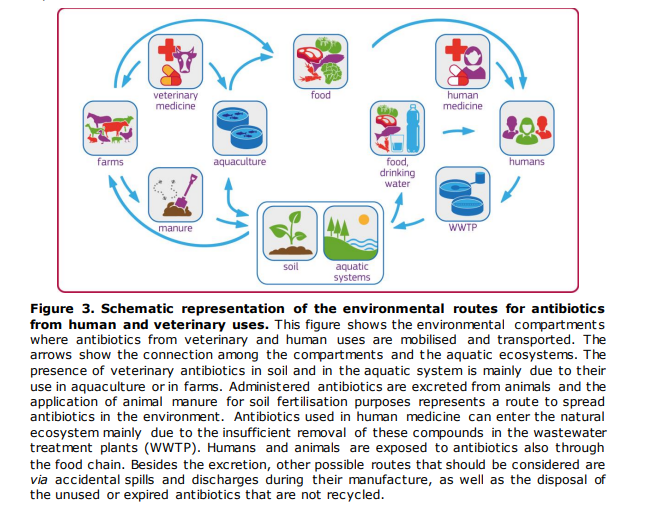
I’ve decided to keep the focus on Simon and just put some graphics and links here that might supporting learning more about antimicrobial resistance and One Health. At some point when the loss of Simon has had a little more time to be processed I will think about writing something in a little more depth reflecting on his comments and the overlap between human health and veterinary medicine. Until then, the links to the episodes are below:

Ahmad Nayeem , Joji Ronni Mol , Shahid Mohammad. (2023). Evolution and implementation of One Health to control the dissemination of antibiotic-resistant bacteria and resistance genes: A review. Frontiers in Cellular and Infection Microbiology

Episode One

Rhouma, M., Soufi, L., Cenatus, S., Archambault, M., & Butaye, P. (2022). Current Insights Regarding the Role of Farm Animals in the Spread of Antimicrobial Resistance from a One Health Perspective. Veterinary Sciences, 9(9), 480. https://doi.org/10.3390/vetsci9090480

Episode Two

Sanseverino, Isabella & Navarro, Anna & Loos, Robert & Marinov, Dimitar & Lettieri, Teresa. (2018). State of the Art on the Contribution of Water to Antimicrobial Resistance. 10.2760/771124

Episode Three

Sanseverino, Isabella & Navarro, Anna & Loos, Robert & Marinov, Dimitar & Lettieri, Teresa. (2018). State of the Art on the Contribution of Water to Antimicrobial Resistance. 10.2760/771124

Episode Four

Sanseverino, Isabella & Navarro, Anna & Loos, Robert & Marinov, Dimitar & Lettieri, Teresa. (2018). State of the Art on the Contribution of Water to Antimicrobial Resistance. 10.2760/771124

Episode Five

Sanseverino, Isabella & Navarro, Anna & Loos, Robert & Marinov, Dimitar & Lettieri, Teresa. (2018). State of the Art on the Contribution of Water to Antimicrobial Resistance. 10.2760/771124

Episode Six

Sanseverino, Isabella & Navarro, Anna & Loos, Robert & Marinov, Dimitar & Lettieri, Teresa. (2018). State of the Art on the Contribution of Water to Antimicrobial Resistance. 10.2760/771124

Other resources

All opinions in this blog are my own

Guest Blog by Callum Barnes: Why the university lab is different to the pathology lab (and why we should plug the gap)

I’m back from a lovely week away at Disneyland Paris, celebrating Christmas and escaping reality (a post on Disney and denial as a coping mechanism is on its way). Whilst I am still struggling with the return to reality this weeks blog post is supplied by the wonderful Callum Barnes. Callum is a disciple of the biomedical sciences, current master’s student creating a more authentic lab experience for those after me, aspiring consultant microbiologist (the best discipline, sorry Claire – you see he understands, like me, that micro will always trump immunology).

Callum is supervised by Dr Claire Walker who is a paid up member of the Dream Team since 2013, token immunologist and occasional defector from the Immunology Mafia. Registered Clinical Scientist in Immunology with a background in genetics (PhD), microbiology and immunology (MSc), biological sciences (mBiolSci), education (PgCert) and indecisiveness (everything else). Now a Senior Lecturer in Immunology at University of Lincoln. She has previously written many great guest blogs for The Girlymicrobiologist, including one on turning criticism into a catalyst for change.

Two years ago, I began a placement year in the microbiology department of a pathology lab, unsure of what was to come, and unsure of myself and my skillset as a scientist. As I think every scientist feels at some point, I was mostly concerned that I would be a hinderance to all the wonderful staff that were just trying to get on with their jobs. Everyone was amazing though and helped me develop the skills and confidence I needed to successfully complete my IBMS portfolio verification. Returning back to university for my final year, I found the lab-based work so much easier than in my second year with my experience, but… something was different. This wasn’t the same stuff I just spent the last year working on, where was the LIMS? The booking in of the samples, the investigative process and the, frankly, the occasional chaos were missing. That’s not to say the labs weren’t good – they were great – and the staff that developed and ran them miles better, but something felt like it was missing. And that’s when my now supervisor Dr Claire Walker came to me with a project for my Mbio year.

Claire and I both have experience in the NHS, herself a lot more than me, but we have both felt and experienced the environment that a pathology lab has. It has a very unique feel to it, slightly alive in my opinion. This is not a very common experience to have in academia though as most academics have a research background, which means that the practical pathology side of things can sometimes get lost when students do their practical work. As such, Claire and I have been working on creating a lab experience that is as authentic to an NHS pathology lab as possible.

But why even bother? The students are learning the same things, just in a different way, so does it really matter? Well in fact, yes, it does! As Claire has said previously, the pilot study she did had very good results, so the data is there to back up our work. But imagine for just a second that you are looking at applying for medicine, and you have two offers. One university offers a fully simulated experience using manikins and actors – the whole shebang. And the other university teaches mostly through theory and shadowing – no practical experience is offered. I know which course I would enjoy and learn the most from. Medical schools know this too and is why most of them offer simulated teaching – it makes for better doctors too.

So, we should really ask, why isn’t this offered for biomedical scientists? Maybe it’s cost, maybe there isn’t the associated prestige. Whatever it is, I am sure that our work will guarantee a truly authentic clinical laboratory experience here on the iBMS accredited course at the University of Lincoln – something I know will provide the right skills for the pathologists of tomorrow.

All opinions in this blog are my own

Let’s Talk Antimicrobial Resistance for World Antimicrobial Awareness Week (WAAW) 2024

I’ve posted in previous years about what antimicrobials are, what antimicrobial resistance may mean for individuals, as well as some thoughts about how we might communicate around some of the challenges linked to antimicrobial resistance in a difference way, or plan our outreach differently. This year I wanted to sign post to some resources that I have either been involved with or found useful in order to help support both our own learning and planning responses to some of the common misconceptions about AMR  I hear when I’m out and about talking to people.

What is antimicrobial resistance?

The World Health Organisation (WHO) talks about it like this:

Antimicrobial Resistance (AMR) occurs when bacteria, viruses, fungi and parasites no longer respond to antimicrobial medicines. As a result of drug resistance, antibiotics and other antimicrobial medicines become ineffective and infections become difficult or impossible to treat, increasing the risk of disease spread, severe illness, disability and death.

I think it’s easy to forget that although AMR is a big part of the professional life of most Infection Control and microbiology professionals, even for other healthcare professionals it features less often, let alone for members of the public. It can be surprising therefore when you do go out and about, or even just talk to friends and family, to hear some of the ways that non infection professionals think about how AMR works and who it impacts.

Common misconceptions I hear when talking to people about AMR:

  • It’s the body that becomes resistant to antibiotics
  • I have never taken antibiotics so I cannot get a resistant infection
  • Antibiotics treat all types of infection
  • Antibiotics can be stopped when the symptoms stop
  • Only infected patients can transmit antimicrobial resistance

If you reflect on some of these myths, it’s actually pretty easy to understand how they come about. Most people are focused on themselves and act from a human centric point of view. Many people give little, if any, thought to the multitudes of living bacteria that co-exist in their bodies. Once you accept this as the starting point, most of these myths are actually based on pretty small mental leaps. If, however, you don’t switch your point of view before you start having conversations about AMR, you can unwittingly end up reinforcing the very misconceptions you were aiming to address.

One of the reasons that I think this post is timely right now, is that I am already seeing more posts linked to how we should not be putting artificial medications into our bodies, alongside the back lash against vaccines, and so it seems to me a good time to remember what a difference these, now common, medical interventions have made to the lives of individuals and public health in general.

Let’s start with a little bit of context

Hardly any of us will have living memory of life without access to antibiotics and what life was like in a world without vaccination. One way to really get a feel for the impact these common interventions have made is to look at the impact in the last 30 years on reducing child mortality (death). Even in this recent time period, massive progress has been made due to advances such as the rota virus vaccine, but also in getting more global access to antimicrobial therapy where it is most needed.

Public health is multi factorial, with impacts being cumulative and made by more than just one thing, so not all of these impacts are made by antibiotic and vaccine availability. Other steps to reduce death linked to infectious disease include everything from clean water and sewer systems to pasteurisation and other means of food safety controls. The impact of these combined approaches is massive, but as the UN sustainable development goals show us, those of us who are access to clean water are not actually in the majority and more is yet to be done to ensure equality of access.

To aim to undo some if not all of this century plus of progress is something I find pretty hard to process. If you’ll forgive the momentary indulgence, I have to state that I think the current anti-vaccine and general anti medical stance that is being seen within some groups and communities is ultimately an act of extreme privilege It’s a privilege to be able to choose not to access something that is readily available to you and not available to others.  It is a privilege not to have to live first hand the consequences of what the alternative might hold. It’s also a privilege to be able to change your mind and choose to access something later. Thinking of things in this light doesn’t necessarily help with having conversations in a supportive and open way when some of the underlying thinking may be so different, but it may mean we can flip the dialogue from one of imposition to one about the power of choice, and supporting evidenced based decision making for all.

Where does AMR come into this?

There’s a big stat that everyone quotes about more people dying from AMR than cancer by 2050, with an estimated 10 million deaths. As a scientist, I get the need to quantify and use numbers, as a human being however, I find that numbers that are so big can just be off-putting. They are so large it can make us, as individuals, feel powerless to impact them.

For me, the reason this conversation is so important to have in the right way, and pitched to the right communities, is because if we are going through a period of global push back against the common interventions, such as vaccination, that have successfully reduced mortality and provided first line protection, then our final line of defence in terms of treatment is now even more vital. 2050 isn’t that far away, and we are already seeing consequences linked to more resistant organisms being identified in severe infections. Therefore, the time to be having conversations and really raising awareness to impact decision-making is now. Sadly, this is coinciding with a period of time when trust in healthcare professionals and science in general feels very low. Instead of being defeated by this, however, we need to use it a driver to really focus on how we can do it better.

One of the other reasons that AMR is both important and challenging to communicate is that it is always in constant flux. You can’t just learn about it and move on. The mechanisms change, the diagnostics change, and the interplay of all of these factors within the bacterial host interactions can make it even more complex and hard to engage with. To exemplify this, the figure below was something I saw posted on Bluesky and fell in love with, as I adore the fact that it lists all kinds of routes to AMR in a single image, thus capturing the complexity of what we’re dealing with.

That said, you don’t have to understand all or any of this image to understand the core of why AMR is going to be a problem moving forward. The main thing to take away from it is that AMR is complicated, and as a result you will hear many different messages linked to it, and those messages will continue to change as we learn more and the impacts are felt differently. As a result, it can then sound like we don’t know what we’re doing, or just end up really off putting, as there isn’t one clear message we are getting out there for people to cling onto. We, therefore, need to build this flexibility into messages and link around core themes rather than trying to talk in absolutes. Otherwise, we risk losing more of the public confidence than has already occurred.

What is being done nationally?

This year, a new version of the UKs National Action Plan for confronting AMR has been released and within it there is a strong focus on the acknowledged need to educate both members of the public and healthcare professionals on AMR.

There is also plenty in there about increasing equitable access to antimicrobials, the need to improve diagnostics to help support both diagnostic and antimicrobial stewardship, and something that pleased me greatly, a special mention of the role of the built environment in managing AMR.

The thing is, top-down approaches will only ever get us so far. At some point, those of us involved in all things infection also need to be consciously including some of these drivers in our own every day practice.

No one can do everything, but whether you are collaborating with industry, undertaking research, or working in clinical practice, we have to embed AMR based action into our encounters. Do you include an AMR slide into all of your teaching? No matter the audience? Do you take the moment when it comes up with friends and family to just talk about the fact that this issue exists? Can you free up some capacity and undertake some public engagement?

Recognising there is a need is not the same thing as addressing that need, and we also have to be there to hold strategic partners and organisations to account in order to make sure action happens. So, let’s consciously match that top-down approach with a bottom-up drive for change.

What resources are there to help talk about AMR to other professionals

Having talked a lot about the need to talk to other healthcare professionals and seeing so much about #WAAW this year, it does really feel progress is being made to support us all to do this better.

Those of you who are UK based have probably heard of and support the Antibiotic Guardian programme (https://antibioticguardian.com/). This programme has lots of resources and supports personal action by asking you make a specific pledge about what you will undertake linked to addressing AMR.

Every year, new infographics come out that talk about different aspects of AMR. Some of these, like the one above, link AMR into commonly known components of healthcare practice, such as hand hygiene, in order to support individuals to feel empowered to act. Others focus more on messaging about antibiotic courses, or as we heard a lot about at the FIS/HIS conference last week, things like IV to oral switches, and sending the right samples to enable a switch from broad to narrow spectrum antibiotics. There’s plenty of ones out there now that can be really useful to embed in talks or laminate and put up on walls. The UKHSA especially have recently released a lot for WAAW, and because there are so many, you can keep them on rotation so that they don’t just become invisible as people see them too frequently.

I’ve also been involved in creating various content this year, as have many others, including webinars and podcasts to explore some of the issues linked to AMR and provide different routes via which healthcare professionals can engage with information and CPD on this topic. I’ve included a link to just one of these below in case it’s of interest, but a quick internet search will provide you with all kinds of others.

https://www.selectscience.net/webinar/resistance-on-the-rise

The main thing to remember is that we all like to receive our learning in different ways, and so ensuring that we remember that when we’re designing our education strategies is one of the best ways to be impactful.

What resources are there to help talk about AMR to members of the public

The resources you might want to use linked to AMR will vary greatly based on your target audience. It’s important to remember that even if someone is a healthcare worker they are also a member of the public, and depending on their personal background or setting they work in, utilising content created for the general public may serve both purposes.

There is some really great video, podcast, infographic, blog, and other content aimed at public outreach on AMR. There’s even a musical called The Mold that Changed the World, about Fleming and Penicillin, as the first antibiotic.

There are lots of different entry points when you are thinking about content that might be appropriate, and you’re likely to go to different depths depending on whether you are doing a one off encounter or a more prolonged piece of relationship building.

The post that is linked to at the start of this article on AMR as a Super Wicked Problem may help with choosing your content. You may also want to consciously address some of the myths mentioned at the start or even start your conversation with the fact that many antibiotics actually started as products identified in nature, and so are not as far from natural compounds as may be frequently thought.

Some of you who have been reading this blog for a while will know how proud and passionate I am about The Nosocomial Project, which aims to use a science, technology, engineering, arts and mathematics (STEAM) approach to talk about infection and infection risks.

As part of this work, we organised a two part festival linked to AMR entitled Rise of the Resistance Festival. All of the content is split across YouTube and the website. I’ve included linked here in case any of it is useful in your own settings when you are looking for inspiration or planning content. The content covered in the festival included everything from a play aimed at pre-school aged children entitled Sock the Puppet, who is a hand puppet who is scared of germs, expert panels, comedy sets, and Klebsiella as a drag queen. I still have so much fun rediscovering this content, and I hope you’ll feel the same way.

I would make a plea that we all work together on this one to do some myth busting and get messages about AMR out there, but also find a way to get messages across that are entertaining/joyous and filled with hope for what we can achieve, rather than focusing on the horrors of what happens if we don’t get our act sorted. I think all of us, including healthcare professionals, have had our fill of trauma in the last few years. So, let’s focus on empowerment and positivity to make this change happen, rather than following in the footsteps of those who want a world of decisions driven by fear.

All opinions in this blog are my own